


Table of content
- What are the key takeaways about preserving eye shape in eyelid surgery?
- Why is orbital fat structure rather than excess?
- How does over-resection cause hollowing?
- What is removed, and what is kept, in a shape-preserving blepharoplasty?
- How do I decide how much upper-lid skin and fat to remove in Dubai?
- How do resection and preservation compare over time?
- What does an over-resected eye look like years later, and why?
- How do I protect eye shape across the different faces I see in Dubai?
- Why does brow position matter when planning eyelid surgery?
- Why is restraint the highest skill in eyelid surgery?
- Where can you read more about protecting the eye’s shape?
- What do patients in Dubai ask about preserving eye shape in eyelid surgery?
- Book a private consultation with Dr. Baycin in Dubai
This article covers why over-resection hollows the eye and how a preservation approach protects its shape; for candidacy, recovery and risks, see eyelid surgery in Dubai, and for the techniques themselves and for dry eye, the in-depth articles linked below.
What are the key takeaways about preserving eye shape in eyelid surgery?
- A youthful eye is defined by soft, supported volume, not by tightness.
- The decisive error is treating orbital fat as excess to be removed rather than structure to be repositioned.
- Over-resection skeletonizes, producing hollows that read as tired and gaunt.
- The failure modes are specific: upper-lid hollowing, lower-lid hollowing and impaired closure.
- The right approach repositions fat to fill the hollow while correcting the bulge, and removes skin conservatively.
- Planning must honor individual and ethnic identity: crease, canthal tilt and facial balance.
Why is orbital fat structure rather than excess?
Orbital fat is structure because it gives the eyelid its soft contour and fills the space between the eye and the bony rim; what patients call eye bags is usually that same fat pushed forward, not surplus tissue. The periorbital region is an architectural zone where skin, muscle and orbital fat work in concert. As the orbital septum, the thin membrane that holds the fat back, weakens with age, the fat pads bulge forward, while the area just below them hollows. The fat has moved; it has not multiplied.
That is why I approach the eye with a single principle: preserve the architecture that makes the eye look alive. True mastery in blepharoplasty requires a shift from resection to preservation, from taking away to strategically repositioning and supporting, and this is the defining discipline of an experienced cosmetic surgeon in Dubai. Volume is one of three pillars I plan around, together with support and the protection of delicate structures, as set out in the volume pillar of periorbital rejuvenation.
How does over-resection cause hollowing?
Over-resection causes hollowing by removing the fat and skin that hold the eye’s contour, so the lid sinks toward the bone and the transitions around the eye become sharp. The consequences are predictable and specific. They are not complications of healing; they are the direct result of an incorrect surgical philosophy, and each has its own appearance.
| Failure mode | Where it shows | What you see | What causes it | How preservation prevents it |
|---|---|---|---|---|
| Upper-lid hollowing (supraorbital hollowing) | The upper lid, below the brow | A sunken lid that reveals the bony orbital rim; a tired, gaunt look | Too much upper-lid fat removed | Conservative upper-lid fat resection, so the lid keeps a soft contour |
| Lower-lid hollowing (infraorbital deficiency) | The lower lid and tear trough | A deepened tear trough and a sharp break between lid and cheek | Lower-lid fat excised instead of moved | Fat repositioned over the rim to fill the trough |
| Impaired closure (dynamic dysfunction) | Both lids, functionally | Incomplete closure (lagophthalmos), dry eye, a lower lid pulled down | Too much skin removed and the muscle disrupted | Conservative skin removal and a lower lid anchored to the orbital rim |
How to read this table: each row is a separate problem with its own cause, so an eye can show one, two or all three; the last column shows that every one of them is prevented at the first operation rather than repaired afterward.
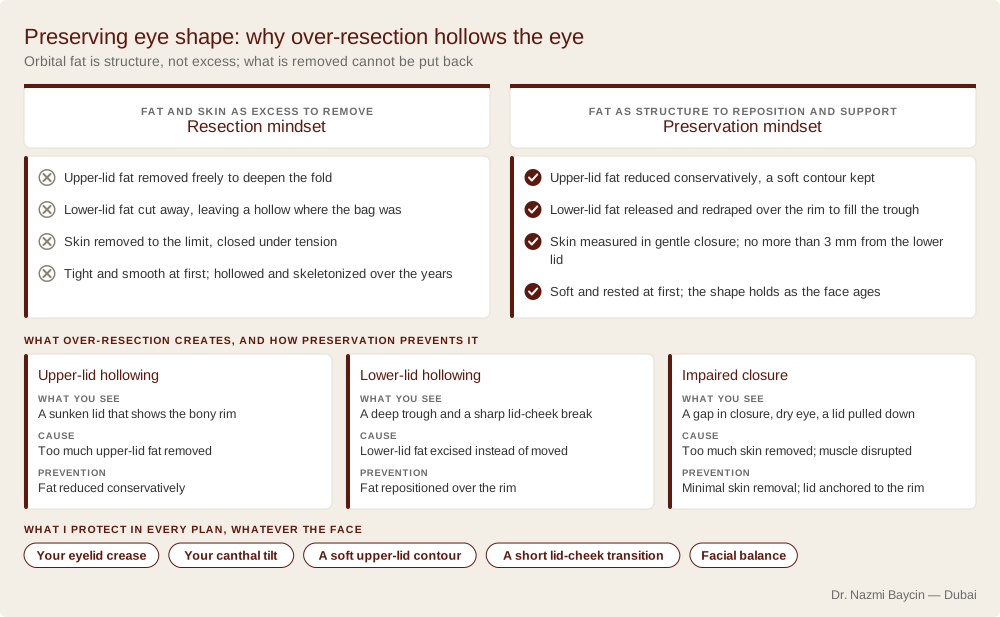
Resection against preservation: what each mindset does to the fat and skin, the three things over-resection creates, and the features of eye shape I protect in every plan. Dr. Nazmi Baycin, Dubai.
What is removed, and what is kept, in a shape-preserving blepharoplasty?
In a shape-preserving blepharoplasty only true skin excess is removed, upper-lid fat is reduced conservatively, and lower-lid fat is kept and moved rather than cut away. My protocol is designed to conserve and restore, not to deplete. On the upper lid, skin removal is calculated with the eye in gentle closure, using a minimal pinch to eliminate only the true excess; the goal is to remove laxity, not to create tension. On the lower lid, I work through a lash-line skin-muscle flap, remove no more than 3 mm of skin, and anchor the lower-lid tissue to the orbital rim in every case, adding a canthopexy or canthoplasty only where the lid is lax; why that limit and that support matter is explained in preventing retraction through canthal support.
The cornerstone of a natural result is what happens to the fat, where my rule is simple: I almost never excise lower-eyelid fat. It is released and redraped over the orbital rim to fill the tear-trough depression, correcting the bulge and the hollow in one move. The surgical detail of how that is done, from the ligament release to the vascularized pedicle and the compartments, is set out in how the fat is repositioned to fill the tear trough.
The reasoning has a long pedigree in the literature, though it should be described accurately: a review of fat-preservation lower-lid blepharoplasty in Clinics in Plastic Surgery sets out transcutaneous fat transposition as its authors’ own preferred technique, with refinements layered onto a framework developed over two preceding decades. That is an expert account of a favored approach rather than a trial showing preservation beats removal, a distinction worth making, because the case for preservation rests on anatomical reasoning and long-term appearance rather than on comparative outcome data.
How do I decide how much upper-lid skin and fat to remove in Dubai?
I decide by measuring, not by eye: the skin is marked with your eyes gently closed, the pinch takes only what prevents closure from being smooth, and the fat pads are reduced only where they bulge. Everything else stays, because the upper lid that looks best at ten years is the one that kept its soft fullness.
- Skin is marked in gentle closure. With your eyes closed as in sleep, I pinch the fold with fine forceps until the lashes just begin to lift, and mark that line. Anything beyond it would be borrowed from closure.
- A minimum stays behind. I keep at least 20 mm of skin between the lower edge of the brow and the lash line, measured at the center of the lid, so the lid can still close over the eye once it heals.
- The brow is checked first. If the brow sits low, part of the apparent excess belongs to the brow, and I lift the brow rather than remove lid skin for it.
- Fat is reduced, not emptied. Only a bulging inner fat pad is reduced, and conservatively; the central fat that gives the lid its contour stays.
- A hollow lid gets no fat removed at all. Where the upper lid is already sunken, removing fat would deepen it; in selected cases I add fat instead.
| What I measure | How | What it sets |
|---|---|---|
| True skin excess | Pinch in gentle closure until the lashes begin to lift | The upper limit of the skin to be removed |
| Skin reserve | Brow edge to lash line with a caliper, at the center of the lid | At least 20 mm must remain after removal |
| Brow position | Manual brow lift while watching the fold | Whether the correction belongs in the lid, the brow or both |
| Fat pad bulge | Gentle pressure on the closed eye to show which pad protrudes | Which pad, if any, is reduced, and how conservatively |
| Existing hollowing | Depth of the sulcus between crease and brow at rest | No fat removed; volume added in selected cases |
How to read this table: the first two rows set a ceiling and a floor for skin removal; the last three decide what happens to the fat. A plan that skips any row is where hollowing begins.
The blink and the tear film are the other reason to measure rather than guess, because a lid that no longer closes fully dries the eye. How I protect them, and who is most at risk, is set out in my article on who is at risk of dry eye after eyelid surgery and how it is prevented.
How do resection and preservation compare over time?
Resection looks tight and smooth early but hollows and ages the eye over the years, while preservation looks soft at first and keeps its shape as the face ages. The difference is best seen side by side, because it explains why two technically successful operations can age so differently.
| Consideration | Resection mindset | Preservation mindset |
|---|---|---|
| View of orbital fat | Excess to be removed | Structure to be repositioned |
| Upper-lid fat | Removed freely to deepen the fold | Reduced conservatively, keeping a soft contour |
| Skin removal | Maximal, chasing tightness | Minimal, removing only true excess |
| Lower-lid support | Skin closed under tension | Lid anchored to the orbital rim; canthal support where lax |
| Tear trough | Often deepened by fat loss | Filled by redraped fat |
| Outer corner of the eye | At risk of rounding or pulling down | Shape and tilt kept |
| Early result | Tight and smooth | Soft and rested |
| Result over time | Hollowed, skeletonized, aged | Volume preserved, ages gracefully |
How to read this table: the early-result row is where the resection mindset looks better, and the row after it is why I do not follow it; the eye has to look right in ten years, not only at the first review.
What does an over-resected eye look like years later, and why?
An over-resected eye looks tight and smooth in the first months, then increasingly hollow, rounded and tired, because the fat that was removed is the volume the face loses anyway with age. The operation spent the reserve early, so aging arrives with nothing left to soften it. I see this pattern in the revision cases that come to me, and it follows a recognizable course.
| Time after surgery | What appears | Why it appears |
|---|---|---|
| First months | A tight, smooth lid; the result looks successful | Swelling fills the space the removed fat left |
| Six to twelve months | The upper lid starts to show the bony rim; the tear trough deepens | Swelling has gone and the missing volume shows for the first time |
| Two to five years | A rounded or downturned outer corner; white visible below the iris | Scar contraction pulls on a lid left without support |
| Five years and beyond | A gaunt, skeletonized eye that looks older than the rest of the face | Normal age-related fat loss arrives with no reserve left to absorb it |
How to read this table: the first row is why over-resection keeps being done; the last three are why I refuse to do it. The timeline is drawn from the cases I revise, not from a published series.
Revision is harder than prevention at every step. Fat that was removed has to be replaced with grafted fat, which survives only in part and can be placed only where there is a bed for it. A lid pulled down by scar needs its support rebuilt and sometimes a graft behind it. The result can be much improved, but it is rarely the eye you would have had if the first operation had kept what belonged to you. How those revisions are planned is covered in my article on revising an over-corrected face.
How do I protect eye shape across the different faces I see in Dubai?
I protect eye shape by planning each operation around the patient’s own crease, canthal tilt and facial balance instead of a single template. A one-size-fits-all approach to blepharoplasty is artistically bankrupt: the ideal eye shape varies profoundly across ethnicities and individuals, and Dubai’s population brings every variation to my consultations. How the anatomy itself differs, from crease height to the fat and skin of the upper lid, is the subject of my article on why eyelid planning differs across ethnic anatomy.
| Feature | What I protect | What happens if it is ignored |
|---|---|---|
| Eyelid crease | Its height and shape, tailored to the patient rather than to an imposed Western ideal | A crease set too high, which changes how open and alert the eye looks |
| Canthal tilt | The angle of the eye, preserved or subtly enhanced so it looks innate | A rounded or downturned outer corner |
| Upper-lid contour | Soft fullness between the crease and the brow | A hollow, aged upper lid |
| Lid-cheek junction | A smooth, short transition from lid to cheek | A visible step or groove below the eye |
| Facial balance | The eyes in proportion to brow position, cheek projection and the rest of the face | Eyes that look operated on rather than refreshed |
How to read this table: the middle column is what I measure and plan for at consultation; the right-hand column is what you would usually notice first when it has been lost.
Why does brow position matter when planning eyelid surgery?
Brow position matters because a heavy or descended brow can push down on the upper lid and look like excess eyelid skin, and removing that skin would treat the symptom rather than the cause. The eyes never exist in isolation, which is why I consider the position of the brow in the same breath as the lid. Where the brow is contributing, the honest correction may lie above the eye rather than within it, so I decide whether the correction belongs within the eyelid, above it or both; over-resecting the lid to compensate for a low brow is one of the commonest routes to a hollow, surprised upper lid. How to tell the two apart is explained in my article on heavy brow versus heavy eyelids, and the choice of lift in temporal versus full brow lift.
Why is restraint the highest skill in eyelid surgery?
Restraint is the highest skill because tissue removed from the eye cannot be put back, and what looks perfectly tight today becomes hollowed stiffness over the years. It takes the confidence to leave well enough alone, the judgment to see where today’s tightness will lead, and the artistic vision to enhance what is uniquely beautiful about a patient’s eyes.
This ethos of measured, anatomical conservation is what separates a technician from a restorative artist. The goal throughout is to make you look like a refreshed version of yourself, not like someone who has had eye surgery: eyes that look alive, soft and naturally youthful, never hollow, surprised or overdone.
Where can you read more about protecting the eye’s shape?
Each part of a shape-preserving eyelid operation has its own in-depth page: this article covers why over-resection hollows the eye, and the pages below cover the rest.
- Eyelid surgery in Dubai: candidacy, technique, recovery and risks — the procedure page, with anesthesia options, the self-check for lid or brow and the day-by-day recovery timeline.
- Repositioning lower-lid fat instead of removing it — the surgical detail of how the bag’s own fat is released and redraped to fill the tear trough.
- Orbicularis suspension of the lower lid — how the lid muscle is lifted and anchored so that it, not tightened skin, carries the lid.
- Canthal support against retraction — how a lax lid is identified and supported so the outer corner keeps its shape.
- Dry eye risk after eyelid surgery — how a preserved blink and a supported lid protect the tear film, and who is at risk.
- Heavy brow versus heavy eyelids — the brow-lift test that stops lid skin being removed for a problem that sits in the brow.
- Why eyelid planning differs across ethnic anatomy — how crease, fat and skin differ, and why the plan follows the patient rather than a template.
- The three pillars of periorbital rejuvenation — how volume, vector and the gentle handling of vessels and muscle are planned together.
- The triad approach to eye rejuvenation — how a conservative blepharoplasty, canthopexy and selective fat grafting are combined.
- Revising a hollowed or over-corrected eye — how a lid damaged by previous surgery elsewhere is released, re-supported and refilled.
What do patients in Dubai ask about preserving eye shape in eyelid surgery?
-
Isn’t the point of surgery to remove the eye bags?
Not in the way many people assume. What look like eye bags are usually not surplus fat to be discarded, but orbital fat pads that have bulged forward as the retaining septum weakens. That fat still belongs to the eye and still provides its contour. Cutting it away flattens the bulge but leaves a hollow behind, which is the trade you would regret ten years later. Keeping the fat and moving it is the better answer, and how that is actually done is set out in my article on lower-eyelid fat repositioning.
-
Is fat preserved in the upper eyelid too?
Yes, though in a different way. The upper lid has no tear trough to fill, so its fat is not moved; instead, where a fat pad bulges, I reduce it conservatively and leave enough behind for the lid to keep a soft contour between the crease and the brow. Removing upper-lid fat freely is what creates the sunken, hollow upper lid that reveals the bony rim.
-
Can hollowing from earlier eyelid surgery be corrected?
Often it can be improved, though rarely reversed completely, because the tissue that was removed cannot be put back as it was. Where some fat remains, I redistribute it to soften the hollow; where there is hollowing with nothing left to reposition, I add volume with a small fat graft in selected cases, and a lid that has been pulled down also needs its support restored. How these revisions are planned is covered in my article on revising an over-corrected face.
-
How do I choose a surgeon who will preserve my eye shape?
Look for a surgeon whose results look soft and alive rather than tight and surprised, and who speaks about preserving volume rather than simply removing tissue. Because the difference between a natural and a hollowed result comes down to surgical philosophy, the way a surgeon thinks matters as much as their technique. Ask a prospective surgeon how they handle the orbital fat; an answer built on repositioning and preservation, rather than removal, tells you they understand how to protect your eye shape. Reviewing a portfolio of eyes that look rested rather than operated on is the clearest test.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
