

Table of content
- What are the key takeaways about strategic fat preservation in high-definition liposuction for patients in Dubai?
- Why is high-definition liposuction a question of what to keep rather than what to take?
- What does the preserved fat layer do for the result?
- How much fat do I leave, and where?
- How do I judge the preserved layer during the operation?
- Where must fat never be removed?
- What does the evidence say about working the superficial fat layer?
- What do I ask you to understand before high-definition liposuction?
- Where can you read about each part of high-definition liposuction in more depth?
- What do patients ask about fat preservation in high-definition liposuction?
- Why do you describe fat as something to preserve rather than remove?
- How much fat is left over the muscle after high-definition liposuction?
- Does keeping fat make the definition less visible?
- How do you know during surgery when to stop?
- Why are some areas not treated at all?
- Does the fat you leave behind grow back or enlarge?
- Can fat be put back if too much was removed?
- Get appointment
Strategic fat preservation in high-definition liposuction is the planned retention of a thin, even layer of superficial fat over the muscle, thicker over the muscle bellies and thinnest along their borders, so that the skin stays smooth, well supplied and mobile while the definition beneath it shows through.
This article covers what I deliberately preserve in high-definition liposuction: which fat stays, how much, where, what it does, and where nothing is touched at all. How VASER works, candidacy, recovery, risks and cost are on liposuction in Dubai; how the deep-layer shaping and the superficial etching are combined and sequenced in one operation is in how high-definition VASER liposuction and abdominal etching are combined; what an over-etched abdomen looks like and why it is hard to correct is in why over-etching ruins abdominal definition; why the surgeon rather than the device decides the result is in surgeon technique versus technology in VASER liposuction; how fibrous and soft fat change the way each layer is worked is in fibrous fat versus soft fat; and the catalogue of contour deformities, what each looks like and what correction can offer, is in athletic results without contour deformities.
What are the key takeaways about strategic fat preservation in high-definition liposuction for patients in Dubai?
The definition you see after high-definition liposuction is drawn by the fat that is left, not by the fat that is taken, and I plan the preserved layer as carefully as the removal.
- High-definition liposuction reveals the muscle you have; it does not fabricate muscle you do not.
- The preserved superficial layer does four jobs: it keeps the surface smooth, feeds the skin, lets the skin glide over the muscle, and absorbs weight change and age.
- The layer is thinnest along a muscle border and thickest over the muscle belly; it is reduced along the lines, never cleared.
- I judge it during surgery by pinch, by light with the table tilted, and by comparison with the other side, and I stop when the landmark reads, not when the fat is gone.
- Five zones of adherence on the trunk and thighs are not treated at all, because fat removed there leaves a permanent dent.
- In the largest pooled review, one patient in seven had a complication after high-definition work, almost all of them superficial-layer problems; major complications were rare.
Why is high-definition liposuction a question of what to keep rather than what to take?
Because the definition is not made by the absence of fat; it is made by a thin, even layer of fat lying over a muscle so that its shape shows through the skin. Remove that layer and the muscle does not look more defined; the skin simply collapses onto it and shows every irregularity beneath.
Standard liposuction addresses volume: the aim is less, and the measure is milliliters. High-definition liposuction addresses form and the way light falls across it, and its measure is what remains. The common mistake is to chase maximal definition at the expense of structural honesty, exaggerating muscle groups that are not there or clearing the fat between the ones that are. I do not create illusions; I reveal what exists, which means studying your own muscle insertions, fat distribution and skin before deciding how much to leave over each.
Definition should look born, not built. The moment a result begins to look fabricated, a pattern stamped onto an abdomen rather than drawn from it, the philosophy has failed, however precise the instruments. That is why I describe this operation to patients as a question of restraint, and why the rest of this article is about the fat I keep.
What does the preserved fat layer do for the result?
The preserved layer does four things: it keeps the skin surface smooth, it carries the blood supply to the skin, it lets the skin glide over the muscle rather than sticking to it, and it gives the result room to tolerate weight change and age. Each job has a failure that appears when the layer is taken.
| Job | How the preserved layer does it | What fails when it is removed | When the failure shows |
|---|---|---|---|
| A smooth surface | A thin, even cushion between skin and muscle evens out every small irregularity in the muscle and in the suction passes beneath | Ridges, waves and a surface that shows the track of every pass | Within weeks, once swelling has gone; worse in thin skin and in good light |
| Blood supply to the skin | The vessels that feed the skin run up through the fat beneath it; leaving the layer leaves the supply intact | Dark, mottled skin, slow healing, firm scar beneath the skin, and in the worst case skin loss | Darkening in the first weeks; firmness over months |
| Gliding, not sticking | Fat between skin and muscle lets the two move independently when you bend or tense | The skin heals stuck to the muscle and dimples or puckers whenever the muscle contracts | From the second month, and permanently; it is the hardest failure to revise |
| Room for life | A preserved layer swells and shrinks a little with weight and loses a little elasticity with age without the surface changing | A few kilograms or a decade turn a stripped abdomen lumpy, because there is no cushion to absorb the change | Years later, which is why early photographs of over-resected results look deceptively good |
How to read this table: the third column is the list of problems I am most often asked to correct after high-definition work elsewhere, and every one of them is a preservation failure rather than a removal failure. What each looks like in detail, which error produces it and what correction can offer is the subject of my article on athletic results without contour deformities; the over-etched abdomen in particular, and why fat cannot simply be put back, is in my article on why over-etching ruins abdominal definition.
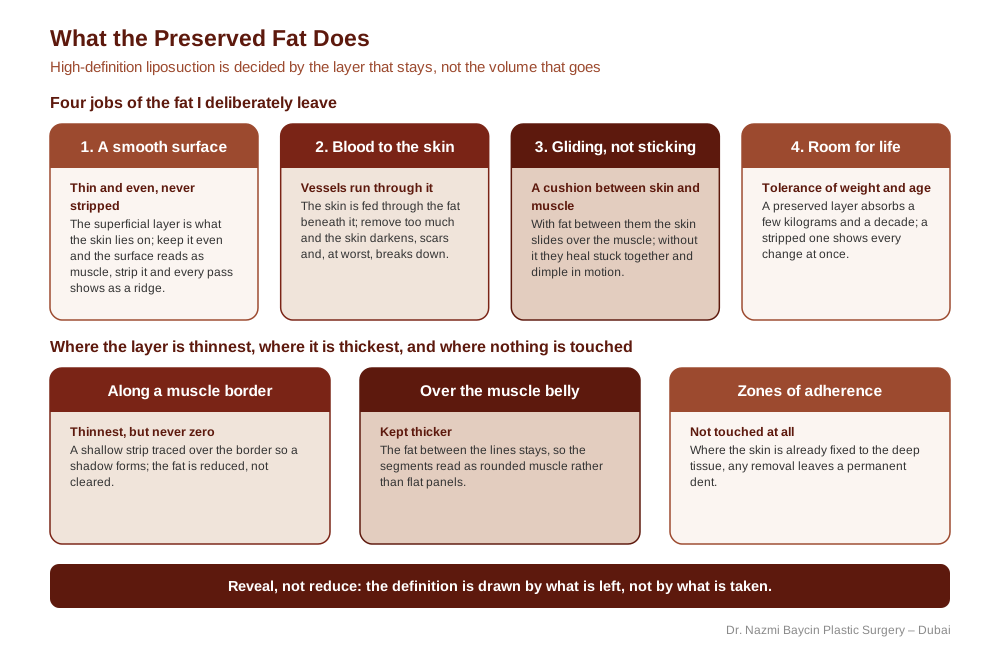
What the preserved fat does in high-definition liposuction: the four jobs of the layer that stays, where it is thinnest and thickest, and where nothing is touched, by Dr. Nazmi Baycin, Dubai.
How much fat do I leave, and where?
I leave a layer that is thinnest along the borders of a muscle, where a shadow is wanted, and thickest over the muscle belly, where the rounded shape must read; I leave the deep layer tapered rather than emptied at the edges of every treated area; and I leave some regions untouched altogether. The thickness is set by pinch, not by a number, because skin and fat differ from one patient to the next, and so does the fat itself: a dense, fibrous zone holds its thickness differently under the cannula from a soft one, which is why the tissue is read before the layer is set, as described in my article on fibrous fat versus soft fat.
In practice I think in terms of what the skin should rest on in each region, and the table sets out how that varies across the abdomen and torso.
| Region | What is preserved | Why that thickness | What goes wrong if less is left |
|---|---|---|---|
| Along a muscle border (midline, outer borders, inscriptions) | The thinnest layer: a shallow, narrow strip is reduced so a soft shadow forms, but the skin never rests directly on the muscle | A shadow needs only a small step in thickness to read; a trench reads as a cut | A fixed groove that does not change with movement, and skin stuck to the border |
| Over the muscle belly (between the lines) | The thickest preserved layer in the treated zone; the fat between the lines stays | The rounded segment of muscle is what makes definition look like muscle rather than a grid; the layer gives it its convexity | Flat panels between sharp lines: the topographical-map look |
| Flanks and lower back | Bulk is taken from the deep layer; the superficial layer is thinned evenly and left intact | These zones are seen from the side and in motion, where any irregularity in the superficial layer shows first | Waves and dents over the obliques; a waist that looks narrow from the front and lumpy from the side |
| Transitions into untreated skin | A taper: progressively more fat is left as the edge of the treated area approaches | The eye reads an edge wherever thickness changes suddenly | A visible step where treatment stopped |
| Over bony prominences (ribs, hip bones) | Fuller than the surrounding treated skin | Bone shows through a thin layer as a hard shelf rather than an athletic line | A skeletal, over-thinned look at the ribcage or hips |
| Zones of adherence | Nothing is removed | The skin is already fixed to the deep tissue here; see the section below | A permanent depression that cannot be released |
How to read this table: read the second column as a gradient, thinnest at a border and thickest over a belly, with a taper at every edge and an exclusion zone where the skin is already adherent. The map of which zones are etched and which are shaped, and the order they are treated in, is in my article on combining high-definition VASER and abdominal etching; this table is about what each zone keeps.
In a lean man with thin skin the whole gradient is shallower, because there is less fat to begin with and less margin for error, so the strips along the borders are fewer and the passes shorter. In a woman the preserved layer over the muscle belly is kept thicker still, because the aim is a soft two-pack and a defined waist rather than a hard grid; how the goals differ is set out in my article on six-pack surgery in men versus women.
How do I judge the preserved layer during the operation?
I judge it three ways during the operation: by pinching the skin between finger and thumb to feel the thickness of what remains, by looking at the surface under raking light with the table tilted, and by comparing the two sides at every stage. The endpoint is when the landmark reads, not when the fat is gone.
None of these is a measurement, and I distrust surgeons who quote one, because skin thickness, fat quality and the depth of the muscle differ in every patient. What I rely on instead is a set of checks repeated throughout the operation:
- The pinch. Before any fat is removed I pinch each zone and note the thickness. During the operation I pinch again and stop along a border when the fold has thinned to a shadow and over a belly when it has thinned evenly but still has substance. A pinch that reaches skin on skin is a pinch I have gone too far on.
- Raking light. With the table tilted and the light low, the surface shows every wave that would be invisible from above. I do this after the deep layer is shaped, again after the superficial strips, and once more after blending, and I correct unevenness by adding to the thin side rather than by thinning the thick side further.
- The other side. Each stage is completed on both sides before the next begins, so that asymmetry is caught while it can still be matched by restraint rather than by removal.
- The landmark test. The question I ask at each zone is whether the muscle border or the waist now reads from across the room. When it does, I stop, even if more fat could be taken. More fat is the one thing I cannot give back.
The device plays no part in any of these decisions. VASER makes the deep layer easier to remove evenly and the superficial strips easier to trace without tearing, but it cannot tell me when to stop, which is why I regard technique as the whole of the result and the machine as a tool within it; that argument is made in full in my article on why surgeon technique matters more than technology for VASER liposuction. That judgment is the foundation of all of my cosmetic surgery in Dubai.
Where must fat never be removed?
Fat must never be removed from the zones of adherence, five regions of the trunk and thighs where the skin is naturally fixed to the deep tissue by fibrous attachments with little fat between. Liposuction there does not thin a cushion; it removes the only tissue holding the skin away from the muscle, and the dent it leaves is permanent.
These zones were described in 2001 by Rohrich and colleagues, who reviewed the anatomy of the subcutaneous tissue in the trunk, correlated it with magnetic resonance imaging and analyzed cases of primary and secondary liposuction, and who recommended that the five zones be avoided in circumferential liposuction whether suction-assisted or ultrasound-assisted. In high-definition work, where the aim is to thin the superficial layer deliberately, the temptation to continue a line into one of these zones is real, and resisting it is part of the preservation discipline. The same five zones are respected when the whole trunk is treated in one operation, which is the planning described in my article on 360° liposuction.
| Zone | Where it lies | Why it is adherent | What liposuction there causes | What I do instead |
|---|---|---|---|---|
| Lateral gluteal depression | The hollow on the side of the hip, below the hip bone | Fibrous attachments fix the skin to the deep fascia over the hip | A deep, fixed dent that exaggerates the hollow | Shape the fat above and below it so the natural hollow reads without being deepened |
| Gluteal crease | The fold where the buttock meets the thigh | The crease is a dense attachment that defines the lower border of the buttock | A buttock that loses its lower border and droops over the thigh | Treat the thigh below and the buttock above; never the crease itself |
| Distal posterior thigh | The back of the thigh just above the knee | Thin fat tightly bound to the underlying tissue | Irregular, adherent skin above the knee | Taper any thigh treatment to a stop well above it |
| Middle medial thigh | The inner thigh at mid-level | Fat is sparse and the skin is thin and loosely supported | Waves and sagging of inner-thigh skin | Shape above and below with a long taper, and address loose skin by lifting, not suction |
| Inferolateral iliotibial tract | The outer thigh low down, over the band that runs to the knee | The skin is fixed to the tough band beneath | A dent over the outer knee that shows in every pair of shorts | Stop outer-thigh contouring above the band |
How to read this table: the fourth column is the reason these zones are a rule rather than a judgment. In every other region the preserved layer is a gradient I set; in these five there is no layer to set, and the only correct thickness is the one nature left. The locations are those described in the original paper; its abstract gives the number of zones and the method, and the sites themselves are set out in its text.
What does the evidence say about working the superficial fat layer?
The evidence says that working the superficial layer produces definition and skin retraction, and that its price is a high rate of minor, superficial complications: in the largest pooled review about one patient in seven had a complication after high-definition liposuction, nearly all of them problems of the superficial layer, while major complications were rare. It does not measure how much a preserved layer lowers that rate, because no study has compared preservation with its absence.
A 2023 systematic review of 21 case series covering 6,964 high-definition liposuction patients found an overall complication rate of 14.4 percent, of which only 0.2 percent were major. The commonest problems were transient skin darkening in 3.8 percent, seroma in 3.3 percent and transient firmness beneath the skin in 2.7 percent, and reported satisfaction was 92.6 percent. The authors describe the technique as targeting the superficial layer to reveal anatomy while promoting skin retraction, which is the same layer this article is about. Three cautions keep the figures honest: the review pools case series with no controlled comparison and no uniform reporting; the satisfaction figure rests on the 1,497 patients for whom it was reported, not the full 6,964; and the three commonest complications are all injuries of the superficial layer, which is the point I draw from it.
The 2001 paper by Rohrich and colleagues on the zones of adherence is anatomical rather than statistical: it reviews the subcutaneous anatomy of the trunk, correlates it with magnetic resonance imaging and with primary and secondary liposuction cases, and recommends avoiding five zones to prevent contour deformity. It reports no rates, so it supports the rule in the section above and nothing more.
| Source | Design | What it found | What it does not show |
|---|---|---|---|
| Willet and colleagues, 2023 | Systematic review of 21 case series, 6,964 patients | Complications 14.4 percent, major 0.2 percent; skin darkening 3.8 percent, seroma 3.3 percent, transient fibrosis 2.7 percent; satisfaction 92.6 percent of those reporting | Any effect of how much fat was preserved; no comparison group and no uniform reporting across series |
| Rohrich and colleagues, 2001 | Anatomical review correlated with MRI and with primary and secondary liposuction cases | Five zones of adherence in the trunk and thighs that should be avoided to prevent contour deformity | Any rate of deformity; it is a description of anatomy and a recommendation, not an outcome study |
How to read this table: the first row tells you how often the superficial layer is injured in practice; the second tells you where it must not be touched at all. Neither tests the gradient of preservation described on this page, which is reasoned from the anatomy and from what revision cases show.
What do I ask you to understand before high-definition liposuction?
I ask you to understand that this is a reveal, not a transformation: the operation can show the muscle you have built and cannot build muscle you have not, and the result you will see is drawn by the fat I leave as much as by the fat I take. The general requirements, weight, skin and health, are on my liposuction page; this is the conversation specific to definition.
The patients who do best are those who can describe what they want in the language of their own anatomy, a sharper oblique line or a better-defined border, rather than simply asking to look smaller or harder. That dialogue tells me two things: that you have looked at your own body closely enough to know where the muscle is, and that you will accept a result that follows it rather than a template. I decline to etch lines on an abdomen whose muscle will not support them, and I decline to strip the layer between lines to make them sharper, because both produce a result that looks defined in a photograph and deflated in life.
Where the skin will not retract over a preserved layer, the answer is to address the skin, not to take more fat; the tightening options are set out in my article on J-Plasma skin tightening after liposuction. Where a previous operation has already taken too much, the correction is a different discipline, covered in my article on revision body contouring.I invite you to a discussion not about what I can remove, but about what I can reveal; the plan and its cost follow from that discussion, at consultation.
Where can you read about each part of high-definition liposuction in more depth?
This article covers what is preserved; the pages below cover the procedure, the operation that combines the techniques, and each of the decisions and risks around it.
- The procedure, how VASER works, safe volumes, candidacy, recovery, risks and cost: liposuction in Dubai
- Six-pack surgery as a procedure: abdominal etching and six-pack surgery in Dubai
- How the two techniques are combined, in which layer and in which order: combining high-definition VASER liposuction and abdominal etching
- What an over-etched abdomen looks like and why it is hard to correct: why over-etching ruins abdominal definition
- The five contour deformities, their causes and their correction: athletic results without contour deformities
- How fibrous and soft fat change the technique: fibrous fat versus soft fat
- Planning the abdomen, flanks and back as one continuous form: 360° liposuction
- Why the surgeon, not the device, decides the result: surgeon technique versus technology in VASER liposuction
- Planning for the body in motion: the 4D concept in liposculpture
- How the goal differs for men and women: six-pack surgery in men versus women
- The male torso as one plan: male body sculpting and why the male form needs its own rules
- How long definition lasts: skin quality and six-pack longevity
- When the skin, not the fat, is the limit: J-Plasma skin tightening after liposuction
- Correcting a previous operation: revision body contouring after poorly sequenced surgery
What do patients ask about fat preservation in high-definition liposuction?
Patients most often ask why I talk about keeping fat in an operation that removes it, how much is left over the muscle, and whether keeping it makes the result softer; the answers below are specific to preservation.
-
Why do you describe fat as something to preserve rather than remove?
Because the preserved fat is what makes a result look like muscle rather than like surgery. The thin layer I leave over the muscle keeps the skin smooth, carries its blood supply, lets it glide when you move, and absorbs the small changes of weight and age that would otherwise show as lumps. Take that layer away and the skin collapses onto the muscle: it looks carved and deflated rather than defined, it sticks and dimples, and it ages badly. So I plan the fat that stays as carefully as the fat that goes, and I remove just enough along the muscle borders for a shadow to form. The intelligent preservation of fat is as vital as its removal.
-
How much fat is left over the muscle after high-definition liposuction?
Enough that the skin never rests directly on the muscle anywhere, with the amount varying by region. Along a muscle border, where a shadow is wanted, the layer is thinned to a narrow, shallow strip; over the belly of the muscle, between the lines, it is kept thicker so the segment reads as rounded muscle; at the edge of every treated area it tapers back to the untreated thickness. I set it by pinching the skin rather than by a number, because skin and fat differ in every patient; a pinch that reaches skin on skin means too much has gone. In a lean man the whole gradient is shallower, and in a woman the layer over the muscle is kept fuller for a softer result.
-
Does keeping fat make the definition less visible?
It makes it look like definition rather than like lines. A shadow along a muscle border needs only a small step in thickness between the border and the belly beside it; it is the contrast that reads, not the depth of the groove. Stripping the layer between the lines to make them sharper produces flat panels divided by trenches, the topographical-map look, which photographs sharply and looks wrong in life because real muscle is convex between its borders. The preserved layer is what gives each segment that convexity. Definition that shows clearly in motion and softens at rest is the natural pattern, and it comes from keeping fat, not from removing it.
-
How do you know during surgery when to stop?
By three checks repeated throughout the operation, and by one question. I pinch each zone before and during treatment and stop along a border when the fold has thinned to a shadow and over a belly when it is even but still has substance. I tilt the table and look at the surface under low, raking light, which shows waves that are invisible from above, and I correct unevenness by leaving more on the thin side rather than taking more from the thick side. I complete each stage on both sides before moving on, so asymmetry is matched by restraint. And at every zone I ask whether the landmark now reads from across the room; when it does, I stop, because more fat is the one thing I cannot give back.
-
Why are some areas not treated at all?
Because in five regions of the trunk and thighs, the zones of adherence, the skin is naturally fixed to the deep tissue by fibrous attachments with very little fat between. They are the hollow on the side of the hip, the crease under the buttock, the back of the thigh above the knee, the mid inner thigh, and the outer thigh low down over the band that runs to the knee. Liposuction there does not thin a cushion; it removes the only tissue holding the skin off the muscle, and the dent it leaves is permanent and cannot be released. So I shape the fat above and below these zones with long tapers and leave the zones themselves exactly as nature made them, however tempting it is to carry a line through them.
-
Does the fat you leave behind grow back or enlarge?
It does not grow back, because fat cells that are removed are gone and the ones that remain do not multiply in adults to any meaningful degree. It can enlarge, because every remaining fat cell swells with weight gain, and that is true of the preserved layer exactly as it is of any untreated fat. A preserved layer is an advantage here rather than a risk: because it is even, it enlarges evenly with a few kilograms and the surface stays smooth, whereas a stripped abdomen with patches of remaining fat becomes lumpy with the same gain. What protects the result is weight stability, which I cover in my article on skin quality and six-pack longevity.
-
Can fat be put back if too much was removed?
Only partly, and only with difficulty. Fat can be grafted into a depression from elsewhere on the body, but it has to survive on a blood supply in tissue that has been scarred by the first operation, so a proportion is lost, the result is less predictable than the original layer would have been, and it often needs more than one session. Where the skin has healed stuck to the muscle, the adhesion must be released first or the graft does nothing. That is why I describe preservation as a matter of safety as well as aesthetics: prevention is a single decision during the first operation, and correction is a long and uncertain one afterward. How that correction is approached is the subject of my article on revision body contouring.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
