


Table of content
- What are the key takeaways about correcting asymmetric labia?
- When is labial asymmetry worth correcting?
- Which differences between the two labia do I assess?
- Why do I map each labium separately in motion in Dubai?
- What do I record for each side before planning?
- How do I make a separate plan for each side?
- What do I never sacrifice for symmetry?
- How is asymmetry after a previous labiaplasty different?
- Where can you read about each part of labiaplasty in Dubai in more depth?
- FAQs about asymmetric labia in Dubai
- Get appointment
This article covers how labial asymmetry is assessed and how each side is planned; for the labiaplasty technique in general, candidacy, recovery and risks, see labiaplasty in Dubai, and for asymmetry left by a previous operation, see corrective revision labiaplasty.
What are the key takeaways about correcting asymmetric labia?
Each side is diagnosed and planned on its own, so two different labia reach one balanced shape without either being over-reduced to match the other.
- Some asymmetry is normal; a difference of more than about 5 mm, or one that causes symptoms, is what warrants correction.
- The sides can differ in length, thickness, projection, edge and pigmentation, and each is assessed separately.
- Dynamic mapping of each labium in motion guides the plan, not just its length at rest.
- Each side often needs a different plan to reach one harmonious shape.
- The goal is balance, not sameness: natural proportion rather than a forced mirror image.
- Restraint matters: chasing symmetry is a common route to over-resection.
When is labial asymmetry worth correcting?
Labial asymmetry is worth correcting when the difference between the two sides is greater than about 5 mm, or when it causes you friction during exercise, difficulty with clothing, irritation or real self-consciousness. Some degree of variation between the two sides is entirely normal, and mild asymmetry within that natural range is something I leave alone rather than treat as a defect.
My priority, when correction is warranted, is to restore balanced, natural contours while keeping the tissue soft, sensate and functionally healthy, the standard I hold across my plastic surgery practice in Dubai.
Which differences between the two labia do I assess?
The differences I assess between the two labia are length and projection, thickness and firmness, the edge with its texture and pigmentation, and any share of the imbalance that comes from the clitoral hood. “Asymmetry” is not one thing: two labia can be mismatched in several independent dimensions at once, and each has different surgical implications, so I identify exactly which are in play, and to what degree, before planning anything.
| What differs | How it presents | Why it matters for planning |
|---|---|---|
| Length or projection | One side protrudes further than the other | Determines how much edge to reduce, and on which side |
| Thickness or firmness | One labium is bulkier or denser | Bulk is a volume problem as well as an edge problem |
| Edge, texture and pigmentation | An irregular border, folding, or a darker edge on one side | Guides how the new border is shaped on each side |
| Clitoral hood share | Excess hood skin on one side adds to the imbalance | May need addressing so that a new imbalance is not created above |
How to read this table: most women show more than one row at once, and the rows can point in different directions on each side; the plan answers every row that applies rather than the most visible one alone.
The causes behind these differences vary:
- Natural variation that becomes more noticeable with age.
- Stretching from pregnancy or childbirth.
- Friction from sport, especially cycling and riding.
- Hormonal change.
- Previous injury or a previous operation.
The cause rarely changes the surgical plan, but naming the exact pattern of difference always does.
Why do I map each labium separately in motion in Dubai?
I map each labium separately in motion because asymmetry is a matter of contour and behavior, not length alone: two labia can measure the same on a ruler yet sit and move quite differently. A side that looks balanced lying down can protrude or fold differently when standing, so I chart each side standing, reclining and flexed, and then compare the two records with each other rather than with a norm.
Charting each side’s behavior separately is what allows the cuts to be designed so that no visible ridge or step-off is left between them. The literature is beginning to formalize the same principle: a quantitative study of labia minora morphology in 400 women in Frontiers in Surgery introduced a measurement method that records the left and right sides as separate sets of values. How the same dynamic examination identifies the source of discomfort before any labiaplasty is set out in my article on how labial discomfort is diagnosed before surgery, and why careful preoperative design prevents unwanted results in my article on common unwanted results after labiaplasty.
What do I record for each side before planning?
I record the same five measurements for each side, in the same positions, and then set the two records side by side. The plan is drawn from the differences between them, not from either side alone.
| What I record, on each side | In which position | What the comparison decides |
|---|---|---|
| Length from base to free edge | Standing and reclining | Whether the difference exceeds about 5 mm, and which side carries the excess |
| Projection beyond the outer labia | Standing, then with the thighs flexed | How much edge each side needs reduced to sit level with the other |
| Thickness of the base | Reclining, by pinch | Whether one side needs thinning or a wedge as well as a trim |
| Edge pattern and pigmentation | Reclining, under good light | How the new border is shaped on each side so the two edges read as one |
| Hood skin on that side | Standing and reclining | Whether the imbalance continues above the labia and must be answered there |
How to read this table: every row is measured twice, once per side; the last column is what the two numbers decide together. A plan that measures only the larger side has already assumed the answer.
How do I make a separate plan for each side?
I make a separate plan for each side by matching the technique to the difference that each labium shows, so that two sides with different problems reach one shared shape. It is, in effect, two operations planned on one patient: forcing a single plan across both sides is precisely what leaves one side over-reduced or still mismatched.
| What the side shows | What the plan for that side does |
|---|---|
| Greater length or projection | A modified trim that reduces the protruding edge more on that side |
| A darker or irregular edge | The trim removes the darker edge with the excess and reshapes the border |
| Greater thickness | A modified trim combined with thinning of the base, or a central wedge in selected cases with enough length |
| Excess hood skin on that side | The hood is reduced on that side so the balance holds above the labia too |
How to read this table: read it once for each side; the left and right labia often land in different rows, which is why the two sides can receive different plans and still end in one balanced shape.
Occasionally both sides need reshaping, but with different geometry on each, and in some cases approaches are combined within a single side. How thick tissue is reduced is explained in my article on labiaplasty for thick labia minora, and the techniques themselves on my page on labiaplasty in Dubai.
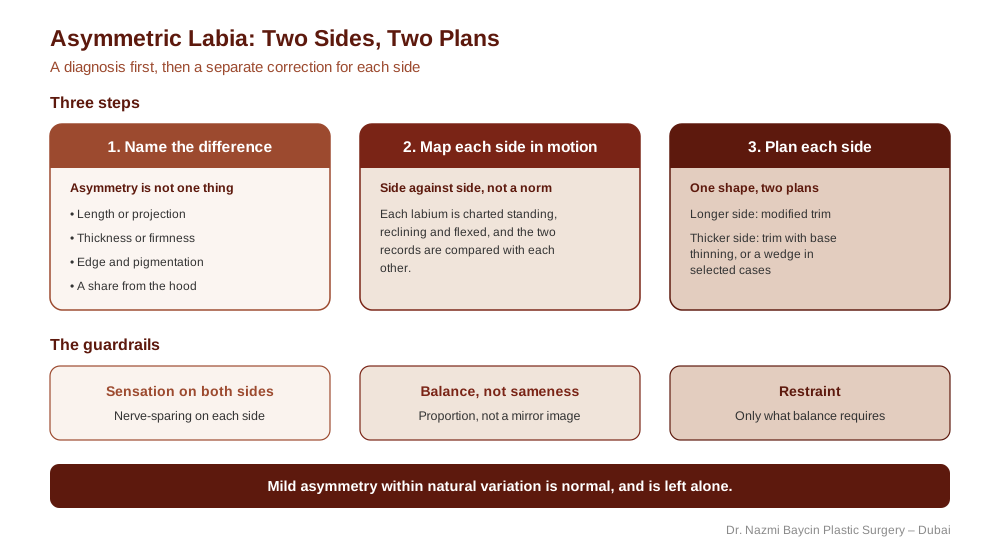
How asymmetric labia are corrected as a diagnosis and a side-specific plan, within three guardrails, by Dr. Nazmi Baycin, Dubai.
What do I never sacrifice for symmetry?
I never sacrifice sensation, natural proportion or healthy tissue for symmetry, because pursuing symmetry carelessly can cause more problems than the original asymmetry. My planning is bounded by three principles.
- Nerve-sparing dissection on both sides: because each side may receive a different plan, the discipline is applied to each side independently rather than assumed to carry across. How sensation is preserved during a reduction is set out in my article on preserving sensation during inner-labia reduction.
- Harmony over identity: the goal is balanced, natural proportion, not a forced mirror image; perfectly identical sides are neither achievable nor natural.
- Restraint: chasing symmetry is a common route to over-resection, so I remove only what balance requires. Why that restraint matters is set out in my article on why restraint defines a natural labia reduction.
Where one side also carries excess clitoral hood skin, I assess and address it so that correcting the labia does not leave a new imbalance above; when the hood should be treated together with the labia is explained in my article on combining labiaplasty with clitoral hood reduction.
How is asymmetry after a previous labiaplasty different?
Asymmetry after a previous labiaplasty is different because it means operating in scarred, altered tissue and often rebuilding rather than reducing, so it is treated as revision surgery rather than as a first correction. That is a distinct undertaking with its own timing and expectations, which I detail in my article on corrective revision labiaplasty; the techniques that bring two unevenly operated sides back into balance, by adding to the deficient side rather than reducing the better one, are in correcting scarring and asymmetry after labiaplasty. For primary asymmetry, the far more common situation, the path is more straightforward, but the same side-by-side diagnosis applies.
Where can you read about each part of labiaplasty in Dubai in more depth?
This article covers asymmetric labia; the pages below cover each other part of labiaplasty in depth.
- The procedure, recovery and risks: the labiaplasty procedure page
- Diagnosing discomfort: how labial discomfort is diagnosed before surgery
- Thick tissue: labiaplasty for thick labia minora
- The clitoral hood: combining labiaplasty with hood reduction and nerve-sparing clitoral hood reduction
- Sensation and restraint: how sensation is preserved and why restraint defines a natural result
- Results to avoid and how to correct them: common unwanted results after labiaplasty, corrective revision labiaplasty and correcting scarring and asymmetry after labiaplasty
FAQs about asymmetric labia in Dubai
-
Is some labial asymmetry normal?
Yes. The left and right labia commonly differ slightly in length, thickness or shape, and this is natural variation rather than a defect. Correction is worth considering when the difference is greater than about 5 mm, or when it causes friction, difficulty with clothing, irritation or real self-consciousness. I do not treat mild, symptomless asymmetry as a problem to be fixed.
-
Can both sides really be made to match?
They can be brought into natural balance, though a perfect mirror image is neither achievable nor desirable. The aim is balanced projection, smooth edges and proportionate shape, not two sides made mathematically identical; even unoperated anatomy is never perfectly symmetric, and chasing exact sameness would look unnatural and risk over-reduction.
-
Why can the two sides look different while healing?
Because the two sides may have had different amounts of work, they can swell and settle at slightly different rates in the early weeks. That is normal and is not a sign that the asymmetry has returned. I judge the final balance only once the swelling has fully settled, since early swelling can temporarily mask the true result.
-
Can non-surgical treatments fix labial asymmetry?
No. Energy-based devices and lasers may improve the surface quality of the tissue, but none of them can reshape or reduce excess labial tissue, which is what correcting asymmetry requires. Because the imbalance is structural, with one side genuinely carrying more or differently shaped tissue, only a planned surgical correction can bring the two into proportion in a predictable, lasting way.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
