


Table of content
- What are the key takeaways about preventing unwanted labiaplasty results in Dubai?
- Why does preoperative design, not the instrument, decide a labiaplasty result?
- Which unwanted results does each design decision prevent?
- What are the three disciplines of preoperative design?
- What do I map and measure before drawing the incision line in Dubai?
- Why do millimeters decide the outcome in conservative design?
- How do selection and preparation prevent unwanted results?
- Why is prevention always preferable to correction?
- Where can you read about each part of labiaplasty results in more depth?
- FAQs about preventing unwanted labiaplasty results in Dubai
- What is the single most important factor in avoiding labiaplasty complications?
- Why do you assess the anatomy both standing and lying down?
- What does conservative resection actually mean?
- Does the choice of instrument prevent unwanted results?
- Why is staging a small second adjustment safer than one aggressive resection?
- How do selection and preparation reduce risk?
- What do I measure before drawing the incision line?
- How do I choose a surgeon who plans this carefully?
- Get appointment
What are the key takeaways about preventing unwanted labiaplasty results in Dubai?
Nearly every unwanted labiaplasty result I am asked to correct traces to a planning decision, so prevention is a design discipline: map the anatomy dynamically, design conservatively in millimeters, and make sure you are the right candidate, properly prepared, before any line is drawn.
- Most unwanted results trace to poor preoperative design, not to equipment or tools.
- Labiaplasty is roughly 80% design and 20% execution.
- Dynamic mapping — standing and supine — captures anatomy a static exam misses.
- Conservative margins matter: tissue can be removed later, never restored.
- Selection and risk optimization set healing up to succeed.
- Correcting a poor result is a separate discipline — prevention is always preferable.
An unwanted labiaplasty result is an outcome — over-resection, asymmetry, a scalloped edge, lost sensation, or an exposed vestibule — that was built into the plan before the operation began. The labia are delicate, highly innervated tissues that vary widely from one woman to the next, so millimeter differences in planning translate into major differences in outcome. This is why I regard prevention as a design problem, not a tools problem, a conviction that guides my work as a plastic surgeon in Dubai.
This article covers how preoperative design prevents unwanted labiaplasty results. For the techniques themselves, my reasons for avoiding energy-based devices, candidacy, recovery, risks, and cost, see my labiaplasty in Dubai page; for the aftercare disciplines that protect the result once the operation is done, see my article on the labiaplasty aftercare protocol.
Why does preoperative design, not the instrument, decide a labiaplasty result?
Because the decisions that produce an unwanted result — how much to remove, where the edge will sit, which anatomy must be preserved — are all made at the marking stage, and no device can correct a plan that was wrong before it began. It is tempting to attribute good outcomes to a particular device or a favored suture. In reality, nearly every unwanted result I am asked to correct traces back to a decision made, or not made, before the operation.
The evidence points the same way. A published systematic review and meta-analysis of labiaplasty techniques and risk factors in the Aesthetic Surgery Journal found high satisfaction across all methods, pooled at 94%, but meaningfully different complication rates between them — dehiscence reached 8% after wedge resection — and concluded that surgeons must tailor the approach to each woman’s needs and anatomy rather than apply one method to everyone. In fairness to that paper, it also found the scalpel carried a higher incidence of bleeding, swelling and hematoma than laser, which cuts against the way instrument choice is often argued; my own preference for sharp technique rests on wound-edge healing, which I explain on my labiaplasty page. What the review does establish is the point this article is about: the plan matters more than the catalogue.
My own formulation is simple: labiaplasty is roughly 80% preoperative design and 20% execution. Before any incision, I spend meaningful time evaluating labial projection, border thickness, tissue elasticity, the clitoral-hood relationship, your natural asymmetry, and your goals. The operation itself is largely the disciplined enactment of a plan already made.
Which unwanted results does each design decision prevent?
Each of the results you may fear most has a specific planning decision that prevents it, and the table below pairs them. This is the catalogue the title promises, read backward: not what can go wrong, but which decision stops it.
| Unwanted result | How it shows | The design decision that prevents it |
|---|---|---|
| Over-resection | An exposed vestibule, dryness, tightness, and loss of the natural edge. | Margins planned generously in millimeters, with a second small adjustment preferred to one aggressive cut. |
| Asymmetry | One side visibly longer or thicker than the other after healing. | Dynamic mapping standing and supine, with your natural asymmetry measured and planned for, not discovered at surgery. |
| Scalloped or notched edge | An irregular, wavy border along the reduced labium. | Preserving the natural edge and the mucocutaneous junction, and planning the line as one continuous curve. |
| Loss of sensation | Numbness or altered sensitivity that persists beyond healing. | Incisions and margins planned to respect the nerve supply; conservative margins are themselves the main protection. |
| Hood disproportion | A clitoral hood that looks heavy or exposed against the reduced labia. | Assessing the hood-to-labia relationship at the mapping stage and deciding then whether hood reduction belongs in the plan. |
| Wound breakdown | The suture line separates in the first weeks. | Selecting and preparing you: smoking cessation, stable medical conditions, and a technique matched to your tissue. |
How to read this table: every row’s third column is a decision taken before the operation. The pages that go deeper into each result are listed in the further-reading box near the end of this article.
What are the three disciplines of preoperative design?
Mapping the anatomy, designing conservatively, and selecting and preparing you; each pre-empts a category of unwanted result. Good planning is not a single step but three connected disciplines.
| Design discipline | What it involves | What it prevents |
|---|---|---|
| Map the anatomy | Dynamic assessment standing and supine; measure vestibular aperture, border thickness, elasticity, projection, and the hood relationship. | Mis-estimated margins and unrecognized asymmetry. |
| Design conservatively | Plan the margin in millimeters; leave more than seems necessary; stage rather than over-resect. | Over-resection and an unnaturally tight, exposed vestibule. |
| Select and prepare | Confirm candidacy and realistic goals; full history; optimize modifiable risks before surgery. | Impaired healing, wound problems, and disappointment. |
How to read this table: the disciplines run in the order I apply them at consultation; each row’s last column is the category of result it is there to prevent.
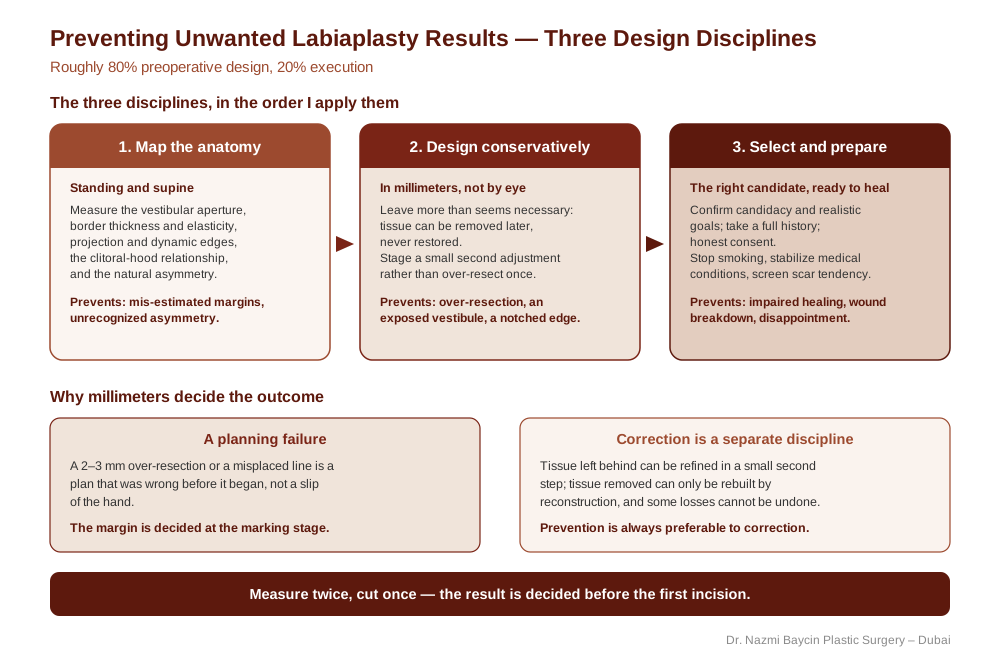
The three disciplines of preoperative design — map the anatomy, design conservatively, select and prepare — and why a 2–3 mm misjudgment is a planning failure rather than a slip of the hand — by Dr. Nazmi Baycin, Dubai.
What do I map and measure before drawing the incision line in Dubai?
Five things, with you both standing and lying down, because the labia change shape between the two and marking you only lying down misjudges the edges that actually move in daily life. Before drawing a single line, I document the dynamic anatomy — in effect, measuring twice so I cut once.
| Measurement | What it tells me | What it decides in the plan |
|---|---|---|
| Vestibular aperture | The depth that must be preserved for comfortable function. | The inner limit of the margin; the line never encroaches on it. |
| Border thickness and elasticity | How the edge will settle and heal after reduction. | Whether the edge is trimmed or the tissue is thinned, and how much to leave for settling. |
| Projection and dynamic edges | What protrudes in motion and when standing, not only at rest. | Where the margin sits so the result holds when she is upright and active. |
| The clitoral-hood relationship | How the hood balances against the planned labial contour. | Whether hood reduction belongs in the same plan, and in what proportion. |
| Natural side-to-side difference | How much asymmetry exists before surgery, and where. | Different margins on each side so the result, not the resection, is symmetrical. |
How to read this table: each measurement sets one constraint on the incision line. Taken together they define the plan before the instrument is chosen.
Why do millimeters decide the outcome in conservative design?
Because the trade-off is not symmetrical: tissue left behind can be refined later in a small adjustment, while tissue removed cannot be restored without complex reconstruction. If one principle sits at the center of prevention, it is conservatism, and this article is concerned with how it is built into a plan rather than with why it matters — the case for restraint itself, and what over-resection costs, I make in my article on why restraint defines a natural labia reduction.
In design terms conservatism means three things:
- Generous margins: planned deliberately wider than seems necessary, in millimeters, not estimated by eye.
- Staging: adjustments made in a small second step rather than chased with a single aggressive resection.
- Preservation: the natural edge and the mucocutaneous junction kept, unless you specifically request otherwise and understand the trade-off.
This is also why I treat a 2–3 mm misjudgment as a planning failure rather than a slip of the hand. The margin that protects the vestibule and preserves comfortable function is decided at the marking stage. Where a previous surgery has already removed too much, restoring it is an entirely different undertaking — the reconstructive work I describe in my articles on corrective revision labiaplasty and on correcting scarring and asymmetry after labiaplasty, which is precisely the outcome careful design exists to avoid.
How do selection and preparation prevent unwanted results?
By making sure the anatomy, the goals, and the healing capacity are all in place before the plan is drawn, so that no intraoperative skill has to compensate for a problem that could have been settled at consultation. The final discipline is making sure you are the right candidate, and that you are prepared.
- Consultation: establishes the anatomy, the function, and realistic expectations.
- Consent: covers honestly the possibilities of asymmetry, sensation change, and the rare need for revision.
- Modifiable risks: smoking is addressed with cessation several weeks before surgery, medical conditions are stabilized, and any tendency to abnormal scarring is screened for in advance.
- Special anatomy: pronounced side-to-side differences have their own planning logic, set out in my article on correction of asymmetric labia.
How the reduction is then executed so that labial sensation survives it is a separate subject, which I set out in my article on preserving sensation during inner-labia reduction, and when the clitoral hood is part of the picture, its reduction follows nerve-sparing principles I detail in my article on precision clitoral hood reduction.
Why is prevention always preferable to correction?
Because correction works with whatever tissue the first operation left, and some results — significant over-resection, true loss of sensation — cannot be fully undone. Labiaplasty rewards precision, anatomical respect, and conservative judgment above all.
The best results arise not from any single instrument but from careful preoperative education, conservative planning, and diligent follow-up. You are welcome to a detailed, anatomy-based consultation to plan an approach around your comfort, sensitivity, and long-term satisfaction.
Where can you read about each part of labiaplasty results in more depth?
Each page below owns one part of the topic, so you can go straight to the question you have.
- Techniques, the laser question, candidacy, recovery, risks, and cost: labiaplasty in Dubai
- Why restraint matters and what over-resection costs: why restraint defines a natural labia reduction
- Planning for pronounced asymmetry: correction of asymmetric labia
- How sensation is preserved during the reduction: preserving sensation through the neurovascular anatomy of labiaplasty
- When the clitoral hood is part of the plan: precision clitoral hood reduction
- The aftercare disciplines that protect the result: the labiaplasty aftercare protocol
- Correcting a result that has already gone wrong: corrective revision labiaplasty, correcting scarring and asymmetry after labiaplasty and correcting vertical malposition
FAQs about preventing unwanted labiaplasty results in Dubai
-
What is the single most important factor in avoiding labiaplasty complications?
In my view it is preoperative design — the planning done before the operation ever begins. I describe labiaplasty as roughly 80% design and 20% execution, because the great majority of unwanted results trace back to decisions made, or missed, at the planning stage rather than to the tools used. This means carefully mapping the anatomy, measuring the tissue, understanding your natural asymmetry and goals, and choosing a conservative, individualized plan. Once that groundwork is done well, the surgery itself is largely the disciplined execution of a sound plan. No device or technique substitutes for this thinking; prevention is fundamentally a design problem, not a tools problem, and that is where my attention is concentrated.
-
Why do you assess the anatomy both standing and lying down?
Because the labia change shape and position depending on posture, and a plan based only on a lying-down examination can misjudge the tissue that actually matters in daily life. When you are lying down, the edges settle differently than they do standing, so marking the excision in that position alone risks removing too much or creating asymmetry once you are upright. By assessing the anatomy dynamically — both standing and supine — I capture how the tissue truly behaves and plan the margins around that. I also measure features such as vestibular aperture, border thickness, elasticity, and the clitoral-hood relationship in this process. This dynamic mapping is one of the practical ways careful design prevents the uneven or over-resected results I am often asked to correct.
-
What does conservative resection actually mean?
In planning terms it means deliberately leaving more tissue than might seem necessary, because the trade-off is not symmetrical: tissue left behind can be refined in a small secondary adjustment, while tissue removed cannot be restored without complex reconstruction. So I plan margins generously, work in millimeters, and prefer to stage minor adjustments rather than chase a result with one aggressive cut. I also preserve the natural labial edge and the mucocutaneous junction unless you specifically request otherwise. Why that restraint matters so much, and what over-resection actually costs, is the subject of a separate article; here the point is narrower, that a few millimeters is a decisive planning matter rather than a minor detail.
-
Does the choice of instrument prevent unwanted results?
Far less than the quality of the plan does, and I want to be accurate about the evidence rather than convenient. The 2024 meta-analysis I cite above found that complication rates differ by technique and that the scalpel carried more bleeding, swelling and hematoma than laser, which runs against a blanket preference for any one instrument. What it concluded is that the method must be matched to the woman, which is a planning decision. My own preference for sharp, controlled technique rests on how the wound edge heals, and that reasoning, with the technique comparison, is on my main labiaplasty page. The decisive factors in my practice remain conservative margins, accurate mapping, nerve-sparing planning, and careful tissue handling, rather than the marketing around any particular device.
-
Why is staging a small second adjustment safer than one aggressive resection?
Because a second small adjustment removes a few millimeters from tissue that has healed and settled, whereas an aggressive first resection commits to a margin before anyone can see how the edge will sit. Swelling at surgery hides the final contour, and tissue retracts as it heals, so the only safe assumption at the first operation is to leave more. If, once everything has settled, you want a little more refinement, that is a minor procedure on a stable result. If too much was taken the first time, the only route back is reconstruction. I would rather plan for the small second step and rarely need it than plan for one cut and sometimes regret it.
-
How do selection and preparation reduce risk?
I treat confirming that you are the right candidate, and preparing you, as an integral part of prevention, not a formality. A thorough consultation establishes the anatomy, the functional and aesthetic goals, and whether expectations are realistic, and honest informed consent covers the real possibilities of asymmetry, sensation change, and revision. Preparation then focuses on what can be controlled: I address modifiable risks such as smoking with cessation several weeks beforehand, ensure medical conditions are stable, and screen for any tendency toward abnormal scarring. Setting these factors right before surgery gives healing the best possible starting point and heads off complications that no intraoperative skill can fully compensate for. In my experience, a well-selected, well-prepared woman with aligned expectations is far less likely to end up seeking correction later.
-
What do I measure before drawing the incision line?
Five things, with you both standing and lying down: the vestibular aperture, which sets the inner limit the line must never cross; the thickness and elasticity of the border, which tell me how the edge will settle; the projection and the edges that move, which fix where the margin sits when she is upright; the relationship of the clitoral hood to the planned contour, which decides whether hood reduction belongs in the plan; and the natural side-to-side difference, so each side gets its own margin and the result, not the resection, is symmetrical. Only when these are documented do I draw the line, and I draw it in millimeters rather than by eye.
-
How do I choose a surgeon who plans this carefully?
Look for a surgeon who treats the consultation as a genuine design process rather than a booking step. That means someone who examines you dynamically, measures and discusses your specific anatomy, talks openly about conservative margins and the trade-offs of removing tissue, and sets realistic expectations instead of promising a standard look. A careful surgeon will explain how they prevent specific problems — over-resection, asymmetry, sensation change — rather than simply reassuring you. Experience in intimate surgery matters, because it is the accumulated judgment that lets a surgeon design well for varied anatomy. I also suggest asking how a surgeon approaches asymmetry and revision, since thoughtful answers reveal a planning mindset. Ultimately, the surgeon’s willingness to prioritize function and anatomy over a quick, uniform result is the best sign of the design discipline that prevents complications.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
