

Table of content
- What are the key takeaways about nerve-sparing clitoral hood reduction?
- Why is the clitoral hood more than redundant skin?
- Where does the dorsal nerve of the clitoris run?
- How do I remove hood tissue without harming the nerve in Dubai?
- What are the steps of a nerve-sparing hood reduction?
- How much of the clitoral hood do I remove?
- Which mistakes in hood reduction cost sensation, and how do I avoid them?
- How do I design the hood together with the labia?
- Where can you read about each part of clitoral hood reduction and labiaplasty in Dubai in more depth?
- FAQs about clitoral hood reduction in Dubai
- Get appointment
This article covers how the hood reduction itself is performed around the nerve; whether the hood should be reduced at all, and what happens to its proportions when the labia are reduced and the hood is not, is covered in why the hood cannot be left out of a labiaplasty plan, the labiaplasty itself, with candidacy, recovery and risks, on labiaplasty in Dubai, and how the nerves of the labia themselves are protected in the neurovascular anatomy of labiaplasty.
What are the key takeaways about nerve-sparing clitoral hood reduction?
The dorsal nerve runs beneath the center of the hood, so I take the excess from the sides, keep the glans covered and design the hood with the labia as one unit.
- Hood reduction is a microsurgical, nerve-sparing procedure, not a simple skin trim.
- The dorsal nerve of the clitoris runs a mapped course beneath the center of the hood, and the plan is built around it.
- A lateral-based technique removes tissue from the sides, never from the midline.
- Only what the contour needs is removed; the glans stays covered, never exposed.
- The hood is the focal point of the vulvar aesthetic triangle, framed by the labia minora.
- It is usually performed as part of a labiaplasty, designed as one unit.
Why is the clitoral hood more than redundant skin?
The clitoral hood is more than redundant skin because it is a protective structure of specialized skin and connective tissue covering the clitoral glans, with the main sensory nerve of the clitoris bound into its framework. Its size and shape are as individual as a fingerprint, set by genetics, hormonal change, childbirth and aging. When the hood becomes elongated or overly full, it can cause three things:
- Reduced stimulation, because the glans is buried beneath more tissue than it needs.
- Hygiene difficulty, because folds that are too deep trap secretions.
- A look out of proportion to the labia minora, which is what most women notice first.
The real complexity lies beneath the surface. The dorsal nerve of the clitoris, the primary pathway for erotic sensation, runs along the top of the clitoral shaft, intimately bound to the hood’s connective tissue, so any reduction has to be mapped around it.
Where does the dorsal nerve of the clitoris run?
The dorsal nerves of the clitoris run along the top of the clitoral body, beneath the center of the hood, in a variable arc between the 10 and 2 o’clock positions rather than at two fixed points. That is the territory a central excision would endanger, and it is why tissue is taken from the sides.
This is grounded in anatomical study, not only in caution. A cadaveric dissection of the dorsal nerve of the clitoris in ten specimens, published in Aesthetic Surgery Journal, found the nerves larger than expected, 2.0 to 3.2 mm in diameter on average along the clitoral body, and mapped their course to that variable arc. Its authors state that knowledge of this anatomy is essential for safe genital surgery. It is an anatomical study rather than an outcomes study: it tells a surgeon where not to dissect, not how often injury occurs.
| Structure | Where it lies | What it means for the operation |
|---|---|---|
| Dorsal nerves of the clitoris | Along the top of the clitoral body, in a variable arc between the 10 and 2 o’clock positions | No dissection over the midline of the hood |
| Clitoral glans | Beneath the free end of the hood | The tissue that shelters it is preserved, so it is never exposed |
| Sides of the hood | Away from the course of the nerves | The only place excess tissue is removed from |
| Creases where the hood meets the labia minora | At the junction of the hood and the labia | Where the incisions are placed, so they are hidden in the natural folds |
How to read this table: the first two rows are what is protected and the last two are where the work is done; the whole technique follows from keeping those apart.
How do I remove hood tissue without harming the nerve in Dubai?
I remove hood tissue without harming the nerve by a lateral-based reduction: the excess is taken from the sides of the hood rather than from its central zone, so the silhouette is refined while no dissection crosses the course of the dorsal nerve. The incisions sit within the natural creases where the hood meets the labia minora, where they become virtually invisible once healed.
The distance between a satisfactory result and a lasting complication rests on this. Aggressive or anatomically careless approaches can cause permanent loss of sensation, painful hypersensitivity, or scarring that restricts the natural mobility of the clitoral complex. These are not aesthetic disappointments; they are functional injuries, and the lateral-based technique exists to make them avoidable.
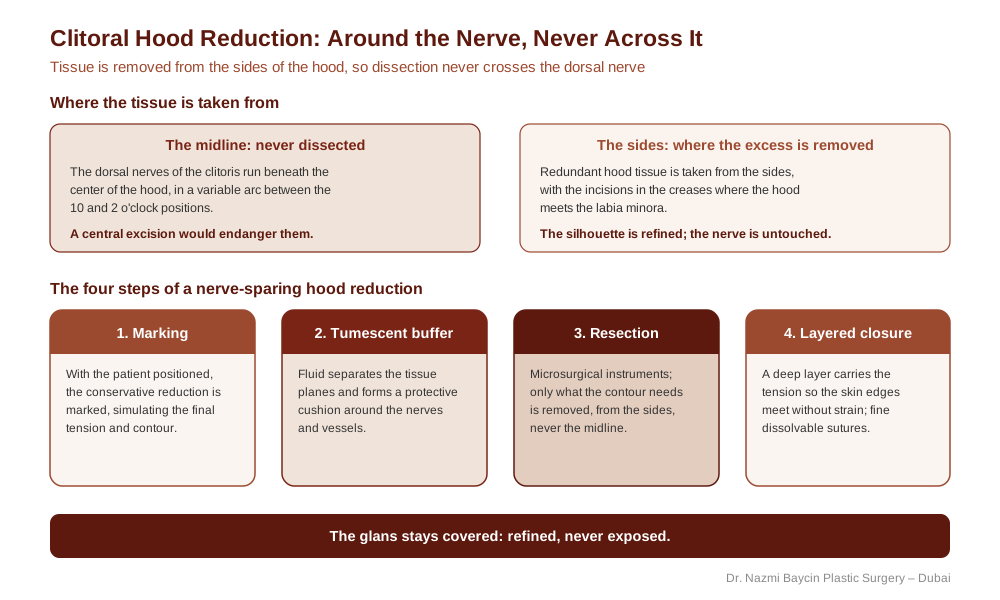
The nerve-sparing, lateral-based logic of clitoral hood reduction and its four steps, by Dr. Nazmi Baycin, Dubai.
What are the steps of a nerve-sparing hood reduction?
A nerve-sparing hood reduction runs in four steps: dynamic marking, a tumescent fluid buffer around the nerves, a conservative microsurgical resection from the sides, and a layered closure that carries the tension beneath the skin. Each step is organized around protecting the nerves and vessels while reaching a refined, natural contour.
| Step | What is done | What it protects |
|---|---|---|
| Dynamic marking | With you positioned, I mark the conservative reduction, simulating the final tension and contour and respecting your individual folds and pigmentation | Against removing more than the contour needs |
| Tumescent fluid | A tumescent solution numbs the area and separates the tissue planes, forming a cushion around the nerves and vessels before any tissue is removed | The nerves and vessels during dissection |
| Microsurgical resection | With microsurgical instruments, excess tissue is removed from the sides only, as conservatively as the aesthetic goal allows | The dorsal nerve, which is never crossed, and the tissue sheltering the glans |
| Layered closure | The wound is closed in several fine layers with dissolvable sutures; a deep layer carries the tension so the skin edges meet without strain | Against a widened scar and tethering of the hood |
How to read this table: the steps run in order, and the third column shows that each one guards against a different way the operation could go wrong; none can be skipped without losing that protection.
How much of the clitoral hood do I remove?
I remove only as much of the clitoral hood as the contour needs, and I always preserve the tissue that shelters the glans. Redundant bulk is taken from the sides, so the hood still covers what it exists to cover. Taking too much is the error I plan hardest against, because an over-exposed glans is uncomfortable rather than more sensitive, and it cannot be undone: tissue can be removed but never returned. Over-removal of the hood is among the results I am asked to correct after surgery elsewhere, and what can and cannot be rebuilt is set out in my article on correcting scarring and asymmetry after labiaplasty. The aim is never to expose the clitoris, but to let it sit in its natural, gently protected position within a more elegant frame.
Which mistakes in hood reduction cost sensation, and how do I avoid them?
The mistakes that cost sensation are the ones that bring the dissection, the heat or the tension onto the nerve: a central excision, deep dissection toward the shaft, cautery or laser over the midline, over-resection that exposes the glans, and a closure under strain. Each has a recognizable consequence, and each is avoided by a decision I make before or during the operation.
| Mistake | What it produces | How I avoid it |
|---|---|---|
| A central, midline excision of the hood | Dissection directly over the dorsal nerves; numbness or painful hypersensitivity | I remove tissue from the sides only; the midline is never dissected |
| Dissecting deep toward the clitoral shaft | Injury to the nerves bound into the connective tissue over the shaft | The tumescent cushion separates the planes, and I stay superficial to it |
| Cautery or laser over the course of the nerves | A zone of thermal injury where no cut should have been made | I cut with a scalpel and reserve any bleeding control for the sides, away from the midline |
| Removing enough to expose the glans | A glans that is uncomfortable rather than more sensitive, and cannot be re-covered | I mark conservatively with the tissue under its final tension and always keep the covering |
| Closing the skin under tension | A widened scar that tethers the hood and restricts its natural movement | A deep layer carries the tension so the skin edges meet without strain |
| Reducing the hood without regard to the labia | A hood that looks heavy or exposed against the new labia, with visible junctions | I design the hood and the labia as one unit, with the edges tapering into each other |
How to read this table: the first three rows injure the nerve directly and the last three injure the result; the middle column is what you might see after a hood reduction done without this discipline, and the right-hand column is my standard for preventing it.
How do I design the hood together with the labia?
I design the hood together with the labia as one unit, with the resection patterns drawn so that the new edges of the labia minora taper softly and continuously into the refined contour of the hood, with no visible junctions. The hood is the central focal point of the vulvar aesthetic triangle, framed by the labia minora, and in the majority of my cases its reduction is performed as an integral part of a labiaplasty rather than on its own, so that the whole anatomy looks refined as one, not altered in separate parts.
Whether the hood should be reduced at all, and why an unreduced hood does not stay as it was once its neighbors are smaller, is a decision in its own right that I cover in my article on why the hood cannot be left out of a labiaplasty plan. The same aesthetic-triangle thinking governs how I sequence intimate procedures together, in my article on combining a pubic lift with labiaplasty or vaginoplasty. This precision, placing your long-term physical and psychological well-being above any passing surgical trend, is the standard of my plastic surgery practice in Dubai.
Where can you read about each part of clitoral hood reduction and labiaplasty in Dubai in more depth?
This article covers how the hood reduction is performed; the pages below cover the decision around it and the labiaplasty it is usually part of.
- Whether to reduce the hood: why the hood cannot be left out of a labiaplasty plan
- The labiaplasty, candidacy, recovery and risks: the labiaplasty procedure page
- Diagnosing discomfort: how labial discomfort is diagnosed before surgery
- Sensation in the labia: the neurovascular anatomy of labiaplasty
- Sexual function: what labiaplasty means for sexual function
- Combining procedures: a pubic lift with labiaplasty or vaginoplasty
- Recovery: labiaplasty recovery week by week
- When a hood or labia were over-reduced elsewhere: correcting scarring and asymmetry after labiaplasty
FAQs about clitoral hood reduction in Dubai
-
Will a clitoral hood reduction affect my sensitivity?
A properly performed hood reduction should not diminish sensation, because protecting it is the foundation of the technique. The risk comes from operating over the center of the hood, where the dorsal nerves run in a variable arc between the 10 and 2 o’clock positions; the lateral-based technique avoids that territory entirely by removing tissue from the sides. Many women report improved stimulation afterward, because a hood that was burying the clitoris has been refined without the nerve ever being disturbed.
-
Does sensitivity change while the hood is healing?
It can, temporarily. Swelling in the first weeks can make the area feel more sensitive or, less often, duller than usual, and this settles as the swelling resolves. It is not a sign that the nerve has been affected, since the nerve is never in the field of dissection. The timing for resuming intimacy and the week-by-week course of healing are set out on the labiaplasty page and in my recovery article.
-
Will the clitoris look exposed after a hood reduction?
No. The aim is never to expose the clitoris but to let it sit in its natural, gently protected position within a more elegant frame. The tissue that shelters the glans is preserved in every case, because an over-exposed glans is uncomfortable rather than more sensitive and the change cannot be undone.
-
Can a clitoral hood reduction be done without labiaplasty?
It can, when the labia minora are already in proportion and only the hood is excessive, but in most of my cases the two are done together, because the hood and the labia form a single visual unit and the edges can then be designed to flow into each other. Whether your hood needs reducing at all depends on your proportions, which is the question my article on combining labiaplasty with hood reduction answers.
-
Where are the incisions, and will the scars show?
The incisions sit in the natural creases where the hood meets the labia minora, on each side, and never across the midline of the hood. Because they follow folds that are already there, and because the deep layer of the closure carries the tension, they heal as fine lines that are hard to find once the swelling has gone. When the hood is reduced with a labiaplasty, the lines continue into the labial edges, so there is no separate scar at the junction.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
