

Table of content
- What are the key takeaways about what makes the shape last?
- Which tissue carries the weight of the new breast?
- Why does relying on the skin fail?
- How is the internal brassiere built in Dubai?
- Why can the skin be draped without tension?
- What is the evidence for internal support?
- How is the sling scaled to the reduction?
- Why is the shape built inside, then covered?
- Which pages cover the rest of what holds a result?
- Which questions about lasting shape come up most often?
- Why does a shape held by the skin fail?
- What is the internal suspension sling?
- How does the sling keep the upper pole full?
- Does building an internal sling improve my scars?
- Is this different from a standard breast reduction?
- Is there evidence that internal support lasts?
- Will the internal sling work for a large reduction?
- How do you decide how much internal reconstruction I need?
- Get appointment
An internal suspension sling is a support built during a breast reduction from your own de-epithelialized dermis and parenchymal pillars and anchored to the pectoral fascia high on the chest wall, so that the sling, not the skin, carries the weight of the reshaped breast. When you come to me in Dubai for a breast reduction, your focus is understandably on relief and on size. What I spend most of my planning on is something you rarely ask about at first: what will hold the new shape in place once the swelling settles and the years pass.
A reduction that looks beautiful at three months but flattens within a few years has not succeeded. Lasting shape is an engineering problem, and the answer lies inside the breast, not on its surface. This article is about that internal architecture: the sling I build from your own tissue, the single element that most determines whether a result endures, and the part of the operation you never see.
This article covers one element of a breast reduction: the internal suspension sling, what it is made of, where it is anchored, how it is built and scaled, and the evidence for it. Why a result can relapse at all, the biology of tissue memory and skin elasticity, the patient factors and what you can do, is in why breast reduction results relapse. The operation, candidacy, recovery, risks and cost are on breast reduction in Dubai; how the pedicle sets projection and upper-pole fullness is in how pedicle selection shapes long-term outcomes; and how tension governs the scar is in breast reduction scarring.
What are the key takeaways about what makes the shape last?
The shape of a reduced breast lasts when something other than the skin carries its weight, so I build a sling from your own tissue, anchor it high to the chest wall and let the skin drape over it without tension.
- Lasting shape depends on who carries the load: the skin or an internal support.
- When the skin bears the weight, it stretches and the breast bottoms-out.
- An internal sling built from your own tissue carries the load instead.
- It is anchored to the pectoral fascia higher on the chest wall.
- The skin then drapes without tension, so scars stay fine.
- The shape is held by the construct, not the envelope.
This internal-support philosophy is central to how I work as an experienced plastic surgeon in Dubai. My aim here is not to cover every element of a reduction, but the one that governs longevity: the suspension construct that carries the load the skin should never be asked to bear.
Which tissue carries the weight of the new breast?
Either the skin envelope or an internal support, and the choice between them is the difference between a result that lasts and one that fails. Once tissue has been removed and the breast reshaped, something has to hold that shape against gravity. The first option is to tension the skin so it holds the mound in place. The second is to build an internal support that carries the weight, leaving the skin to simply cover it.
The skin is the weakest and most elastic tissue in the breast. Asking it to bear the structural load is asking the wrong tissue to do the work, and over time it stretches under that burden.
Why does relying on the skin fail?
Because skin was never built to be a load-bearing structure, so a shape held by skin is a shape on a deadline. When the skin is tensioned to hold the shape, two predictable failures follow:
- Bottoming-out: the tissue slides downward, the lower pole stretches and the upper pole empties, leaving exactly the flattened shape you hoped to avoid.
- Widened scars: under constant tension, the scars stretch and thicken rather than fading into fine lines.
How tension governs scar quality is a subject in its own right, covered in my article on how surgical technique impacts breast reduction scarring. Why some women’s tissue yields sooner than others’, and what else pulls a result down over the years, is in my article on why breast reduction results relapse. Here the point is the mechanical one: who carries the load.

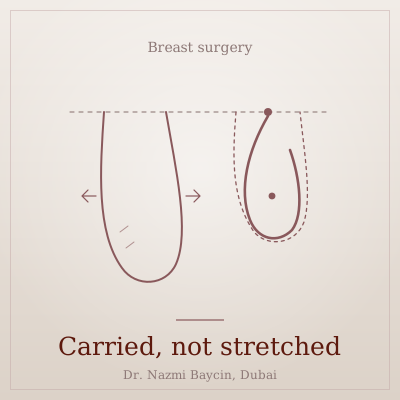
How an internal suspension sling, not the skin, carries the load and holds a reduced breast’s shape, by Dr. Nazmi Baycin, Dubai.
How is the internal brassiere built in Dubai?
From the tissue that a reduction would otherwise discard. After the reduction, rather than throwing away the de-epithelialized dermal tissue and the robust parenchymal pillars, I use them as the raw material for a suspension sling, an autologous internal brassiere shaped from the breast’s own structure.
This construct is then anchored to the pectoral fascia at a higher, pre-marked position on the chest wall. That fixation is what restores upper-pole fullness and holds it there, because the weight of the breast now hangs from a strong, fixed point rather than pulling on the skin. The tissue that would once have been removed becomes the scaffold that supports the result.
What are the four steps of building the sling?
The sling is built in four steps, in a fixed order, and the skin is closed only at the third.
| Step | What I do | What it achieves |
|---|---|---|
| 1. Shape the tissue | Keep the de-epithelialized dermis and the parenchymal pillars as the support material | A sling made of your own tissue, which integrates as living structure |
| 2. Anchor it high | Suture the construct to the pectoral fascia at a higher, pre-marked point on the chest wall | Upper-pole fullness, held from a fixed point rather than by the skin |
| 3. Drape the skin | Close the skin over the construct with no tension | A covering envelope rather than a load-bearing one; fine scars |
| 4. The shape endures | Nothing further: the sling, not the skin, now holds the breast | Resistance to the descent that empties the upper pole |
How to read this table: the second row is the one that decides the result, because where the sling is anchored is where the fullness will sit. The fourth row is not a step you see; it is what the first three were for.
The design of the pedicle that carries blood and sensation to the nipple is a related but separate decision, and one I keep distinct. How it shapes long-term outcomes is in my article on how pedicle selection shapes reduction results, and the safety of the nipple’s blood supply in my article on protecting nipple viability.
Why can the skin be draped without tension?
Because with the internal sling carrying the load, the skin is no longer a structural element; it is simply a cover, draped over a shape that is already built and secured beneath it. It can therefore be closed without tension, which is what allows the scars to mature into fine, discreet lines.
The incision pattern that lays this skin down is a choice of its own. Which pattern each degree of reduction needs is on my procedure page, and the trade-offs between a vertical and an anchor pattern in a lift are explained in my article on how skin quality and volume dictate the scar pattern. Whichever pattern is used, the principle holds: because the internal construct owns the shape, the skin closure is free of the tension that would otherwise widen the scar.
| Element | If the skin bears the load | If the internal sling bears the load | Why it matters |
|---|---|---|---|
| Upper pole | Empties as tissue descends | Stays full, anchored high | Upper-pole fullness reads as youthful |
| Longevity | Flattens within a few years | Holds shape over the long term | The result ages with you |
| Scars | Widen under tension | Stay fine, closed tension-free | Scar quality reflects the load path |
| What holds the shape | The stretching envelope | The fixed internal construct | Structure, not skin, decides the result |
How to read this table: the last row causes the first three. Decide who carries the load and the upper pole, the longevity and the scars follow from it.
What is the evidence for internal support?
Two studies support the principle: a series describing essentially this dermal construct with sustained projection at sixteen months, and a ten-year randomized trial in which suspension to the chest wall measurably reduced the descent of the breast tissue. This is not merely a matter of surgical preference.
A published account of the dermal suspension sling describes triangular dermal flaps taken from tissue that would ordinarily be discarded, de-epithelialized and fixed to the chest wall to give the reshaped breast a structural foundation, with the mound then firm enough for the skin to drape over it under minimal tension. Across 66 reductions the authors report that projection and shape were sustained through follow-up, though at a median of around sixteen months that series speaks to the early years rather than to decades.
A ten-year randomized comparison of chest-wall suspension marked the reshaped breast tissue with titanium clips and tracked their position radiographically for a decade, finding significantly less downward migration in the supported breasts than in the unsupported controls. The support tested there was a pectoralis muscle loop rather than the dermal construct I build, and the trial was small, twenty-one patients in total. What it establishes is the principle rather than any single technique: suspension anchored to the chest wall measurably resists the descent that skin alone cannot.
What does each study show, and what can it not?
The series shows the construct; the trial shows the principle over ten years; neither shows my exact technique over decades.
| Study | Design and size | Support tested | What it shows | What it cannot show |
|---|---|---|---|---|
| Dermal suspension sling series, 2011 | Case series, 66 reductions, median follow-up about sixteen months | De-epithelialized dermal flaps fixed to the chest wall | Projection and shape sustained; skin draped under minimal tension | Results beyond the early years; no comparison group |
| Chest-wall suspension trial, 2016 | Randomized, 21 patients, ten-year radiographic follow-up with titanium clips | A pectoralis muscle loop | Significantly less downward migration of the breast tissue than without suspension | The dermal construct specifically; a small trial |
How to read this table: the first row is closest to what I build and the second is the longest and best-controlled follow-up; together they show the material and the principle, which is why I treat internal support as structural rather than optional.
How is the sling scaled to the reduction?
The sling is scaled to the load it will carry, so a large reduction gets a robust suspension and a light one a more modest internal reshaping. A woman seeking a large reduction for long-standing physical symptoms needs a construct built to carry substantial weight. A lighter, proportion-focused reduction, the one-cup operation I describe in my article on the mini reduction for athletic patients, calls for less.
What does not change is the principle. Whatever the volume removed, the shape that remains should be held by an internal support, not by a tensioned skin envelope. Reading your tissue and building the right sling for it is the part of the planning that most determines how the result will look in ten years.
Why is the shape built inside, then covered?
Because removing breast tissue is the straightforward part of a reduction, and rebuilding the internal support that holds the reshaped breast is the part that takes judgment and time. It is what separates a shape that lasts decades from one that flattens within a few years.
When the result is built from the inside, a strong internal construct carrying the load and the skin merely draped over it, the breast keeps its fullness, ages gracefully with you, and holds the relief and the shape together. That, to me, is what a modern reduction should deliver: not just a smaller breast, but a lasting one.
Which pages cover the rest of what holds a result?
This article covers only the internal sling; the pages below cover why results relapse, the pedicle, the scars, the operation and the other breasts the same principle holds.
- The operation, candidacy, recovery, risks and cost: the breast reduction procedure page
- Why a result can lose shape over time, and what you can do: why breast reduction results relapse
- The pedicle and long-term shape: how pedicle selection shapes long-term outcomes
- How the scar is built to heal as a fine line: breast reduction scarring and surgical technique
- The nipple’s blood supply and the prevention of necrosis: nipple-areola complex safety in breast reduction
- The one-cup reduction, where the sling is lightest: the mini breast reduction
- The same principle in a lifted breast after weight loss: breast lift after massive weight loss
- How skin quality and volume decide a lift’s scar pattern: vertical versus anchor scar patterns in breast lift
Which questions about lasting shape come up most often?
-
Why does a shape held by the skin fail?
Because skin is the weakest and most elastic tissue involved, so when the envelope is tensioned to hold the breast in place it gradually stretches. As it stretches, the breast bottoms-out: the tissue slides downward, the lower pole lengthens, and the upper pole empties. The result is the flattened shape you were trying to get away from in the first place. My approach is never to rely on the skin for support. I build an internal sling from your own tissue to carry the load, so the shape is held by a structure that does not stretch the way skin does. The other forces that act on a result over the years, your tissue’s memory, your skin’s elasticity, weight change and pregnancy, are the subject of my article on why results relapse.
-
What is the internal suspension sling?
It is an internal support I construct from your own tissue during the reduction, essentially an autologous internal brassiere. Rather than discarding the de-epithelialized dermal tissue and the firm parenchymal pillars, I use them as the material for the sling. I then anchor this construct to the pectoral fascia at a higher point on the chest wall. That fixation is what lifts and holds the upper pole, because the weight of the breast now hangs from a strong, fixed point rather than pulling on the skin. The elegance of it is that the tissue which would normally be thrown away becomes the scaffold that supports the whole result. The shape is built from the breast’s own structure, which is why it integrates so naturally.
-
How does the sling keep the upper pole full?
Upper-pole fullness is one of the first things to disappear when a breast bottoms-out, so holding it is a central goal. The sling achieves this by anchoring the breast tissue high on the chest wall, at a pre-marked position, rather than letting it settle downward. Because the construct is fixed to the strong pectoral fascia, it keeps the volume distributed higher on the breast, where it reads as youthful and full. The support resists the gravitational descent that would otherwise empty the upper pole over time. This is very different from relying on the skin to hold that fullness, which never lasts. By building the fullness into the internal structure, I make it a durable feature of the result rather than a temporary one.
-
Does building an internal sling improve my scars?
Yes, indirectly but significantly. Once the internal sling is carrying the load, the skin no longer has to. It becomes a cover draped over a shape that is already built and secured beneath it, so it can be closed without tension. Tension is the enemy of a fine scar. When skin is stretched tight to hold a shape, the resulting scars tend to widen and thicken; when it is closed loosely over a supporting structure, they can mature into fine, discreet lines. So the internal support serves two purposes at once: it holds the shape, and it protects the scars by taking the load off the skin. The quality of the scar is really a reflection of whether the skin was asked to bear weight it should not.
-
Is this different from a standard breast reduction?
The tissue removal is similar; the difference is in what happens to the shape afterward. Many techniques still rely substantially on the skin envelope to hold the breast, which is why a proportion of reductions flatten or bottom-out over the years. My emphasis is on the internal reconstruction, the suspension sling that carries the load independently of the skin. This is the part of the operation that takes the most planning and time, and it is where the longevity of the result is decided. So while any reduction can make a breast smaller, not every reduction is built to keep its shape. The distinction I draw is between removing tissue and rebuilding support, and I consider the second part just as important as the first.
-
Is there evidence that internal support lasts?
Yes, and the most useful evidence comes from imaging rather than photographs. In a ten-year randomized study, twenty-one women had a vertical reduction and the reshaped breast tissue was marked with titanium clips so its position could be tracked on radiographs. The breasts given an internal chest-wall suspension showed significantly less downward migration over that decade than the unsupported ones. Two honest caveats: the trial was small, and the support used was a pectoralis muscle loop rather than the dermal construct I build, so it does not validate my exact technique. What it does test, objectively and over a long follow-up, is the underlying principle, that suspension anchored to the chest wall holds the shape where the skin alone does not. That matches what I see in my own practice, which is why I treat internal support as structural rather than optional.
-
Will the internal sling work for a large reduction?
Yes, and in fact the larger the reduction, the more important the internal support becomes. A bigger breast places more load on whatever is holding it, so relying on the skin is even riskier when a substantial volume is involved. For a large reduction, I build a correspondingly robust suspension, scaled to carry the greater weight. For a lighter, more proportion-focused reduction, the internal reshaping is more modest. The construct is always matched to the load it will need to support. What stays constant is the principle: the shape should hang from a strong internal structure, not from the skin. Scaling the sling to the reduction is simply a matter of building the right amount of support for each individual breast.
-
How do you decide how much internal reconstruction I need?
I base it on your tissue and your goals. During the consultation I assess how much volume needs to be removed, the quality and character of your breast tissue, and the shape you are hoping to achieve, because all of these determine how much support the result will require. From that assessment I plan the suspension: how much dermal and parenchymal tissue to preserve for the sling, and where on the chest wall to anchor it. The heavier the breast and the more upper-pole fullness you want to hold, the more robust the construct needs to be. The reason I plan it this carefully is that the internal support is what determines how your result will look years from now. Choosing a surgeon really means finding someone who treats the lasting shape as an engineering task, not just the removal of tissue.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
