

Table of content
- What are the key takeaways about pedicle selection?
- Why is the pedicle a shaping decision, not only a safety one?
- How does the superomedial pedicle support projection and upper-pole fullness?
- When does the inferior pedicle make sense, and what shape does it give?
- Why do two successful reductions in Dubai age differently?
- Which features of your breast push the pedicle choice one way or the other?
- How does the pedicle relate to the other decisions of a reduction?
- How should the pedicle be chosen for a shape that lasts?
- Which pages cover the rest of what the pedicle touches?
- Which questions about pedicle selection come up most often?
- What is a pedicle, and why does it decide the shape?
- What is the difference between a superomedial and an inferior pedicle?
- Does the pedicle choice really affect my long-term shape?
- What is bottoming-out, and how does the pedicle affect it?
- Is one pedicle safer for the nipple than the other?
- Which pedicle gives more upper-pole fullness?
- Can any patient have a superomedial pedicle?
- How do you decide which pedicle to use for me?
- Get appointment
I want this article to stay on the aesthetic side of that choice: how the pedicle governs projection, upper-pole fullness and how well the breast resists bottoming-out over the years. Understanding the pedicle is what explains why two technically successful reductions can age so differently.
This article covers one thing: how the pedicle decides the long-term shape of a reduced breast. The operation, candidacy, recovery, risks and cost are on breast reduction in Dubai. How the pedicle is chosen to protect nerve supply and sensation is in nipple sensation and pedicle choice, and how nipple blood supply is protected against necrosis is in nipple-areola complex safety. Why a result can relapse through tissue memory and skin elasticity is in why breast reduction results relapse, and the scars are covered in breast reduction scarring.
What are the key takeaways about pedicle selection?
Both pedicles keep the nipple alive, so I choose between them for the shape each one will hold, and that choice is made before any tissue is removed.
- The pedicle choice is made before any tissue is removed.
- Both pedicles reliably keep the nipple alive, so safety rarely separates them.
- The superomedial pedicle supports projection and upper-pole fullness.
- The inferior pedicle gives a fuller lower pole and a robust blood supply.
- Superomedial tends to resist bottoming-out better over the years.
- The real long-term difference is shape and durability, not viability.
This shape-first way of thinking about the pedicle is central to how I work as a plastic surgery specialist in Dubai. My aim here is not to walk you through the whole operation. It is to explain the single decision that most determines how your reduction will look a decade later.
Why is the pedicle a shaping decision, not only a safety one?
Because both pedicles meet the safety baseline, what separates them over the years is the arrangement of the tissue they leave behind. The pedicle’s first job is to keep the nipple and areola alive by carrying their blood supply, and both the superomedial and the inferior pedicle do this reliably in experienced hands. Safety is therefore rarely the deciding factor between them, a point worth making because it is often assumed to be the whole story.
What actually separates the two is aesthetic: how the remaining tissue is arranged, how much the breast projects, and how well it holds that shape. This is why I treat the pedicle as the first shaping decision of the operation. The nipple’s blood supply and its nerves are subjects I address separately, in my articles on protecting nipple viability and on how the pedicle protects nipple sensation. Here the focus is shape.
Once safety is set aside as a shared baseline, the pedicle governs three things that decide the long-term look:
- Projection: how forward and lifted the breast sits after healing.
- Upper-pole fullness: the gentle upper slope that reads as youthful.
- Shape retention: how well the breast resists bottoming-out over the years.
How does the superomedial pedicle support projection and upper-pole fullness?
The superomedial pedicle preserves the upper-inner quadrant of the breast, and that preserved tissue is exactly what holds a lifted, projecting shape. It draws the nipple’s blood supply from above and toward the center of the chest, so the tissue that stays is the tissue that sits high. Because the upper-inner tissue is kept, this pedicle also lets me reshape the remaining breast into a higher position and secure it there.
The research supports this. A comparative study of long-term breast shape after pedicle selection measured 58 women over a two-year follow-up and found:
- The lower pole lengthened by 29.5 percent in the superomedial group against 40.9 percent with an inferior pedicle.
- Recurrent drooping at twenty-four months averaged 2.2 cm compared with 3.9 cm.
- Aesthetic scores were higher from both patients and surgeons, at equal complication rates.

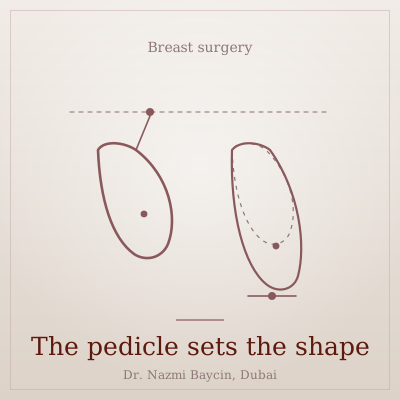
How the superomedial and inferior pedicles differ in shape, projection, and long-term retention, by Dr. Nazmi Baycin, Dubai.
When does the inferior pedicle make sense, and what shape does it give?
The inferior pedicle makes most sense when the nipple has to travel a long way, because its blood supply from the lower chest wall is particularly robust. In very large reductions, where a dependable supply is paramount, that robustness is the reason to choose it. How I match technique to the very largest breasts, including when a pedicle is no longer enough, is in my article on surgical solutions for gigantomastia.
Aesthetically, the inferior pedicle tends to give a softer, fuller lower pole, usually with somewhat less upper-pole fullness than the superomedial. Its trade-off is over time. Because the supporting tissue sits low, this pedicle is more prone to lower-pole elongation and bottoming-out in the years after surgery, particularly in larger reductions. It remains an excellent, dependable technique. The point is simply that the pedicle choice carries a long-term shape consequence, not just an immediate one.
Why do two successful reductions in Dubai age differently?
Two reductions that both look good at three months can look quite different at five years, largely because of where each pedicle anchors the supporting tissue. The immediate result is only part of the picture. How the shape holds is the other part, and that is decided by where the tissue that carries the breast sits.
| Consideration | Superomedial pedicle | Inferior pedicle | Why it matters long-term |
|---|---|---|---|
| Blood supply from | Above and central | Lower chest wall | Both reliable; inferior favored for long nipple travel |
| Upper-pole fullness | Well supported | Somewhat less | Sets the youthful upper slope |
| Projection | Strong, lifted | Fuller lower pole | Defines the silhouette that lasts |
| Bottoming-out over years | More resistant | More prone | Determines how the shape ages |
How to read this table: the first row is where the two pedicles are equal, and the next three are where they differ. Read down the last column and you have the reason the pedicle is a shaping decision: the tissue is anchored where the blood supply enters, and that anchoring either holds or loses the shape.
What do the follow-up studies show about each pedicle?
Two follow-up studies, one measured and one survey-based, both place the difference between the pedicles on shape rather than on safety. A long-term follow-up study of superomedial versus inferior pedicle reduction found projection and contour more satisfactory with the superomedial pedicle, while nipple sensation was comparable between the two in that series. Pooled data elsewhere link the superomedial pedicle to more reduced sensation, a question I take up in my article on nipple sensation and pedicle choice; here the sensation rows are shown only to separate shape from safety.
| Measure | Superomedial | Inferior | Source |
|---|---|---|---|
| Lower-pole lengthening at 24 months | 29.5 percent | 40.9 percent | Sapino et al. 2021, 58 women |
| Recurrent drooping at 24 months | 2.2 cm | 3.9 cm | Sapino et al. 2021 |
| Aesthetic score, surgeons and patients | 7.7 and 8.6 out of 10 | 6.7 and 7.5 out of 10 | Sapino et al. 2021 |
| Secondary procedures and nipple loss | 14 percent; none | 14 percent; none | Sapino et al. 2021 |
| Projection and contour at late follow-up | More satisfactory | Less satisfactory | Makboul et al. 2017, 60 women |
| Nipple sensation at late follow-up | Comparable in this series | Comparable in this series | Makboul et al. 2017 |
How to read this table: the first three rows are the shape rows and all favor the superomedial pedicle; the fourth and sixth rows are the safety rows and show no difference in these two studies, although larger pooled data on sensation do, which is the sensation article’s subject. Both studies are small and from single centers, so take them as the direction of the difference rather than its exact size.
Is bottoming-out the same as relapse?
No. Bottoming-out is the part of a result’s decline that the pedicle governs, and relapse is the broader loss of shape driven by your own tissue. Bottoming-out means the lower pole gradually lengthens and the breast drops below the nipple, and the pedicle influences it because the pedicle decides where the breast’s weight is carried. Relapse adds the forces the pedicle cannot control: tissue memory, skin elasticity, weight change and pregnancy.
I cover those forces in my article on why breast reduction results relapse, and the internal sling that resists them in why an internal suspension sling makes a reduction last. Here the point is narrower: of all the decisions that resist descent, the pedicle is the one made first.
Which features of your breast push the pedicle choice one way or the other?
Four features of your breast decide which pedicle I choose, and the distance the nipple has to move is the one that most often overrides the others. The superomedial pedicle is my frequent preference for its shape and longevity, but it is not right for every breast.
| Feature | Favors superomedial | Favors inferior | Why |
|---|---|---|---|
| Distance the nipple must move | Short to moderate | Very long | A long move stretches a pedicle; the inferior supply tolerates it best |
| Size of the reduction | Small to large | Very large | The largest reductions make a dependable supply the first priority |
| Quality of the tissue | Firm, well-perfused | Thin or poorly perfused | Weaker tissue needs the wider, more robust base |
| Shape you want | Lifted, full above | Soft, full below | Each pedicle leaves its tissue where its fullness will be |
How to read this table: the first two rows are about safety and can veto the last two, which are about shape. When the first two rows allow either pedicle, the last two decide, and for most of my patients that points to the superomedial.
How does the pedicle relate to the other decisions of a reduction?
The pedicle governs the internal architecture and the shape, and the closure governs the surface. Choosing the pedicle for shape does not stand alone; it sits alongside the other decisions of a reduction. How the incisions are planned and closed to give the finest possible scar is a separate consideration, which I discuss in my article on how surgical technique shapes breast reduction scarring.
Together, the pedicle, the tissue reshaping and the closure make up a single coordinated plan. If you would like to see how these elements come together for your anatomy, you can read my procedure page for breast reduction surgery in Dubai. My purpose here is simply to establish that the pedicle is what most determines the long-term shape.
How should the pedicle be chosen for a shape that lasts?
It should be chosen for the shape it will hold, not treated as a technical detail that only concerns healing. Thinking about the pedicle as a shape-and-longevity decision changes the whole conversation. Instead of asking only how much to remove, the better question is how the breast should be built to hold its shape over the years, and the pedicle is the first answer to that question.
A breast reduction result is the product of a safe technique and a durable design. A safe reduction is the baseline; a shape that endures is what the pedicle decision protects.
Which pages cover the rest of what the pedicle touches?
This article covers only the pedicle’s effect on shape; the pages below cover the operation, the nipple, the scars and the other reasons a result can change.
- The operation, candidacy, recovery, risks and cost: the breast reduction procedure page
- The pedicle and nipple sensation: how pedicle choice affects nerve preservation
- Nipple blood supply and the prevention of necrosis: nipple-areola complex safety in breast reduction
- The internal sling that carries the load the skin should not: why an internal suspension sling makes a reduction last
- Why a result can relapse through tissue memory and skin: why breast reduction results relapse
- How the scar pattern is chosen and heals: breast reduction scarring and surgical technique
- The very largest breasts, where the pedicle itself may not be enough: surgical solutions for gigantomastia
Which questions about pedicle selection come up most often?
-
What is a pedicle, and why does it decide the shape?
The pedicle is the bridge of tissue that stays attached to the nipple and areola during a reduction, carrying their blood supply and much of their sensation. When tissue is removed, the nipple is not detached; it is kept alive on this pedicle and repositioned higher. Its first job is to keep the nipple healthy, and both the main pedicle types do that reliably. But the pedicle also determines where the remaining breast tissue is anchored. That second role is what I focus on when I plan, because where the tissue is anchored is what sets the projection and how well the breast holds its shape over the years. So the pedicle is both a lifeline and a shaping tool, and it is the shaping side that most affects the long-term look.
-
What is the difference between a superomedial and an inferior pedicle?
They differ mainly in where the nipple’s blood supply comes from, and that difference has aesthetic consequences. The superomedial pedicle draws its supply from above and toward the center of the chest, preserving the upper-inner tissue. The inferior pedicle draws from the lower chest wall. Because the superomedial preserves the upper-inner quadrant, it tends to support more projection and upper-pole fullness and to hold that shape better over time. The inferior gives a fuller lower pole and a very robust blood supply, which is valuable when the nipple must travel a long way. So the choice is not about one being safe and the other not; both are safe. It is about which arrangement of tissue gives the shape that suits you and lasts. I choose between them based on your anatomy and the result we are aiming for.
-
Does the pedicle choice really affect my long-term shape?
Yes, more than most people expect. The pedicle decides where the supporting tissue sits, and that in turn decides how the breast projects and how it resists sagging over the years. Comparative research bears this out: the superomedial pedicle tends to preserve upper-pole fullness and resist the gradual bottoming-out that can affect inferior-pedicle results, especially in larger reductions. Two reductions that look similar at first can diverge over five or ten years largely because of this. This is exactly why I do not treat the pedicle as a routine technical choice. It is one of the main determinants of how your reduction will look years from now, so I choose it deliberately for the shape I want your breast to hold, not just for the immediate result.
-
What is bottoming-out, and how does the pedicle affect it?
Bottoming-out is when the lower part of the breast gradually descends and elongates after surgery, so that too much tissue sits below the nipple and the shape drops over time. It is one of the main ways a good early result can deteriorate. The pedicle influences this because it determines where the breast’s weight is supported. An inferior pedicle, with its tissue based low on the chest, can be more prone to this descent in larger reductions, whereas the superomedial pedicle, preserving upper-inner tissue, tends to resist it. When I plan a reduction, anticipating bottoming-out is part of the pedicle decision. The other forces that pull a result down, your skin’s elasticity, tissue memory and weight change, and the internal support that resists them, are the subject of my article on why results relapse.
-
Is one pedicle safer for the nipple than the other?
In experienced hands, both the superomedial and inferior pedicles are safe and reliable for keeping the nipple alive, which is why I rarely frame the choice as one of safety. Studies comparing them find comparable nipple survival; on sensation the evidence is mixed, with pooled data favoring the inferior pedicle, which I cover in my article on nipple sensation. The inferior pedicle’s blood supply is especially robust, which is why I may favor it when the nipple has to be moved a very long distance in a very large reduction. But that is a matter of matching the technique to the magnitude of the reduction, not one pedicle being generally unsafe. How the blood supply is protected against necrosis, and how the nerves are protected for sensation, are each important enough that I address them in their own articles. For the pedicle decision itself, safety is the baseline both techniques meet, and shape is what distinguishes them.
-
Which pedicle gives more upper-pole fullness?
The superomedial pedicle generally gives more upper-pole fullness. Because it preserves the tissue of the upper-inner quadrant, it supports that gentle fullness in the upper part of the breast that reads as lifted and youthful. The inferior pedicle tends to concentrate fullness lower down, giving a softer, fuller lower pole but usually a little less in the upper pole. Neither is right or wrong; they simply create different shapes. Which one suits you depends on your starting anatomy and the look you want. If upper-pole fullness and a lifted projection are the priority, the superomedial often serves that well. Part of my role in the consultation is to match the pedicle to the shape you are hoping for, within what your anatomy allows.
-
Can any patient have a superomedial pedicle?
Not always, and that is why the choice is individual. The superomedial pedicle is my frequent preference for its shape and longevity, but in very large reductions, where the nipple must travel a long distance, the inferior pedicle’s robust blood supply can make it the safer and more sensible option. So the magnitude of the reduction, your existing anatomy, and how far the nipple needs to move all influence which pedicle is appropriate. It is a judgment made for each patient rather than a fixed rule. What I always do is weigh the shape advantages of one option against the practical demands of your particular reduction. The goal is the best lasting shape that can be achieved safely for your specific anatomy, which sometimes means the superomedial and sometimes means the inferior.
-
How do you decide which pedicle to use for me?
I start from your anatomy and the result we are aiming for. I assess the size of the reduction, how far the nipple needs to move, the quality of your tissue, and the shape and projection you want to end up with. From there I choose the pedicle that best delivers a lasting shape within a safe operation. For many patients that is the superomedial, for its projection and resistance to bottoming-out; for very large reductions it may be the inferior, for its dependable blood supply. The reason I plan it this way is that, in my experience, the pedicle decision is one of the strongest determinants of how a reduction looks years later. Choosing a surgeon really means finding someone who selects the pedicle deliberately for your long-term shape, rather than applying the same technique to everyone.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
