

Table of content
- What are the key takeaways about wide-set breasts and cleavage in Dubai?
- Why can cleavage not be forced on wide-set breasts?
- What are the four pillars of planning for wide-set anatomy?
- How is the cleavage kept stable over the years?
- What is the difference between creating cleavage and compressing it?
- How much can augmentation narrow a wide gap?
- What should you ask a surgeon about wide-set correction?
- Where can you read about each part of breast augmentation planning in more depth?
- FAQs about wide-set breasts and cleavage in Dubai
- Can breast augmentation fix wide-set breasts and create cleavage?
- Why can’t cleavage simply be forced closer together?
- What is symmastia, and how is it avoided?
- Why does implant base width matter more than size for wide-set breasts?
- What implant profile is best for wide-set anatomy?
- Will the cleavage look natural, or like a push-up bra?
- Will the cleavage result last, or will it drift over time?
- How do I know if my expectations for wide-set correction are realistic?
- Get appointment
What are the key takeaways about wide-set breasts and cleavage in Dubai?
The gap between wide-set breasts is set by the sternum and the medial pectoral attachments, so natural cleavage is created by matching the implant to the chest and opening the medial pocket only as far as that boundary allows, never by cutting past it.
- Wide-set breasts have a broad intermammary gap set by tight medial pectoral fibers and a fixed sternal border.
- Cleavage cannot be forced: an aggressive medial release breaches the sternal boundary and destabilizes the result.
- Over-release risks symmastia, implant migration, and rippling, which are difficult to reverse.
- The published series on symmastia point to detachment of the pectoralis from the sternum and an oversized base diameter as the usual causes.
- Implant base width, matched to the chest, matters more than volume or profile for this anatomy.
- A moderate or moderate-plus profile usually fills the cleavage zone better than a high profile.
- The goal is organic medial fullness present without a push-up bra: creation, not compression.
The wider aim throughout is stability. A cleavage that looks good on the operating table but drifts within a year is not a success. Everything below is about building a result that holds within the limits the chest wall sets.
This article covers the anatomy of wide-set breasts and how the medial boundary, implant base width, and profile are planned to create natural cleavage. For candidacy, incisions, implant placement, recovery, risks, and cost, see my breast augmentation in Dubai page; for how every boundary of the pocket is built and anchored, see my article on implant pocket control; for how base width and projection shape the breast in general, see my article on how implant dimensions shape the result.
Why can cleavage not be forced on wide-set breasts?
Because the structures that hold the breasts apart are fixed anatomy, not soft tissue that can be pushed aside. Wide-set breasts are a common anatomical variation, and many women seek augmentation not only for volume but for a more centered, balanced cleavage line. To understand why this is delicate, you have to look at the internal landscape rather than the surface.
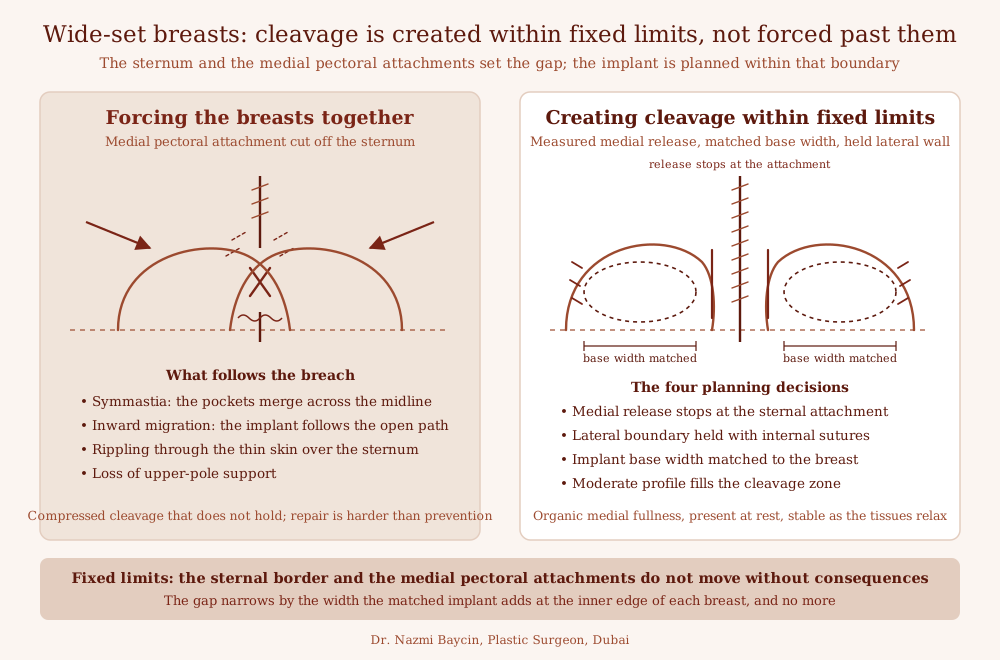
Cleavage for wide-set breasts is created within the chest wall’s fixed limits, not forced past them, by Dr. Nazmi Baycin, Dubai.
What sets the width of the gap between the breasts?
Two structures set the limit. The medial fibers of the pectoralis major muscle attach firmly along the breastbone, and the sternal border itself forms a solid, fixed boundary. Together they define how close the breasts can naturally sit. That boundary is not a suggestion; it is anatomy, and it does not move without consequences.
In a wide-set chest the breast footprints simply start further from the midline than average. The skin over the sternum is thin, with little gland or fat beneath it, so nothing soft is available to fill that space. Any fullness that appears there has to come from the implant sitting at the inner edge of its own footprint, not from tissue moved across the midline.
What happens when the medial boundary is breached?
The construct loses its inner wall, and the implant follows the path of least resistance toward the midline. This is where the most consequential error in wide-set surgery happens. In an attempt to close the gap, some surgeons aggressively release the medial pectoral fibers to force the breasts together. That release breaches the natural boundary and destabilizes everything built on it.
The consequences are difficult to reverse. Symmastia, where the implant pockets merge across the midline, is the most visible. Inward implant migration, rippling that shows through the thin skin over the sternum, and loss of upper-pole support follow the same breach. Each of these is a repair problem, and the repair is far harder than the prevention.
What does the published evidence on symmastia show?
That the breach usually happens at the sternum, and that it happens during augmentation rather than afterward. A 2019 review of 23 iatrogenic symmastia cases in the Aesthetic Surgery Journal lists the commonly cited causes: over-dissection of the medial pocket over the sternum, disruption of the midline sternal fascia, an oversized implant base diameter, and over-dissection of the medial pectoralis attachments to the sternum. Every patient in the series had previously undergone a subpectoral augmentation, and the authors conclude that symmastia most often follows the pectoralis major detaching from the sternum during that operation. Their survey of 91 plastic surgeons pointed the same way, with most respondents attributing the cases they saw to over-dissection of the medial pectoral attachments.
Two of those named causes are design decisions, which is the point of this article. The release of the pectoralis at the sternum is the medial boundary, and the base diameter is the implant choice. The series is a single-surgeon retrospective review supported by a member survey, so it describes what the cases had in common rather than proving causation. It is still a clear warning that the midline is where wide-set cleavage goes wrong.
What are the four pillars of planning for wide-set anatomy?
A measured medial release, a held lateral boundary, a base width matched to the breast, and a profile that fills rather than projects. Achieving natural cleavage for wide-set breasts is an exercise in controlled, balanced engineering, and these four principles guide the plan. This is the technical layer that sits beneath the standard operation.
How far is the medial pocket opened, and where does it stop?
It is opened only as far as the implant needs to provide subtle medial fullness, and it stops at the sternal attachment of the pectoralis. The release of the lower medial fibers must be meticulous and measured. I treat the sternal attachment as an immutable landmark rather than a limit to be negotiated. This precision is exactly what prevents the internal drift that leads to symmastia.
The practical consequence is that the medial edge of the pocket is set by anatomy, not by the cleavage you hope for. The implant’s inner edge comes to rest where the breast footprint ends, and the gap narrows by the amount the matched implant fills. Nothing is gained by cutting further, and the series above shows what is lost.
Why does the lateral boundary matter for a wide gap?
Because an implant that drifts outward widens the gap it was placed to close. An over-dissected lateral pocket lets the implant slide toward the armpit over time, which worsens the wide-set appearance rather than improving it. For this anatomy the outer wall of the pocket is therefore held deliberately, with the implant centered on its footprint where it belongs.
The lateral stay sutures and the pocket-to-implant matching that hold that wall are part of my general pocket method, which I set out in my article on implant pocket control. What is specific to wide-set breasts is the reason: every millimeter of outward drift is a millimeter added back to the gap.
Why does implant base width matter more than volume?
Because width is what reaches toward the midline, and volume is not. For wide-set anatomy the implant’s base diameter is the paramount decision, more important than profile or volume. The base width must match the natural breast width. Too narrow, and a gap remains; too wide, and the tissues are strained, risking a double bubble or lateral bulging.
An oversized base is also one of the named causes of symmastia, so the match works in both directions. The correct width delivers a seamless transition and a natural inner contour. How base width and projection interact in general, and why two implants of the same volume shape the breast differently, is covered in my article on how implant dimensions shape the result.
Which implant profile fills the cleavage zone rather than projecting past it?
Usually a moderate or moderate-plus profile. High-profile implants project forward more than they widen, which can actually emphasize the separation when the breasts sit wide apart. A moderate profile distributes the same volume across a broader base, gently filling the cleavage zone rather than producing an artificial, projecting look. The exact choice still follows the measurements, because a very narrow chest can need a higher profile to avoid an over-wide base.
| Surgical decision | Wide-set anatomy calls for | Why it matters |
|---|---|---|
| Medial pocket release | Measured, stopping at the sternal attachment | Over-release detaches the pectoralis from the sternum and leads to symmastia |
| Lateral boundary | Held with internal sutures | Prevents outward drift that widens the gap again |
| Implant base width | Matched to the natural breast width | Fills the gap without straining tissue; an oversized base is a named cause of symmastia |
| Implant profile | Moderate to moderate-plus, in most cases | Fills the cleavage zone instead of projecting away from it |
How to read this table: the first two rows are pocket decisions and the last two are implant decisions, and the plan fails if either pair is right while the other is wrong. A perfectly matched implant drifts in a pocket with no walls, and a perfectly built pocket cannot make a narrow implant reach the midline.
How is the cleavage kept stable over the years?
By building the support into the construct at the first operation, so that the medial fullness does not depend on tissue that will relax. The result on the day of surgery is only half the equation. Tissues soften with time, and an implant that is centered only by fresh swelling will settle wherever the pocket allows.
For wide-set breasts that means two things in particular. The medial border is reinforced with layered sutures when the tissue is thin, so the inner wall holds without the pectoralis having been cut past its attachment. The inframammary fold is secured as a stable shelf, because an implant that descends also rotates outward and reopens the gap. The suturing method and the fold reconstruction are described in my article on implant pocket control; here the point is that cleavage is a long-term structure, not an early appearance.
What is the difference between creating cleavage and compressing it?
Created cleavage is present at rest and belongs to the breast; compressed cleavage exists only while something pushes the breasts together. The surgical aim is organic medial fullness, not the temporary cleavage of a push-up bra. The outcome should be a soft, natural curve between the breasts that is there without any support.
That distinction is the whole philosophy. It is the difference between an object placed on the chest and an enhancement that appears to have grown from it. Achieving it requires an eye for holistic balance over simple magnification, and the discipline to work with the anatomy rather than against it.
How much can augmentation narrow a wide gap?
By the width the matched implant adds at the inner edge of each breast, and no more. Wide-set anatomy exists on a spectrum, and honesty about what surgery can achieve is part of good care. Augmentation can meaningfully narrow the visual gap and build a natural, centered fullness, but it works within the boundaries the chest wall sets. A realistic goal is graceful improvement in balance and cleavage, not the elimination of every trace of the natural spacing.
In consultation the plan is built from measurements rather than from a photograph. The assessment covers the breast base width, the intermammary distance, the thickness of the tissue over the sternum, and the shape of the chest wall. From those numbers the implant width and the medial boundary follow, and the achievable cleavage becomes clear before anything is decided.
| Measurement | What it decides | What it rules out |
|---|---|---|
| Breast base width | The implant base diameter | An implant wider than the breast, which strains tissue and risks symmastia |
| Intermammary distance | How much of the gap the matched implant can fill | A promise of touching cleavage on a broad sternum |
| Tissue thickness over the sternum | Whether the medial border needs layered reinforcement | A high profile that would ripple through thin skin at the inner edge |
| Chest-wall shape | Where each implant sits on a curved or flat chest | Treating the two sides as identical when the chest is asymmetric |
How to read this table: each row is a measurement taken before any implant is discussed, and the third column is the reason measurement comes first. The number that most often disappoints is the intermammary distance, because it is the one the implant cannot change.
Where a wide gap is accompanied by deflation after major weight loss, the planning priorities shift again. That is a distinct situation, which I cover in my article on restoring the deflated breast after major weight loss. If your expectations align with what the anatomy allows, you are far more likely to be happy with your result.
What should you ask a surgeon about wide-set correction?
Ask where the medial release will stop, and how the implant width was chosen. Wide-set correction rewards careful surgeon selection more than routine augmentation does, because the margin between a natural result and a destabilized one is narrow. A surgeon who discusses the chest wall in anatomical terms, and explains base-width matching and the sternal boundary rather than promising to push the breasts together, is planning the operation the right way.
It is also reasonable to ask to see long-term results in wide-set breasts rather than early photographs. Cleavage that still looks balanced after several years is the evidence that the boundaries held. If wide-set anatomy is your concern, the most useful next step is an assessment focused specifically on your chest-wall proportions and the cleavage you hope to achieve.
Where can you read about each part of breast augmentation planning in more depth?
Each page below owns one part of the topic, so you can go straight to the question you have.
- Candidacy, incisions, implant placement, recovery, risks, and cost: breast augmentation in Dubai
- How every boundary of the pocket is built, matched, and anchored: implant pocket control in breast augmentation
- Why implants of the same volume shape the breast differently: how base width and projection shape the result
- The two planes beyond the standard three, and the pinch test that rules planes out: the five implant planes and when each is chosen
- The first-operation errors that produce each deformity: technical mistakes in breast augmentation
- Rebuilding a pocket that has failed: breast augmentation revision
- Planning when the breast has deflated after major weight loss: breast augmentation after weight loss
FAQs about wide-set breasts and cleavage in Dubai
-
Can breast augmentation fix wide-set breasts and create cleavage?
It can meaningfully improve them, within anatomical limits. Augmentation narrows the visual gap and builds a natural, centered fullness by matching implant base width to the chest and opening the medial pocket in a measured way. What it cannot do is remove the natural spacing entirely, because the sternal border and the medial pectoral attachments set a fixed boundary. A realistic goal is graceful, balanced cleavage that suits your frame, rather than breasts forced into the midline. The right plan is designed around your chest-wall measurements at consultation.
-
Why can’t cleavage simply be forced closer together?
Because the anatomy that holds the breasts apart is structural, not incidental. The medial pectoral fibers attach firmly along the breastbone, and the sternal border is a fixed limit. Releasing those fibers aggressively to force the breasts together breaches that boundary and destabilizes the whole construct. The result is difficult to reverse: implants merging across the midline, migrating inward, or rippling over the sternum. Durable, natural cleavage comes from optimizing the implant within the safe borders, not from cutting past them.
-
What is symmastia, and how is it avoided?
Symmastia is a complication in which the two implant pockets merge across the midline, so the breasts appear joined with no defined cleavage. The published series attribute it most often to the pectoralis major detaching from the sternum during subpectoral augmentation, with an oversized implant base diameter among the other named causes. It is avoided by keeping the medial release measured, treating the sternal attachment as a fixed landmark, and choosing an implant no wider than the breast. Wide-set cases carry the greatest temptation to over-release, which is why controlled pocket work matters most here. Prevention is far easier than correction.
-
Why does implant base width matter more than size for wide-set breasts?
Because width is what reaches toward the midline, and volume is not. The base diameter must match the natural breast width: too narrow and a gap remains, too wide and the tissues are strained, which can cause a double bubble or lateral bulging. An oversized base is also one of the named causes of symmastia. Volume and profile matter, but they cannot compensate for the wrong base width. Choosing the correct diameter is what allows a seamless inner contour without overstretching the tissues, and it is the foundation the rest of the plan is built on.
-
What implant profile is best for wide-set anatomy?
Often a moderate or moderate-plus profile suits wide-set anatomy better than a high profile. High-profile implants project forward more than they widen, which can emphasize the separation rather than reduce it. A moderate profile spreads the same volume across a broader base, gently filling the cleavage zone and giving medial fullness without an artificial, projecting appearance. The exact choice depends on your measurements and tissue, because a very narrow chest can still need a higher profile to avoid an over-wide base. The principle is to favor a profile that fills rather than one that pushes forward.
-
Will the cleavage look natural, or like a push-up bra?
The aim is the opposite of a push-up bra. A push-up bra compresses the breasts together temporarily; good surgery creates organic medial fullness that is present without any support and looks inherent to the body. The distinction is between an enhancement that appears placed on the chest and one that appears to have grown from it. That natural, soft curve comes from matching the implant to your anatomy and building the pocket to its boundaries, rather than from magnifying volume or compressing tissue. Done well, the cleavage looks and feels like your own.
-
Will the cleavage result last, or will it drift over time?
Durability is built into the surgery, not left to chance. Tissues relax with time, and without internal support an implant can drift outward or descend, which reopens the gap. For wide-set breasts the medial border is reinforced with layered sutures when the tissue is thin, the lateral boundary is held against outward drift, and the inframammary fold is secured as a stable shelf. These measures maintain the implant’s position and preserve the cleavage contour as the years pass. A result engineered this way holds its shape, which is why the internal work matters as much as the visible outcome.
-
How do I know if my expectations for wide-set correction are realistic?
The honest answer comes from measurement. At consultation the breast base width, the intermammary distance, the tissue thickness over the sternum, and the chest-wall shape are assessed, and from those the achievable result becomes clear. Augmentation can narrow the gap and build centered fullness, but it works within the boundaries the chest wall sets. If your expectations match what the anatomy allows, you are far more likely to be satisfied. A responsible consultation tells you plainly what degree of cleavage your anatomy supports, so the plan is built around a natural goal rather than an image that cannot be safely achieved.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
