

Table of content
- What are the key takeaways about breast augmentation revision in Dubai?
- Why does revision begin with diagnosis rather than a new implant?
- How do I correct implant malposition by re-engineering the pocket in Dubai?
- How do I eliminate rippling by engineering soft-tissue coverage?
- How do I restore symmetry with an independent plan for each breast?
- Why is revision a restoration rather than a repair?
- Where can you read about each part of breast augmentation revision in more depth?
- FAQs about breast augmentation revision in Dubai
- How is revision surgery different from my first augmentation?
- My implant has shifted out of position. How do you fix that?
- What is a neo-pocket, and when do you create one?
- What causes rippling, and can it really be corrected?
- What is an internal bra, and when is mesh or dermal matrix needed?
- Can breast asymmetry be corrected during revision?
- Is a revision more complex than the original surgery?
- Why should I choose a revision specialist rather than any surgeon?
- Get appointment
What are the key takeaways about breast augmentation revision in Dubai?
Revision succeeds when the failed structure is diagnosed first and rebuilt, because malposition, rippling, and asymmetry are three different problems with three different repairs, and none of them is fixed by swapping the implant alone.
- Revision begins with diagnosing which structure failed, not swapping the implant.
- Malposition is a pocket failure — corrected by re-engineering the pocket.
- Rippling is a coverage failure — corrected by thickening soft-tissue cover.
- Asymmetry needs an independent plan for each breast.
- The tissues have memory, so lasting correction rebuilds structure.
- The goal is a natural result that looks and feels durably yours.
Breast augmentation revision is surgery on a breast that has already been augmented, to correct a shape or position failure by rebuilding the pocket, the soft-tissue cover, or both, rather than only exchanging the implant. Primary augmentation works with untouched anatomy; revision navigates a landscape of stretched capsules, thinned tissues, and displaced landmarks, where precision supersedes all else. This diagnostic, reconstructive mindset defines my work as a board-certified plastic surgeon in Dubai.
This article covers how each of the three revision failures — malposition, rippling, asymmetry — is diagnosed and structurally repaired. For whether an implant needs exchanging at all, the rupture question, and when a lift belongs with an exchange, see my breast implant exchange in Dubai page; for the technical errors in a first operation that produce these failures, and how they are avoided, see my article on the technical mistakes in breast augmentation.
Why does revision begin with diagnosis rather than a new implant?
Because there is no standard template for a revision: each case is a unique puzzle of altered anatomy, and the implant is rarely the whole story. Before any implant is chosen, the real work is identifying which of the three shape-and-position failures has occurred, and what caused it. That diagnosis dictates everything that follows.
| Failure | What you see | Underlying cause | The structural repair |
|---|---|---|---|
| Malposition | An implant too high, too low, too far to the side, or meeting its partner in the middle. | Pocket too large or misshapen. | Pocket re-engineering: capsulorrhaphy, a neo-pocket, or internal support. |
| Rippling | Visible edges or surface wrinkles, usually at the cleavage or the side. | Soft-tissue cover too thin. | Coverage engineering: fat grafting, a cohesive gel implant, a profile change. |
| Asymmetry | Two breasts that no longer match in height, fullness, or fold. | Side-to-side tissue mismatch. | An independent surgical plan for each breast. |
How to read this table: read across from what you see to the structure that failed; the repair in the last column follows from the cause, not from the implant. Which decision in the first operation produced each failure is a separate question, answered in my article on the technical mistakes in breast augmentation.
Treating each of these as the same problem — simply exchanging the implant — is why so many revisions fail. The implant is rarely the whole story; the pocket and the soft-tissue envelope usually are.
How do I correct implant malposition by re-engineering the pocket in Dubai?
By rebuilding the space the implant sits in, because placing a new implant into the same faulty pocket guarantees the problem recurs. Malposition — an implant sitting too high, too low, too far to the side, or too close to the midline — is fundamentally a pocket problem, and the solution is structural, built on precise pocket control. The same boundaries that go wrong here are the ones set at the first operation, which I describe in my article on how the pocket is built right the first time. An implant that has crossed toward the midline is the hardest of these to repair, which is why the medial boundary is planned so conservatively when the breasts sit wide apart, as I explain in my article on creating cleavage for wide-set breasts.
| Tool | What it does | When I use it |
|---|---|---|
| Capsulorrhaphy | Permanent, high-strength sutures reshape and tighten the existing capsule: suturing it to the chest wall to lift a low implant, closing a lateral pocket to correct outward drift, or rebuilding a defined inframammary fold. | My primary tool, whenever the capsule is sound enough to hold sutures and the distortion is moderate. |
| Neo-pocket | An entirely new plane is created, leaving the old, misshapen capsule behind. | Severe or recurrent distortion, where tightening the old capsule would not hold. |
| Internal bra | A soft mesh or dermal matrix reinforces the lower pole and carries the implant’s weight. | Thin tissues or bottoming-out, where your own tissue cannot support the repair alone. |
How to read this table: the tools escalate from top to bottom; most malpositions are corrected with the first, and the other two are added when the capsule or the tissue is not strong enough on its own.
This reflects the wider evidence base. In a retrospective series of 149 patients and 266 breasts treated with popcorn capsulorrhaphy, malposition was the leading indication, at 61.3% of breasts, ahead of repositioning for ptosis, pocket adjustment for a size change, and pocket reduction after explantation. That is one practice’s caseload with one technique, not a comparison against alternatives, but it shows how often revision is a pocket problem rather than an implant problem.
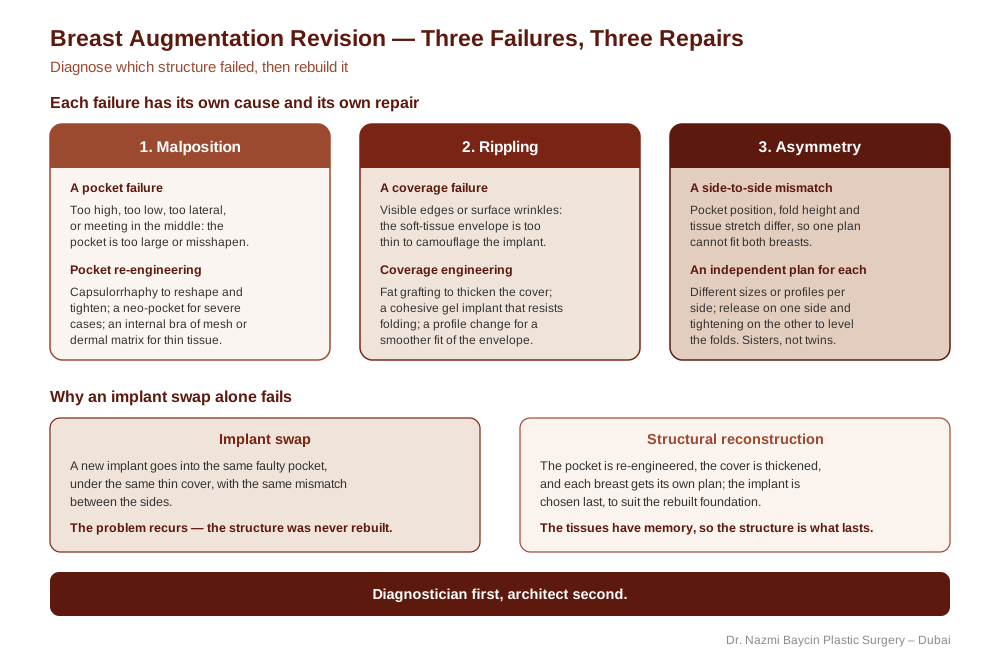
Three failures, three repairs: malposition is a pocket failure rebuilt by capsulorrhaphy, a neo-pocket, or an internal bra; rippling is a coverage failure corrected by fat grafting, a cohesive gel implant, or a profile change; asymmetry is a tissue mismatch answered by an independent plan for each breast — diagnostician first, architect second — by Dr. Nazmi Baycin, Dubai.
How do I eliminate rippling by engineering soft-tissue coverage?
By improving the relationship between the tissue and the implant rather than changing the device in isolation. Rippling — visible edges or surface wrinkles — occurs when the soft-tissue envelope is too thin to camouflage the implant. It is common if you are very slender or if your original pocket was over-dissected. My approach combines three levers:
- Fat grafting — harvesting your own fat and layering it over the implant to thicken the soft-tissue cover and camouflage edges.
- Cohesive gel implant — switching to a firmer, form-stable gel that resists the folding which produces ripples.
- Profile change — sometimes a moderate-profile, wider-based implant fills the envelope more smoothly than a high-profile one.
The cohesive-gel effect has been measured, though in a different setting: in a retrospective cohort of 129 two-stage prepectoral reconstruction patients, the most cohesive implants were associated with less rippling and fewer reoperations for fat grafting. That is post-mastectomy reconstruction rather than aesthetic revision, so I read it as support for the mechanism rather than as a result to hand to you as your own numbers. Together these three levers build a softer, seamless transition where edges once showed. Where the problem is not rippling but a hardened capsule, the options are set out in my article on treating established capsular contracture.
How do I restore symmetry with an independent plan for each breast?
By treating the two breasts as two different problems, which they almost always are after a previous operation. Perfect symmetry is a biological myth, but surgical asymmetry is a correctable reality. Revision allows a meticulous, side-by-side analysis in which differences in pocket position, fold height, and tissue stretch are measured and addressed independently.
I often use a dual-plan strategy — a different surgical plan executed on each side:
- Two different implant sizes or profiles, matched to each breast’s tissue capacity.
- A more aggressive capsulorrhaphy on the side with the lower fold.
- A capsule release on a tight side combined with a capsule tightening on a stretched one.
The aim is balance: breasts that appear as closely matched sisters, not identical twins. Where asymmetry is the primary, longstanding condition rather than the consequence of a previous augmentation, the diagnosis and the plan both start from the native anatomy instead of from a prior operation — a distinct subject I set out in my article on accurate diagnosis and correction of breast asymmetry.
Why is revision a restoration rather than a repair?
Because the tissues carry the memory of the first operation, and a lasting result has to rebuild the structure they rest on, not patch the surface. I view each case not as a simple fix, but as an opportunity to restore what was intended: balance, softness, and confidence. The technical steps — the capsulorrhaphy, the plane change, the fat grafting, the meticulous suturing — are all in service of that higher goal, and it requires patience, spatial reasoning, and an artist’s eye for proportion.
If you want to understand the foundational anatomy we are working to restore, my page on breast augmentation in Dubai sets out the primary principles, and my article on breast augmentation after weight loss explores how changing tissue affects implant support over time. The result of a well-diagnosed revision should be more than improved — it should be a seamless, natural, and finally harmonious version of you.
Where can you read about each part of breast augmentation revision in more depth?
Each page below owns one part of the topic, so you can go straight to the question you have.
- Whether an implant needs exchanging, rupture, and when a lift belongs with it: breast implant exchange in Dubai
- The first-operation errors that produce each deformity: technical mistakes in breast augmentation and how to avoid them
- How every boundary of the pocket is built and anchored at the first operation: implant pocket control in breast augmentation
- Why the medial boundary is planned conservatively when the breasts sit wide apart: managing wide-set breasts for natural cleavage
- Primary augmentation and its principles: breast augmentation in Dubai
- Asymmetry that predates any surgery: breast asymmetry explained
- A hardened capsule rather than a shape failure: capsular contracture management
- How changing tissue affects implant support: breast augmentation after weight loss
FAQs about breast augmentation revision in Dubai
-
How is revision surgery different from my first augmentation?
A primary augmentation works with untouched anatomy, whereas revision navigates a landscape already altered by prior surgery — stretched capsules, thinned tissues, scar tissue, and displaced landmarks such as the inframammary fold. This means there is no standard template; each case is a unique puzzle. The most important difference in my approach is that revision begins with diagnosis rather than with choosing an implant. I first identify which shape-and-position failure has occurred — malposition, rippling, or asymmetry — and what caused it, because each has a different structural solution. Only once that diagnosis is clear do I plan the reconstruction. I describe my role as diagnostician first and architect second, which is why revision demands more planning and spatial reasoning than a primary procedure.
-
My implant has shifted out of position. How do you fix that?
Malposition — an implant sitting too high, too low, too far to the side, or too close to the midline — is fundamentally a pocket problem rather than an implant one. The existing pocket has become too large or misshapen, so simply placing a new implant into that same space would allow the problem to recur. My main tool is capsulorrhaphy: using permanent, high-strength sutures to reshape and tighten the capsule, for example suturing it to the chest wall to lift a low implant or closing off a lateral pocket to correct outward drift. For severe or recurrent distortion I may create an entirely new plane, and for thin tissue I reinforce the lower pole with a mesh or dermal matrix that acts as an internal bra. The aim is to restore the implant’s stable footprint on the chest wall.
-
What is a neo-pocket, and when do you create one?
A neo-pocket is a brand-new plane for the implant, created beside or in front of the old capsule rather than inside it, so the implant sits in fresh tissue that has never been stretched. I create one when the old capsule is too thin, too distorted, or too scarred to hold capsulorrhaphy sutures reliably, or when a previous capsulorrhaphy has already failed and tightening the same capsule again would only repeat that failure. The old capsule is left in place as a layer of support, or partly removed, depending on its quality. A neo-pocket asks more of the planning, because its boundaries are built from scratch, but for a severe or recurrent malposition it is the more durable answer.
-
What causes rippling, and can it really be corrected?
Rippling — visible edges or surface wrinkles — happens when the soft-tissue envelope is too thin to camouflage the implant, which is common if you are slender or if your original pocket was over-dissected. The correction is about improving the relationship between the tissue and the implant, not just changing the device. My approach combines several levers: fat grafting, where your own fat is layered over the implant to thicken the soft-tissue cover; switching to a more cohesive gel implant that resists the folding which creates ripples; and sometimes adjusting the implant profile so it fills the skin envelope more smoothly. Used together, these build a softer, more seamless transition where edges once showed. I find fat grafting in particular to be a transformative adjunct in thin-tissue revision cases.
-
What is an internal bra, and when is mesh or dermal matrix needed?
An internal bra is a sheet of soft surgical mesh or dermal matrix placed along the lower pole of the breast to carry the implant’s weight, so the repair does not depend on thin tissue or a weak capsule alone. I use it when the lower-pole tissue is thin, when the implant has bottomed out, or when a capsulorrhaphy on its own would be under too much load to hold over the years. The sheet is sutured to the chest wall at the planned fold and to the tissue above, forming a hammock that the implant rests on. It adds a step and a cost, so I reserve it for cases where the tissue genuinely cannot support the correction, rather than using it routinely.
-
Can breast asymmetry be corrected during revision?
While perfect symmetry is a biological myth, surgical asymmetry is a correctable reality. Revision gives me the opportunity for a meticulous, side-by-side analysis, measuring differences in pocket position, fold height, and tissue stretch and addressing them independently. My central principle is that the two breasts are rarely the same problem, so they should not receive the same plan. I often use a dual-plan strategy: a different surgical plan on each side, which might mean two different implant sizes or profiles matched to each breast’s tissue capacity, or a capsule release on a tight side combined with a tightening on a stretched one. The goal is balance — breasts that look like closely matched sisters rather than identical twins. Longstanding asymmetry unrelated to a prior augmentation I treat as its own distinct subject.
-
Is a revision more complex than the original surgery?
Revision is generally more complex, because it works within anatomy that has already been changed by prior surgery and by the body’s own adaptation. The tissues have a memory: scar capsules have formed, skin may be stretched, and landmarks may be displaced, so the surgeon must respect and work around that altered foundation. This is why I treat diagnosis as the decisive first step and why I reject a one-size-fits-all approach. The planning demands spatial reasoning and an artist’s eye for proportion, and the execution requires proficiency in advanced pocket and soft-tissue techniques. I view this complexity not as a deterrent but as the reason revision should be undertaken by a surgeon who specializes in it, so that a disappointing previous outcome can be genuinely rebuilt rather than merely patched.
-
Why should I choose a revision specialist rather than any surgeon?
Revision is a distinct discipline that rewards specialization, because it combines complex diagnosis with advanced reconstructive technique. The work demands both the analytical skill to identify precisely which structure failed and the technical proficiency in pocket control, soft-tissue engineering, and independent side-by-side planning to rebuild it. A surgeon who mainly performs primary augmentations may be tempted to treat every revision as an implant exchange, which is the common reason revisions fail. My own commitment to this complex niche — acting as diagnostician and architect, and respecting the memory of altered tissue — is what I offer you if you have already endured one disappointing outcome. For you, revision is not a simple fix but a strategic reconstruction aimed at a result that finally surpasses their original expectations.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
