


Table of content
- What are the key takeaways about the clitoral hood in labiaplasty?
- Why is the clitoral hood part of every labiaplasty decision?
- What has the surgical literature said about the hood after labiaplasty?
- What happens when the hood is ignored in a labiaplasty?
- What happens when the hood is over-reduced?
- Why is the midline of the hood never crossed?
- When do I decide to leave the hood alone in Dubai?
- Which four questions do I settle before anything is cut?
- What can the evidence on these operations tell you?
- Where can you read about each part of the clitoral hood and labiaplasty in Dubai in more depth?
- FAQs about the clitoral hood and labiaplasty in Dubai
- Get appointment
This article covers a single judgment, what to do about the clitoral hood when the labia minora are reduced, and what follows from getting it wrong; how the hood reduction itself is performed around the nerve is covered in the nerve-sparing technique for clitoral hood reduction, and the labiaplasty itself, with its techniques, anesthesia, recovery and candidacy, on labiaplasty in Dubai.
What are the key takeaways about the clitoral hood in labiaplasty?
Reducing the labia minora changes how the hood looks whether or not it is touched, so the hood has to be examined and decided about before any labiaplasty, even when the decision is to do nothing.
- Reducing the labia minora can make an unreduced hood appear larger than before.
- This is a named deformity in the surgical literature, not an unlucky outcome.
- Hood redundancy is described as the commonest reason women seek revision.
- Over-reduction is worse: the hood exists to shield, and cannot be replaced.
- The correct answer is sometimes to do nothing, but only after examining.
- Published evidence is largely retrospective, and you deserve to be told so.
Why is the clitoral hood part of every labiaplasty decision?
The clitoral hood is part of every labiaplasty decision because it is not a neighbor of the labia minora but a continuation of them: the hood is the anterior extension of the same tissue, arising from the same embryological fold, reaching the clitoris as the labia minora divide to meet it. Surgeons speak of them as separate procedures because they are billed as separate procedures. Anatomy does not recognize the distinction.
When I reduce the labia minora, I have altered one end of a continuous structure and left the other end as it was. Whether that constitutes a decision depends entirely on whether I examined it first. So the question is not should the hood be reduced. The question is what the hood will look like once its neighbors are smaller, and whether that is what you came for.
What has the surgical literature said about the hood after labiaplasty?
The surgical literature has described the problem by name: a hood that looks larger after labiaplasty is a recognized postoperative deformity, and hood redundancy has been called the commonest reason women seek corrective surgery after labia minora reduction. This is not my observation alone. In a case report in the Aesthetic Surgery Journal titled Postoperative Clitoral Hood Deformity After Labiaplasty, the author observes that in select patients with redundant clitoral hood tissue, edge trim techniques may produce an imbalanced result in which the hood actually looks larger. Those patients, she writes, complain of a prominence of the clitoral hood that was not present before their labiaplasty. The operation did not reveal a problem; it created one. It is a report of two patients, so it documents that the deformity occurs, not how often.
The commentary published alongside that report is blunter still. Its author states that clitoral hood skin redundancy is, in his revision experience, the most common reason women seek corrective surgery after labia minora reduction, and he sets out the obligation plainly: where hood redundancy is present, it must be identified during the preoperative consultation and addressed as part of the labia minora reduction. That is one experienced surgeon’s opinion rather than a measured rate, but it is the opinion of someone who sees the revisions.
What happens when the hood is ignored in a labiaplasty?
When the hood is ignored, it stays the same size while everything around it is lowered, and six weeks later it is the most prominent structure there. A woman arrives with labia minora that protrude and a hood she has never thought about. The labia are reduced beautifully and nothing is done to the hood. It has not grown; it has been left standing while its neighbors were reduced, and the eye reads prominence relatively, not absolutely.
She was not warned, because her surgeon did not think of the hood as part of the operation, and she now needs a second procedure to correct a problem produced by the first. A revision on this tissue is a poorer operation than a well-planned primary would have been, performed through scar, on a woman who has lost some of her confidence in surgery. What such a revision involves is set out in my article on correcting scarring and asymmetry after labiaplasty.
What happens when the hood is over-reduced?
When the hood is over-reduced, the glans is left uncovered, and the result is relentless hypersensitivity rather than heightened pleasure, which is very close to impossible to reverse. This is the opposite error, the worse one, and the one I spend most of my time preventing. Understanding that balance matters, a surgeon reduces the hood, then a little further, because the proportions still look uneven under theater lights, on a supine patient, with tissue distorted by local anesthetic. The hood is not decoration. It is a shield, and the structure beneath it is not built to meet the world directly.
A woman whose glans is chronically exposed experiences her underwear, a seam in her jeans, a long walk, a bicycle, a day at work. Tissue cannot be given back. I would sooner accept a slightly fuller hood than take a millimeter too much; that is not timidity but an accurate assessment of which of the two errors can be corrected later.
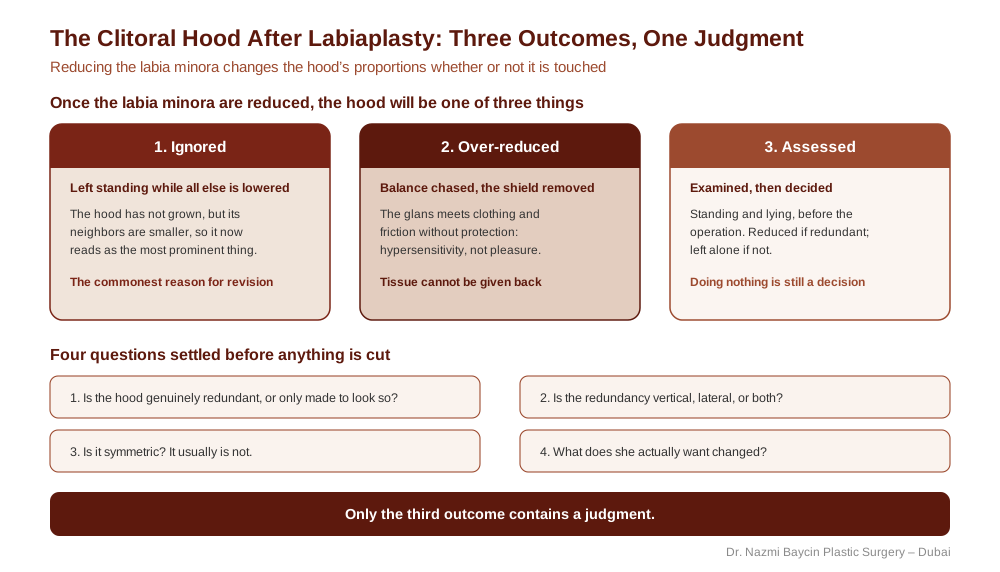
The three outcomes available once the labia minora are reduced, and the four questions that separate a decision from an omission, by Dr. Nazmi Baycin, Dubai.
| The decision | What patients assume | What actually happens | What I do |
|---|---|---|---|
| Hood untouched | It stays as it was | It becomes proportionally larger | Assess it before operating |
| Hood reduced | A separate procedure | The same continuous tissue | Plan both together |
| Reducing further | Better balance | Exposure of the glans | Stop early, deliberately |
| Over-reduction | Correctable later | Tissue cannot be returned | Err toward coverage |
| The midline | Where excess sits | Where the nerves run | Never excise across it |
| Doing nothing | Not a decision | The right answer, sometimes | Say so, and record why |
How to read this table: the second and third columns show the gap between assumption and anatomy, and the last column is what closes it; the first and last rows are the two faces of the same rule, that leaving the hood alone is right only after it has been examined.
Why is the midline of the hood never crossed?
The midline of the hood is never crossed because the nerves that carry sensation run in a predictable relationship to it, so tissue is taken to either side and never across. That one rule constrains everything a surgeon can honestly promise: it is why a hood reduction has limits, and why those limits are a feature rather than a failing. A surgeon willing to cross the midline can achieve any degree of reduction he likes, gambling with sensation the woman cannot get back. I would rather be constrained than clever. Where the nerves actually run, why the resection is lateral and how it is closed is set out in my article on the nerve-sparing technique for clitoral hood reduction.
When do I decide to leave the hood alone in Dubai?
I decide to leave the hood alone when examination shows it is not redundant, which is frequently the case: a great many women have labia minora that trouble them and a hood that is entirely unremarkable. Everything above argues that the hood must be considered; none of it argues that it must be reduced. Reducing an unremarkable hood because the labia were reduced is not balance. It is symmetry pursued for its own sake, on tissue that had no complaint against it, at a cost measured in sensation and coverage.
So I examine, and I often conclude that nothing should be done. I say so out loud, I explain why, and I record the reasoning. The distinction between an omission and a decision is invisible in the operative note and enormous in the outcome.
Which four questions do I settle before anything is cut?
I settle four questions at the consultation, none of them with the patient lying down and anesthetized: whether the hood is genuinely redundant, whether the redundancy is vertical or lateral, whether it is symmetric, and what you actually want changed.
- Is the hood genuinely redundant? Or does it merely appear so because of what currently sits beside it? The examination is performed standing as well as lying down, because gravity is part of the anatomy and the operating table conceals it.
- Is the redundancy vertical, lateral, or both? A hood with vertical excess presents as elongated and drooping; a hood with lateral folds presents quite differently, and the two are corrected differently. Treating one as the other produces a tidy operation and an unsatisfied woman.
- Is it symmetric? It usually is not, and a plan that assumes symmetry will deliver asymmetry with great precision.
- What do you actually want changed? Chafing during exercise is a different complaint from discomfort during intercourse, and both differ from an appearance she dislikes. These do not always need the same operation, and one of them sometimes needs none.
The table below sets out how I examine each question and what its answer changes in the plan.
| Question | How I examine it | What the answer changes |
|---|---|---|
| Is the hood genuinely redundant? | Standing and lying down, and with the labia held at their planned size so the hood is judged against its future neighbors | Whether the hood is reduced at all; a hood that only looks full beside large labia is left alone |
| Is the redundancy vertical, lateral, or both? | Vertical excess shows as a hood that hangs below the glans; lateral excess shows as folds to either side | Where the tissue is taken from and in which direction the incisions run |
| Is it symmetric? | Each side is measured and photographed separately, standing | A side-specific plan, so the result rather than the resection is symmetrical |
| What do you actually want changed? | I ask you to show me on your own body, and to name the situation in which it troubles you | Whether the hood needs any operation, and which one |
How to read this table: the first question decides whether, the second and third decide how, and the last can overrule all three. None of them can be answered on an anesthetized patient lying down.
I ask you to show me, on your own body, what troubles you. The answer is very often not the structure I had assumed, and every minute spent on that question is worth an hour of technique. How that same examination traces the source of labial discomfort before any labiaplasty is set out in my article on how labial discomfort is diagnosed before surgery.
What can the evidence on these operations tell you?
The evidence can tell you that satisfaction after these operations is high, and it cannot tell you much more than that, because the literature is retrospective. A review of female genital cosmetic and plastic surgery found overall patient satisfaction in the ninety to ninety-five percent range, with satisfaction relating to sexual function somewhat lower, and concluded in the same breath that the studies behind those figures are retrospective.
That caveat is not a technicality. Retrospective studies of satisfied patients tell you about satisfied patients. Professional bodies have for years advised that women considering these procedures be informed that data on their efficacy are limited, and I regard passing that on as part of consent rather than as an inconvenience. So what I can honestly tell you is this: the deformity I have described is real, documented and avoidable by examination; the operation is well tolerated; the satisfaction figures are encouraging and they are not proof; and I will not promise you a sensation, because sensation is the one thing in this operation that nobody can promise and only a surgeon can take away. That is the standard of my plastic surgery practice in Dubai.
Where can you read about each part of the clitoral hood and labiaplasty in Dubai in more depth?
This article covers the decision about the hood; the pages below cover the technique, the labiaplasty it belongs to, and the neighboring procedures.
- How the hood is reduced around the nerve: nerve-sparing clitoral hood reduction
- The labiaplasty, candidacy, recovery and risks: the labiaplasty procedure page
- Diagnosing discomfort: how labial discomfort is diagnosed before surgery
- Uneven sides: correcting asymmetric labia
- Sexual function: what labiaplasty means for sexual function
- Preventing unwanted results by design: how preoperative design prevents unwanted labiaplasty results
- Correcting a previous result: corrective revision labiaplasty and correcting scarring and asymmetry after labiaplasty
- The outer lips and the wider range of procedures: vulvoplasty in Dubai and cosmetic genital surgery in Dubai
FAQs about the clitoral hood and labiaplasty in Dubai
-
Do I need clitoral hood reduction with my labiaplasty?
Possibly not, and I will tell you if not, but the question cannot be avoided. The clitoral hood is the continuation of the labia minora, not a separate structure, so when the labia are reduced the hood stays the same size while everything around it becomes smaller, and the eye reads prominence relatively. The decision is not whether to add a procedure; it is what your hood will look like once its neighbors are reduced, and whether that is what you came for.
-
What should I ask my surgeon about the clitoral hood?
Ask what he intends to do about it, and do not accept nothing as an answer on its own. If the hood is to be left alone, ask what he examined before deciding that, whether he looked at you standing as well as lying down, and whether he considers your hood genuinely redundant or only likely to look that way beside labia that are about to be reduced. Then ask what he expects it to look like afterward in proportion to the labia. The useful question is whether he holds a reasoned position on your hood, because he is going to change how it looks either way.
-
Is clitoral unhooding the same as clitoral hood reduction?
No, and I am cautious about the word. Unhooding implies uncovering, and nothing in the aesthetic case for this operation requires the glans to be uncovered, while the functional case against it is considerable. Coverage is the purpose of the structure, and a hood that no longer shields has not been improved, whatever it looks like. If a surgeon offers to unhood you as a route to greater sensitivity, ask what happens if the sensitivity he produces is not the kind you wanted.
-
Can the hood be reduced later if it looks larger after labiaplasty?
It can, as a revision, but a revision is a poorer operation than a well-planned primary would have been: it is performed through scar, on tissue that has already healed once, and it asks a woman to go through a second procedure for a problem the first one produced. That is why the hood is assessed at the consultation before the labiaplasty, so that the decision is made once, with everything still in its original state.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
