

Table of content
- What are the key takeaways about the dual-technique approach to gynecomastia surgery in Dubai?
- Why does gynecomastia need two surgical techniques instead of one?
- What does the evidence show about combining gland excision with liposuction?
- How does the chest’s composition decide which techniques I use in Dubai?
- How is the glandular disc excised through the areola?
- How does feathering liposuction shape the masculine chest?
- How do the tissues of gynecomastia map to the surgical tools?
- When does the dual technique need a skin or areola procedure added?
- What technical mistakes do I avoid in dual-technique gynecomastia surgery?
- How does recovery protect the contour the dual technique creates?
- Where can you read about each part of gynecomastia surgery in Dubai in more depth?
- What do patients in Dubai ask most about the dual-technique approach to gynecomastia surgery?
- Why does precision matter more than the amount of tissue removed?
- Get appointment
The dual-technique approach to gynecomastia surgery is the combination of direct excision of the firm glandular disc behind the nipple with feathering liposuction of the surrounding fat, performed in one operation so that each tissue is removed by the tool suited to it.
Gynecomastia correction is often reduced to the phrase “male breast reduction,” but that label misses what actually determines the result. Removing tissue is easy; shaping a chest that looks masculine is not. The difference between a flat, hollow, obviously operated chest and a natural, athletic one lies in how the two tissue types, the resistant fibrous gland and the surrounding fat, are handled, and in how much tissue is deliberately left behind.
This article covers how the combined operation is performed and why each step is done the way it is. For candidacy, cost, risks and the full recovery timeline, see my page on gynecomastia surgery in Dubai; for how the tissue mix is diagnosed, see the three types of gynecomastia and when an ultrasound scan decides the plan.
What are the key takeaways about the dual-technique approach to gynecomastia surgery in Dubai?
The dual technique matches each tissue to the tool that removes it best, and its quality is decided as much by what is left behind as by what is taken out.
- Gynecomastia usually involves two different tissues, a fibrous gland and fat, and each needs a different tool.
- Excision removes the gland; liposuction contours the fat. Pooled reviews link the combination to the most consistent results and the lowest reported complication rate, though the evidence comes from uncontrolled series.
- Treating a hard glandular disc with liposuction alone tends to leave a puffy nipple and can create a contour deformity that is harder to correct later.
- A thin, even cushion of about 5 mm is deliberately left under the nipple to prevent a crater deformity.
- Feathering liposuction tapers the fat at the edges so the lower and outer borders of the pectoral muscle show without a visible step.
- The two errors I see most in revision patients are gland left behind after liposuction alone and over-resection under the nipple that creates a crater.
Why does gynecomastia need two surgical techniques instead of one?
Gynecomastia needs two techniques because it is usually made of two tissues that behave differently: fat, which liposuction removes well, and a glandular disc, which suction removes reliably only when the gland is soft. When the disc is hard, using one tool for both leaves one of the two problems untreated.
The two most common errors I see in patients who come to me for revision are opposite failures of the same principle: gland left behind after liposuction alone, and gland over-resected under the nipple, which creates a crater deformity. The first treats a two-tissue problem with one tool; the second removes the right tissue in the wrong amount. Liposuction is excellent at removing fat and shaping its edges. Direct excision is the reliable way to remove the gland. Neither does the other’s job well, so I plan the operation around both from the start. What the three tissues are, and how each gives itself away on examination, I describe in my article on what gynecomastia is made of.
Why does a hard glandular disc resist liposuction?
A hard glandular disc resists liposuction because it is dense, fibrous tissue firmly attached behind the nipple, and a cannula tends to slide over it rather than remove it. A soft gland is different: VASER’s ultrasound energy can liquefy soft glandular tissue so that it can be suctioned out.
Long-standing gynecomastia becomes more fibrous over time, so the disc grows firmer and less responsive to suction, and that hard disc is what creates the stubborn puffy nipple that diet and exercise never change. At examination I distinguish a soft gland, which VASER can liquefy and remove through liposuction, from a hard disc, which I excise directly. An uneven remnant directly under the nipple is exactly what shows most, so when the gland is too dense to liquefy evenly, I do not rely on suction to remove it.
What does the evidence show about combining gland excision with liposuction?
The published evidence consistently favors combining excision with liposuction, but it comes from uncontrolled case series and pooled reviews rather than randomized trials. It shows a consistent pattern, not a precisely measured advantage.
A review of 18 men who needed secondary surgery after gynecomastia correction performed elsewhere found that every specimen removed at the second operation still contained a sizable amount of gland. Ten had been treated with liposuction alone and eight had also had partial glandular resection, so gland was left behind either way, and removing it at revision produced a dished-out appearance. The author concluded that liposuction alone unmasks the underlying gland and that, where fat contributes to the deformity, liposuction should be combined with glandular excision in the primary operation. It is a single-surgeon series without a control group, so it illustrates the failure pattern rather than measuring how often it happens.
A systematic review of seventeen studies concluded that excision of the glandular tissue combined with liposuction gives the most consistent results with a low complication rate, while grading the evidence very low quality because every included study was non-randomized. A larger 2022 systematic review of 94 articles and 7,294 patients found the lowest reported complication rate in the combined group. Its authors are careful to note that excision alone tended to be used for the most severe cases, which inflates its complication rate, and that the lack of a single classification system biases any comparison.
| Source | Design | What it found | What it does not show |
|---|---|---|---|
| Aiache, 1998 | Single-surgeon retrospective review of 18 men needing secondary surgery | Every specimen removed at revision still contained a sizable amount of gland after primary liposuction, with or without partial excision; removing it secondarily produced a dished-out appearance | How often the failure occurs: no control group and no denominator of all patients treated |
| Fagerlund and colleagues, 2015 | Systematic review of 17 studies (14 on treatment) | Excision combined with liposuction gave the most consistent results with a low complication rate | Any randomized comparison: every included study was non-randomized, at high risk of bias, and rated very low quality |
| Innocenti, Melita and Dreassi, 2022 | Systematic review of 94 articles and 7,294 patients | Reported complications: 11.8% with combined techniques, 14.9% with liposuction-type techniques alone, 30.6% with excision alone | A fair head-to-head comparison: groups were not matched for severity, and excision alone was often used for the most severe cases |
How to read this table: The third column is what each source supports, and the fourth is where its support stops. Taken together, the three point the same way, which is why I combine the techniques, but none of them is a randomized trial, so I describe the advantage as consistent rather than proven.

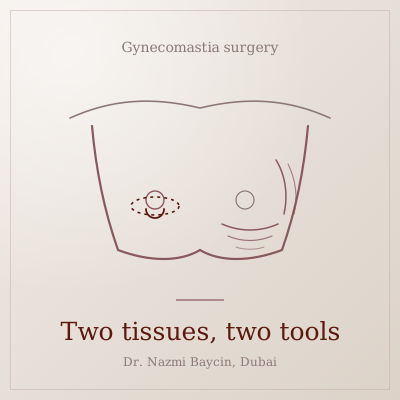
The dual-technique approach: periareolar glandular excision followed by feathering liposuction contouring — by Dr. Nazmi Baycin, Dubai.
How does the chest’s composition decide which techniques I use in Dubai?
The balance of gland, fat and skin decides how much of each technique I use. A chest that is mostly fat may need liposuction alone, while a chest with a firm disc always needs excision.
I set out how I classify the three types of gynecomastia in my article on diagnosing and treating the three types of gynecomastia; here the question is how that diagnosis changes the operation. Where a muscular chest wall or a thick fat layer makes it hard to feel whether the disc is soft or hard, I confirm the reading with an ultrasound scan before deciding, as I explain in my article on why an ultrasound scan decides the plan before surgery.
| What the chest is mostly made of | What I find on examination | How I plan the dual technique |
|---|---|---|
| Mostly fat (pseudogynecomastia) | Soft, evenly compressible tissue with no firm disc behind the nipple | Liposuction may be enough on its own; I still check for a small disc and remove it if present |
| Fat with a soft gland | Glandular tissue behind the nipple that is soft rather than firm | VASER liposuction can liquefy the soft gland along with the fat; I excise only what remains firm |
| Mixed fat and hard gland | A firm disc behind the nipple within a layer of fat | Full dual technique: excision of the disc and feathering liposuction of the surrounding chest |
| Mostly hard gland, lean chest | A distinct firm disc with little surrounding fat, common in lean or athletic men | Excision is the main step; liposuction is limited to feathering the edges so no step is left |
| Gland and fat with loose skin | Ptosis of the nipple or skin that will not retract | Dual technique plus a skin or areola procedure in the same operation |
How to read this table: Find the row that matches the chest, then read across to the plan. The middle column is what I feel for at consultation: whether there is gland behind the nipple, and whether it is soft or hard. A hard disc moves a patient to the third or fourth row, whatever his weight.
How is the glandular disc excised through the areola?
I remove the glandular disc through a semi-circular incision along the lower edge of the areola, where the scar sits in the natural color change between areola and chest skin. Through it, the disc is dissected out from behind the nipple with tapered edges.
Using electrocautery and sharp dissection, I free the disc from the overlying skin and from the pectoral fascia beneath it, then taper its edges rather than leaving an abrupt shelf. An abrupt edge is what later shows as a saucer-shaped depression.
How much tissue do I leave under the nipple, and why?
I leave a thin, even layer of about 5 mm of tissue under the nipple-areola complex. That cushion keeps the nipple’s normal projection and prevents the crater deformity that follows over-resection.
Thorough gland removal and deliberate preservation under the nipple are not contradictory goals; achieving both at once is the skill. Over-aggressive excision directly under the nipple is a recognized cause of a hollow that is far harder to repair than to avoid, and I describe the repair in my article on correcting a crater deformity after previous gynecomastia surgery. The aesthetic reasoning behind this restraint is the first of the principles I set out in the three pillars of a natural male chest.
How does feathering liposuction shape the masculine chest?
Feathering liposuction shapes the chest by removing fat progressively less toward the edges, so there is no visible line where treatment stopped and the lower and outer borders of the pectoral muscle show through. Excision flattens the center; feathering creates the contour.
After the gland is out, I treat the periphery of the excision site, the outer chest toward the armpit (the axillary tail) and the lower pectoral border. With the gland already removed, I can see and feel exactly how much fat surrounds the defect and blend the edges into it. The aim is a subtle taper from chest to abdomen that reads as trained rather than operated. Excision alone can leave a chest that is flat but shapeless; feathering is what makes the result look masculine.
Why do I use power-assisted or VASER liposuction for feathering?
I use power-assisted liposuction (PAL) or VASER because both give fine, controlled removal in the fibrous fat of the male chest, which makes even tapering at the edges easier. I choose VASER when the gland is soft, because its ultrasound energy can liquefy soft glandular tissue as well as fat.
Male chest fat is often denser than fat elsewhere on the body, and a device that helps the cannula pass through it lets me work in small, even passes rather than forcing it. How the devices themselves work is covered on my page on liposuction in Dubai; on the chest, what matters is the control they give at the margins.
How do the tissues of gynecomastia map to the surgical tools?
Each tissue maps to one tool: the gland to excision, the fat to feathering liposuction, the tissue under the nipple to preservation, and excess skin to a tightening technique. The result depends on applying each one only where it belongs.
| Tissue or goal | The problem it causes | The tool that addresses it | What happens if it is handled wrongly |
|---|---|---|---|
| Glandular tissue behind the nipple | Puffy nipple that does not respond to diet or exercise | VASER liposuction if the gland is soft; direct periareolar excision if it is hard | Left behind: persistent puffiness and a later revision |
| Surrounding fat | Bulk of the chest and blurred pectoral borders | Feathering PAL or VASER liposuction | Over-suctioned: irregular, adherent skin; under-treated: a heavy, soft chest |
| Tissue directly under the nipple (about 5 mm) | None if preserved | Deliberate preservation | Over-removed: a concave crater deformity |
| Edges of the excision | An abrupt shelf shows as a saucer-shaped dip | Tapered excision and feathering | Left abrupt: a visible step around the areola |
| Outer chest toward the armpit | Lateral fullness that widens the chest | Liposuction of the axillary tail | Ignored: the chest looks flat in front but wide from the side |
| Loose skin or a wide areola | A loose envelope after debulking | Areolar reduction or a skin-tightening technique | Ignored: folds and a low-hanging nipple |
How to read this table: Read each row from left to right as a cause, its correction, and the failure that follows when the correction is missing or overdone. The last column is a list of the deformities that bring patients to revision.
When does the dual technique need a skin or areola procedure added?
The dual technique needs a skin or areola procedure when the skin is too loose to retract over the new contour or the areola is enlarged. In those cases I add areolar reduction or a skin-tightening technique to the same operation.
Young skin with good elasticity usually retracts on its own once the gland and fat are gone. Where it will not, or where the nipple sits low, I reduce the areolar diameter and, when necessary, remove skin with a concentric-circle (around the areola) or circumvertical technique. The incisions are still planned to sit at the areolar border, so the price of a tighter, flatter chest stays as discreet as possible.
What technical mistakes do I avoid in dual-technique gynecomastia surgery?
The mistakes that matter most are leaving the gland, removing too much under the nipple, and leaving visible edges where either technique stopped. Each one has a specific step in the operation designed to prevent it.
| Mistake | What it causes | How I avoid it |
|---|---|---|
| Liposuction alone on a hard glandular disc | A persistent puffy nipple | I assess whether the gland is soft or hard at every consultation; a soft gland can be liquefied with VASER, a hard disc is excised |
| Removing everything under the nipple | A crater deformity and a nipple stuck to the muscle | A thin, even cushion of about 5 mm is left in place |
| An abrupt edge to the excision | A saucer-shaped dip around the areola | The disc’s edges are tapered, then blended with feathering liposuction |
| Debulking without feathering | A visible line where liposuction stopped | Fat removal is reduced progressively toward the margins |
| Over-suctioning thin areas | Irregular, adherent skin | Small, even passes and a final check of the contour by touch |
| Ignoring the axillary tail | A chest that still looks wide from the side | The outer chest toward the armpit is part of the planned treatment area |
How to read this table: The first two rows are the errors I see most often in patients referred for revision; the last column is the step in my operation that exists to prevent each one. Most of them are not complications of chance but consequences of technique.
How does recovery protect the contour the dual technique creates?
Recovery protects the contour mainly through compression, which helps the skin settle evenly over the new shape and limits fluid in the spaces left by the gland and fat. The details of the timeline belong to the full procedure plan.
Because the result depends on the skin redraping smoothly over the excision site and the feathered edges, I ask patients to wear a compression vest continuously in the first weeks. The complete recovery timeline, including when training can resume, is set out on my page on gynecomastia surgery in Dubai and tailored to each patient at consultation.
Where can you read about each part of gynecomastia surgery in Dubai in more depth?
Each part of the subject has its own page: the procedure page covers candidacy, recovery, risks and cost, and the articles below each go deeper into one question.
- The procedure, candidacy, recovery, risks and cost: gynecomastia surgery in Dubai
- The three tissues behind the fullness: what gynecomastia is made of: gland, fat and the puffy nipple
- Classification and the operation each type needs: the three types of gynecomastia and how each is treated
- When a scan decides the plan: why an ultrasound scan decides the plan before surgery
- Sculpting a natural rather than flat chest: the three pillars of a natural male chest
- Repairing a poor first result: revision surgery for crater deformities and chest asymmetry
- The chest within whole-torso contouring: male body sculpting and why the male form needs its own rules
- The liposuction devices themselves: liposuction in Dubai
What do patients in Dubai ask most about the dual-technique approach to gynecomastia surgery?
Patients most often ask why liposuction alone is not enough, what a crater deformity is and where the scar will be; the answers below are specific to the dual technique.
-
Why can’t gynecomastia be fixed with liposuction alone?
Liposuction removes fat, and VASER can liquefy a soft gland, but a hard, dense glandular disc behind the nipple is not reliably suctioned away. If it is left behind, the nipple stays puffy, and removing only the surrounding fat can unmask the gland and leave a contour depression that is harder to correct later. That is why I excise the gland directly and contour the fat with liposuction in the same operation.
-
What is a crater deformity, and how is it avoided?
A crater deformity, also called a saucer deformity, is a hollow under the nipple caused by removing too much tissue directly beneath it. I avoid it by leaving a thin, even cushion of about 5 mm under the nipple-areola complex and by tapering the edges of the excision rather than cutting an abrupt shelf.
-
Where is the incision, and will the scar show?
The incision runs along the lower edge of the areola, where the scar sits in the natural color change between the areola and the chest skin. It usually becomes hard to see once it matures, although every scar is visible on close inspection and scar quality varies between individuals.
-
What does feathering liposuction mean?
Feathering means removing progressively less fat toward the edges of the treated area, so there is no visible line or step between treated and untreated skin. It is what lets the pectoral borders show and gives a natural taper from chest to abdomen, rather than a chest that is simply flattened.
-
Can the gland be removed without an incision on the areola?
Some techniques pull the gland out through a liposuction opening or remove it endoscopically from the armpit. I prefer the incision at the lower edge of the areola because it lets me see the disc directly, leave an even cushion under the nipple and taper the edges, which are the steps that prevent the most common deformities.
Why does precision matter more than the amount of tissue removed?
Precision matters more because the deformities that bring patients to revision come from tissue removed in the wrong place, not from too little tissue removed overall. A natural chest is defined by where tissue is kept as much as by where it is taken.
The periareolar access, the cushion under the nipple and the feathering of the fat are not incidental details; they are the difference between a natural result and an obvious one. If you are considering correction and want to understand how I approach plastic surgery in Dubai, the consultation begins with the same question this operation answers: which tissue is responsible, and what is the right tool for it?


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
