

Table of content
- What are the key takeaways about diagnosing a double chin?
- Which layers make up a double chin?
- Why can liposuction make the wrong double chin look worse?
- Why is platysmal laxity the overlooked cause of the aging neck?
- How do I examine a double chin at consultation in Dubai?
- Which three categories does the examination sort your neck into?
- How can you read your own neck before a consultation?
- Why does respecting the layers decide whether the result lasts?
- Where can you read about each part of double chin treatment in Dubai in more depth?
- FAQs about double chin diagnosis in Dubai
- Is a double chin always caused by fat?
- How do I know if my double chin is fat or muscle?
- Why does liposuction sometimes make a double chin look worse?
- What is platysmal laxity, and why is it so often missed?
- Can my neck be both fat-dominant and muscle-dominant?
- Does the shape of my platysma at birth affect my neck?
- What should a proper double chin consultation include?
- Get appointment
This article covers the diagnosis: the layers, how I examine them, and the three categories a neck sorts into. The full set of methods, candidacy, recovery, risks and cost are on double chin removal in Dubai; what happens when fat is removed over a lax muscle, and the components of an integrated correction, are in double chin recurrence after liposuction; how liposuction itself is performed safely along the jawline is in lower face liposuction; and the neck whose problem is the bone is in the genetic double chin in slim patients.
What are the key takeaways about diagnosing a double chin?
The examination, not the mirror, decides whether your double chin is fat, muscle or both, and that decision is what makes the treatment work.
- A “double chin” is a layered anatomical problem, not a single fat issue.
- The most common cause of failure is misdiagnosis: treating fat when the muscle is the real culprit.
- Platysmal laxity drives the majority of submental concerns in patients over 35.
- Liposuction on a muscle-dominant neck can unmask bands and worsen the result.
- Necks sort into fat-dominant, muscle-dominant or combined; each needs a different approach.
- A dynamic assessment, not a static glance, is what reveals which category you fall into.
The aim throughout is to move from guessing to knowing. Once the dominant structural failing is clear, the right treatment becomes obvious, and durable.
Which layers make up a double chin?
From the surface inward: the skin, the superficial fat, the platysma muscle, the deep fat, and the bony foundation of the hyoid and the jaw. Each layer ages differently, and each contributes to fullness under the chin in its own way.
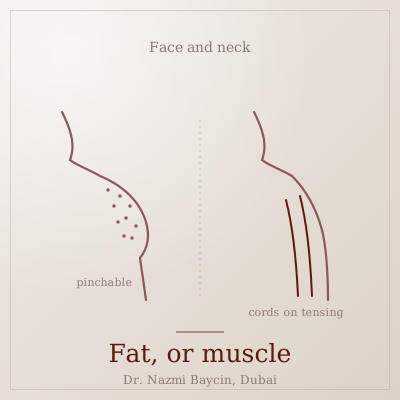
- Fat accumulation: an increase in superficial or deep fat creates soft, pinchable volume.
- Platysmal deterioration: the muscle’s midline fibers separate into visible bands and its lower border descends, losing its sling-like support. This is the hidden architect of many failed treatments.
- Skin laxity: loss of collagen and elastin leaves redundant, crepe-like skin that cannot redrape.
- Skeletal support: a recessed chin or a low hyoid sets an unfavorable foundation. Where the skeleton is the leading cause rather than a contributing one, most often in slim, fit patients whose neck never matched their weight, the plan is built around the bone instead, which I set out in my article on the genetic double chin in slim patients.
| Layer, from the surface inward | What goes wrong | What you notice | What it needs |
|---|---|---|---|
| Skin | Loses collagen and elastin; cannot shrink onto a new contour | Crepey, loose skin that hangs rather than drapes | Tightening or, where severe, a trim |
| Superficial fat | Accumulates with weight or genetics | Soft, pinchable fullness that moves with your weight | Conservative liposuction |
| Platysma muscle | Midline fibers separate; the lower border descends | Vertical cords when you tense the neck; a blunt neck angle at a healthy weight | Platysmaplasty |
| Deep fat | Fullness beneath the muscle | Fullness that does not pinch away at the surface | Direct reduction beneath the muscle, where indicated |
| Hyoid and jaw | A low hyoid or a recessed chin | A short, heavy profile even in a slim neck | Chin projection; the skeletal pathway |
How to read this table: read down the third column and find the description that matches your neck; the last column is the treatment that layer calls for. Most necks involve two rows, and the examination below is how I find which.

How fullness under the chin is diagnosed by layer, fat, muscle or both, and why that diagnosis dictates the correct treatment, by Dr. Nazmi Baycin, Dubai.
Treating only the most visible layer, fat, while ignoring a weakened muscular foundation is a fundamental error. It corrects a fraction of the problem while making the rest more apparent.
The starting anatomy differs from person to person, and that baseline matters. An anatomical study of 20 cadavers in the International Journal of Oral and Maxillofacial Surgery found four distinct patterns of midline merging. In 15 percent the platysma formed a complete sheet under the chin; in the other 85 percent there was some degree of midline gap, measuring 6 to 24 mm a centimeter behind its apex and 10 to 44 mm a centimeter further back. Its authors suggest that the wider and more U-shaped that gap, the greater the tendency toward a turkey-gobbler deformity. That is a hypothesis drawn from cadaveric anatomy rather than a measured clinical outcome. It shows inherited variation, not age-related separation; the loss of tone that produces bands later in life is a separate process, acting on whatever baseline you started with.
Why can liposuction make the wrong double chin look worse?
Because on a neck whose real problem is platysmal laxity, the fat was camouflaging the muscle, and removing it unmasks the bands. Liposuction is a powerful tool for the right neck: in a younger patient with firm skin, good muscle tone and true localized fat, meticulous, conservative liposuction sharpens the neck angle beautifully. How I perform it safely along the jawline is in my article on lower face liposuction.
The trouble begins when the same technique is applied to a muscle-dominant neck. This is where I see the most requests for revision. Removing fat in that setting produces predictable, poor outcomes:
- Unmasking of bands: stripping away the fat camouflage makes pre-existing platysmal bands starkly visible.
- Worsening skin laxity: without fat or muscular support beneath it, the skin collapses into wrinkled redundancy.
- Contour irregularities: an over-suctioned, uneven surface replaces smooth fullness.
These are not complications of surgery. They are complications of misdiagnosis. A surgeon’s first duty is to resist the demand for a simple solution when the anatomy calls for a comprehensive one. How that fullness returns over the months after a fat-only operation, and what the integrated correction then involves, is the subject of my article on double chin recurrence after liposuction. What matters here is choosing the right operation in the first place.
Why is platysmal laxity the overlooked cause of the aging neck?
Because at rest the fat and skin hide it, and only a dynamic examination brings it out. In my practice in Dubai, particularly among patients over 35, platysmal dysfunction is the dominant cause in the majority of submental complaints. The signs reveal themselves when the neck is tensed:
- vertical, cord-like bands down the front of the neck;
- a blunted, obtuse neck angle even at a healthy weight;
- a loss of defined jawline contour.
When the muscle is the problem, any procedure that ignores it is destined for mediocrity. Liposuction alone is not merely ineffective here; it is often the wrong choice entirely. The correct path is a form of platysmaplasty: tightening, repositioning and suturing the muscular layer to rebuild a youthful, supportive sling. This does not just remove something; it reconstructs the foundation of the neck. Where that muscle work is performed as part of a facelift rather than as an isolated neck procedure, the technique is selected by neck type rather than by dominant layer, which I set out in my article on deep platysmal work within a facelift.
How do I examine a double chin at consultation in Dubai?
With four tests that separate the layers, so the true problem is visible rather than guessed: a pinch test for fat, an animation test for the muscle, a retraction test for the skin, and a profile analysis for the bone. The consultation is where the correct pathway is decided, and it must be more than a static glance in a mirror.
| Assessment | What I ask you to do | What it examines | What it tells me |
|---|---|---|---|
| Pinch test | Nothing; I lift the fullness between finger and thumb | Quality and quantity of fat | How much of the fullness is truly fat, and how much lies beneath the muscle |
| Animation test | Tense the neck, as if grimacing or showing your lower teeth | Banding and descent of the platysma | Extent and pattern of platysmal laxity |
| Skin retraction | Nothing; I pinch the skin and release it | The skin’s ability to snap back | Whether skin excision will be needed |
| Profile analysis | Turn to the side, head level | Chin projection and hyoid position | The skeletal framework underneath |
How to read this table: the four tests run in this order and take a few minutes; together they sort the neck into one of the three categories below. One caveat on the fourth: where the profile returns a retrusive chin or a low hyoid as the dominant finding, the neck is not a fat-or-muscle problem but a skeletal one, and it belongs to the structural pathway linked above rather than to the three categories here.
Which three categories does the examination sort your neck into?
Fat-dominant, muscle-dominant or combined, and each calls for a different surgical prescription. Skipping the examination is precisely how the wrong treatment gets chosen.
| Category | Typical patient | What the tests show | Treatment direction |
|---|---|---|---|
| Fat-dominant | Younger, firm skin, a healthy weight with a localized pocket | Soft, pinchable fat; no cords on animation; skin snaps back | Conservative liposuction alone |
| Muscle-dominant | Usually over 35; blunt angle despite a healthy weight | Little in the pinch; cords on animation | Platysmaplasty; liposuction alone would unmask the bands |
| Combined | Fat plus bands, or fat plus loose skin | Pinchable fat and cords, often with slow skin recoil | Layered: conservative liposuction with platysmaplasty, and skin management as the recoil dictates |
How to read this table: the third column is the examination result, the fourth the direction it points. The components of the combined correction, and why each prevents the fullness returning, are set out in my article on double chin recurrence after liposuction; how each is performed is on my double chin removal page.
How can you read your own neck before a consultation?
By looking at three things in the mirror: how the fullness pinches, what happens when you tense your neck, and how your angle looks at your current weight. Only a proper examination can be definitive, but these observations offer an honest starting point.
- If you are younger, your skin is firm, the fullness is soft and pinchable, and no cords appear when you tense your neck, fat may well be the main issue.
- If you are over 35, notice vertical bands when you tighten your neck, or see a blunt angle despite being at a healthy weight, platysmal laxity is likely playing a leading role.
- If you recognize both, fat plus bands or fat plus loose skin, a combined problem is probable.
The value of understanding this in advance is simple: it protects you from accepting a fat-only solution for a muscle-driven problem. The reason so many results disappoint is that this distinction was never made. To have your own anatomy assessed properly, you are welcome to consult a board-certified plastic surgeon in Dubai, where the plan is built around the specific layer that is failing.
Why does respecting the layers decide whether the result lasts?
Because a neck treated by its dominant layer is structurally restored, while a neck treated by the simplest answer is only resurfaced. The path to a defined neck is not a choice between “minimally invasive” and “surgical”. It is a choice between anatomically correct and anatomically incomplete. My commitment is to diagnose with rigor and prescribe with honesty, even when the right solution is more involved than you first imagined. A neck treated this way does not just look better for a season; it is restored, which is what makes the result last. The most natural, enduring outcomes come from respecting your body’s own layered blueprint rather than reaching for the simplest answer.
Where can you read about each part of double chin treatment in Dubai in more depth?
This article covers the diagnosis; the pages below cover each other part in depth.
- The methods, candidacy, recovery, risks and cost: the double chin removal procedure page
- Why a fat-only operation lets the fullness return, and the integrated correction: double chin recurrence after liposuction
- How liposuction is performed safely along the jawline: lower face liposuction for jawline refinement
- When the bone, not the fat or muscle, is the cause: the genetic double chin in slim patients
- Muscle work within a facelift: deep platysmal work within a facelift
- Why the neck, chin and jawline are treated as one unit: the neck-chin-jawline continuum
FAQs about double chin diagnosis in Dubai
-
Is a double chin always caused by fat?
No, and assuming so is the single most common reason treatments fail. Fullness under the chin is a layered problem involving skin, superficial and deep fat, and the platysma muscle. In many patients, especially those over 35, the dominant cause is not fat at all but platysmal laxity, where the muscle separates and loses its supportive sling. Skin laxity and even a recessed chin can also contribute. Because the visible fullness can come from any of these layers, treating every double chin as a fat problem leads to disappointing results in a large share of cases. Accurate diagnosis is what determines the right approach.
-
How do I know if my double chin is fat or muscle?
The clearest signals come from a dynamic examination rather than a still glance. If you are younger with firm skin, and the fullness is soft and pinchable with no cords when you tense your neck, fat is likely the main issue. If you are over 35, see vertical cord-like bands when you tighten your neck, or have a blunt neck angle despite a healthy weight, platysmal laxity is probably involved. Both patterns together suggest a combined problem. These self-observations are a useful starting point, but only a proper assessment with tests for fat quality, banding and skin retraction can categorize your neck definitively.
-
Why does liposuction sometimes make a double chin look worse?
Liposuction works beautifully on the right neck, but on the wrong one it backfires. When platysmal laxity is the real problem, the overlying fat is camouflaging weak, separated muscle. Remove that fat and the bands beneath become starkly visible, the skin can collapse into wrinkled redundancy without its former support, and the surface may end up uneven. The neck can look older and more irregular than before. This is not a surgical complication in the usual sense; it is the predictable result of applying a fat solution to a muscle problem. It is exactly why diagnosis has to come first.
-
What is platysmal laxity, and why is it so often missed?
The platysma is a broad, thin muscle that spans the neck and acts as a supportive sling for the jawline and neck angle. With age its midline fibers separate and its lower border descends, producing vertical bands and a loss of the sharp angle between chin and neck. It is often missed because at rest, overlying fat and skin can hide it, and a static examination does not reveal it. It shows itself on animation, when the neck is tensed and the bands appear. Because it is the quiet, underlying cause in so many cases, overlooking it is what leads to fat-only treatments that cannot succeed.
-
Can my neck be both fat-dominant and muscle-dominant?
Yes, and the combined neck is the commonest one I see after the age of 35. The pinch test finds a real layer of fat, and the animation test finds cords beneath it; often the skin recoils slowly as well. A combined neck is the one most likely to be mistreated, because the pinchable fat invites a liposuction-only plan, and the bands then appear once the fat is gone. The examination settles the proportions: how much of the fullness is fat, how much is muscle, and whether the skin will follow. The plan is then layered to match, rather than built around whichever layer was easiest to see.
-
Does the shape of my platysma at birth affect my neck?
It sets the starting point. In a cadaver study of 20 necks, only 15 percent had a platysma that met completely in the midline; the other 85 percent had some degree of inherited gap, and the authors suggested that a wider, U-shaped gap may predispose to the turkey-gobbler pattern later. That is a hypothesis from anatomy rather than a measured outcome, and it describes variation you were born with, not the separation that comes with age. In practice it means two people of the same age and weight can have very different necks, and why I examine the muscle rather than predict it from your age.
-
What should a proper double chin consultation include?
A thorough consultation goes well beyond looking at the neck at rest. It should include a pinch test to gauge the quantity and quality of fat, an animation test where you tense the neck to reveal any platysmal bands, an assessment of how well the skin retracts to judge whether excision is needed, and a profile analysis of chin projection and hyoid position to understand the skeletal foundation. From these, the neck can be categorized as fat-dominant, muscle-dominant or combined, and a specific plan built accordingly. If a consultation offers a single solution without this kind of layered evaluation, that is a reason for caution.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
