

Table of content
- What are the key takeaways about what gynecomastia is made of in Dubai?
- Why is gynecomastia a diagnostic problem rather than a single procedure?
- Which three tissues make up gynecomastia?
- Why does the tissue mix decide the approach in Dubai?
- Why does an accurate reading protect the result?
- How does seeing three tissues change the conversation in Dubai?
- Where can you read about each part of gynecomastia in more depth?
- What do patients ask about what gynecomastia is made of in Dubai?
- Why do so many gynecomastia treatments not fully work?
- What are the three tissues that make up gynecomastia?
- How can I tell if my gynecomastia is glandular or fatty?
- Why can’t liposuction alone fix a puffy nipple?
- What is the deep fat layer, and why does it matter?
- Does the gland shrink if I lose weight?
- Is a puffy nipple always gynecomastia?
- What does the examination of the three tissues involve?
- Get appointment
This article covers the three tissues only: what each is, how each gives itself away, and why the mix decides the plan. How the three resolve into fatty, glandular and mixed types and which operation each needs is in my article on the three types of gynecomastia; when a scan is needed to read the mix is in gland versus fat and why ultrasound assessment matters; how excision and liposuction are combined in one operation is in the dual-technique approach to gynecomastia surgery; and candidacy, anesthesia, recovery, risks and cost are on gynecomastia surgery in Dubai.
What are the key takeaways about what gynecomastia is made of in Dubai?
Gynecomastia is three tissues in a different proportion for every man, and the correction works only when the reading of that proportion comes first.
- Gynecomastia is a mix of gland, superficial fat, and deep fat.
- Dense glandular tissue causes the puffy nipple and needs excision.
- Superficial fat creates soft fullness and responds to liposuction.
- Deep fat over the muscle blurs the pectoral border.
- Single-technique treatments fail because they miss one of the tissues.
- The tissue mix, read in advance, is what should decide the approach.
My aim here is not to describe how the surgery is performed, but to explain what your chest is made of, because identifying the tissues correctly is what decides whether a correction will work.
Why is gynecomastia a diagnostic problem rather than a single procedure?
Because each technique removes one kind of tissue, and your chest contains three. The most common surgical error is treating gynecomastia as a two-dimensional problem of volume, something to simply reduce. Liposuction alone often leaves behind dense, fibrous glandular tissue, producing persistent puffiness. Gland excision alone, without addressing the fat, can leave a chest that is soft, shapeless, or unevenly hollowed.
The literature has long recognized that composition matters. A landmark classification study of gynecomastia graded the condition on two axes, glandular versus fibrous hypertrophy and the degree of breast ptosis, so that the plan followed from what the breast was made of rather than from volume alone. It was a retrospective series of 61 patients at one institution, with no comparison arm. Its authors preferred ultrasound-assisted liposuction across most grades, with excision reserved for severe cases with significant skin excess. I draw the line between suction and excision differently, as the rest of this article explains. What is not in dispute is the starting point: correct treatment begins with an accurate reading of what the excess is made of.
Which three tissues make up gynecomastia?
Gynecomastia is made of dense fibroglandular tissue under the areola, superficial fat just beneath the skin, and deep fat over the muscle, and each behaves differently and gives itself away in a different manner. In my assessment I am identifying the proportion of these three.
| Tissue | Where it sits | How it feels | What you notice | What removes it |
|---|---|---|---|---|
| Dense fibroglandular tissue | A disc directly beneath the areola | Rubbery and firm | A puffy nipple that stays however lean you get | Precise surgical excision |
| Superficial subcutaneous fat | Just under the skin, across the chest | Soft and diffuse | General fullness and a softer contour | Liposuction |
| Deep fat over the muscle | Beneath the gland, above the pectoralis | Hard to feel separately; read by the shape | A blurred border between chest and abdomen | Liposuction in the deep plane |
How to read this table: read across one row to see how a single tissue announces itself and what answers it; read down the last column to see why one tool cannot cover all three. A successful correction addresses all three in the right proportion, and getting that proportion right is the whole purpose of the diagnostic step.

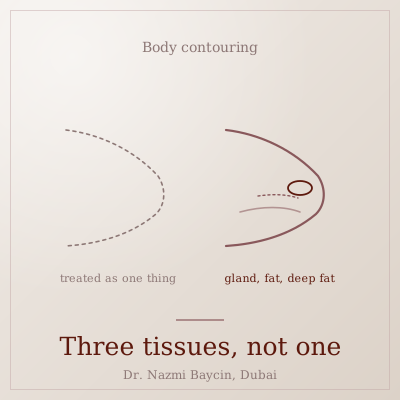
The three tissues that make up gynecomastia and why the mix determines the approach, by Dr. Nazmi Baycin, Dubai.
When does glandular tissue dominate, and why is the nipple puffy?
Glandular tissue dominates when the firm disc under the areola is the main component, and the nipple is puffy because that disc pushes the areola forward from directly beneath it. The single most useful thing you can learn to recognize is the difference between firm and soft. The dense fibroglandular tissue is the true breast gland. It feels rubbery and firm, and it sits as a disc directly under the areola. When it dominates, the puffy nipple persists no matter how lean you become.
This is the crucial point: because this tissue is firm and fibrous, liposuction cannot reliably remove it. A chest treated with liposuction alone, when the problem is truly glandular, will still show the puffiness afterward. That is exactly why so many men are disappointed by a first attempt elsewhere. A glandular-dominant chest needs direct excision of that disc, not suction.
When does fat dominate, and how does it feel?
Fat dominates when the fullness is soft and diffuse rather than firm and focused, spread across the chest rather than concentrated under the nipple. This is the pattern most influenced by your overall weight, and it is the one liposuction addresses well.
The distinction matters enormously for expectations. If your chest is mostly soft fat, you may do very well with a fat-focused approach. The same approach applied to a firm, glandular chest would fail. Telling the two apart by feel, firm and fibrous versus soft and diffuse, is a central part of my assessment, and it is why I never assume the tissue type from appearance alone. The fat of the male chest is itself often dense and fibrous rather than soft, which changes the liposuction technique even where no gland is present; how fat type is read and matched to the tool is in my article on fibrous fat versus soft fat, and the firm male chest.
What does the deep fat layer do to the pectoral border?
The deep fat layer blurs the pectoral border: when it is excessive, it hides the natural lower and outer edge of the muscle and softens the line that should separate the chest from the abdomen. It is the tissue most often overlooked, and it is what separates a merely flat chest from a defined, masculine one. It lies beneath the gland and above the pectoralis muscle.
You can have your gland removed and still be left with a chest that looks flat and shapeless, because this deep fat was never addressed. Recognizing its contribution is what allows a plan to restore not just an absence of puffiness but an actual masculine contour. How the whole male torso is planned around that border, chest first, is in my article on high-definition liposuction for male patients.
Why does the tissue mix decide the approach in Dubai?
Because each technique addresses only one part of the problem, so the operation has to be assembled from the tissues that are present rather than chosen from a menu in advance. Once you see the three tissues, the reason single-technique treatments fail becomes obvious.
| Dominant tissue | How it presents | Why a single method fails | What you notice afterward |
|---|---|---|---|
| Dense fibroglandular | A firm, puffy nipple | Liposuction leaves the firm gland behind | The puffiness is still there once swelling settles |
| Superficial fat | Soft, diffuse fullness | Excision alone leaves the chest soft | No puffiness, but the chest still looks full in a shirt |
| Deep fat over muscle | A blurred pectoral border | Ignoring it leaves a flat, shapeless chest | Flat but not masculine; no lower pectoral line |
| Combined (most men) | Puffiness plus fullness plus blur | Any one technique corrects only a third | Partial improvement that feels like a failed operation |
How to read this table: the last column is what men describe to me after a single-method operation elsewhere; match it to the first column to see which tissue was left untreated. Because most men have some proportion of all three tissues, most cases need more than one technique, combined in the balance the diagnosis reveals.
How those proportions resolve into three treatable types, and which operation each one needs, is in my article on the three types of gynecomastia and the operation each one needs. How excision and feathering liposuction are combined in one operation, and in what order, is in my article on the dual-technique approach to gynecomastia surgery. The operation itself, with candidacy, recovery and risks, is on my procedure page for gynecomastia surgery in Dubai. The purpose here is simply to establish why the diagnosis must come first.
Why does an accurate reading protect the result?
An accurate reading protects the result because tissue predominance is one of the features a surgical plan cannot be built without, and a plan built without it treats the wrong layer. There is strong support in the surgical literature for making classification the foundation of treatment. A systematic review of gynecomastia classification systems screened 1,012 articles and included 11. It found that the eleven published systems each captured only two or three of the ten features surgeons actually use, most often breast size and ptosis. Its authors concluded that none of the existing systems was adequate for surgical decision-making, and that a usable one would have to combine breast size, breast ptosis, tissue predominance and skin redundancy. It is a review of classification systems, not a comparison of operations, so it tells us what a plan must include, not which operation performs best.
This is why I spend the consultation identifying the tissue mix by careful physical examination:
- I feel for the firm glandular disc under the areola.
- I assess the softness and distribution of the fat across the chest.
- I judge how much the deep layer is hiding the lower border of the muscle.
Where a muscular chest wall or a thick fat layer makes that reading less certain, I confirm it with an ultrasound scan; when a scan changes the plan is in my article on gland versus fat and why ultrasound assessment matters. Only once that reading is complete does the question of technique arise, because a correction built on an accurate diagnosis is what lets the chest look masculine and stay that way.
How does seeing three tissues change the conversation in Dubai?
It changes the question you ask: instead of which single procedure to have, you ask which tissues are present and in what proportion, and that reframing is what makes a complete, natural correction possible rather than a partial one that disappoints.
Your chest is an individual combination of gland, superficial fat and deep fat, and an honest result depends on reading that combination correctly before anything else. That diagnostic discipline, seeing what is truly there rather than reaching for a familiar technique, is the foundation of a chest that looks strong, defined and authentically masculine. That discipline is the standard of my plastic surgery practice in Dubai.
Where can you read about each part of gynecomastia in more depth?
This article covers what the excess is made of; the pages below cover each other part of gynecomastia in depth.
- The operation, candidacy, recovery, risks and cost: the gynecomastia surgery procedure page
- The three types and the operation each needs: the three types of gynecomastia
- When a scan is needed to read the mix: gland versus fat and why ultrasound assessment matters
- How excision and liposuction are combined in one operation: the dual-technique approach to gynecomastia surgery
- How a natural chest is sculpted and the crater deformity avoided: the three pillars of a natural male chest
- Correcting a hollow or uneven result from earlier surgery: revision gynecomastia surgery
- Fibrous versus soft fat, and the firm male chest: how tissue type changes liposuction technique
- Where the chest fits into whole-torso male contouring: high-definition liposuction for male patients
What do patients ask about what gynecomastia is made of in Dubai?
Patients ask me why so many treatments fail, what the three tissues are, how to tell gland from fat, why liposuction cannot fix a puffy nipple, what the deep fat layer is, whether the gland shrinks with weight loss, whether a puffy nipple is always gynecomastia and what the examination involves; the answers are below.
-
Why do so many gynecomastia treatments not fully work?
Because they treat the condition as if it were one thing, when it is a combination of three tissues. You are often offered liposuction alone or gland removal alone, and each addresses only part of the problem. If the excess is truly glandular and liposuction is used, the firm gland is left behind and the puffiness persists. If the excess includes a lot of fat and only the gland is removed, the chest is left soft and undefined. In both cases the tissue that was driving the problem went untreated. That is why I place so much emphasis on the diagnosis before anything else; it is the step most often skipped when men come to me after a disappointing first result elsewhere.
-
What are the three tissues that make up gynecomastia?
The first is dense fibroglandular tissue, the true hormonal breast gland, which is rubbery and firm and sits directly under the areola. It is the classic cause of the puffy nipple, and it needs surgical excision. The second is superficial subcutaneous fat, the soft layer just under the skin across the chest, which creates a general, diffuse fullness; liposuction removes it well. The third is deep fat, which sits beneath the gland and above the pectoralis muscle and blurs the natural border of the pec. Most men have some proportion of all three, and my job at consultation is to work out how much of each is present, because that mix decides the approach.
-
How can I tell if my gynecomastia is glandular or fatty?
The most reliable clue is how it feels. Glandular tissue is firm and rubbery and concentrated as a disc directly behind the nipple, which is what produces a puffy nipple that stays even when you are lean. Fatty fullness is softer and more spread out across the chest. Feeling the difference accurately takes an examination, because many men have both, and appearance alone can mislead: a firm puffy nipple over a generally soft chest points to a combination rather than one or the other. This is exactly the distinction I assess by hand, because it changes the plan completely.
-
Why can’t liposuction alone fix a puffy nipple?
Because the puffy nipple is usually caused by dense, fibrous glandular tissue, and that tissue is too firm for liposuction to remove reliably. Liposuction is designed to remove soft fat, and it does that well, but it slides past the rubbery gland. If a chest with a firm glandular disc is treated by liposuction alone, the fat around it may be reduced but the disc remains, so the puffiness persists. This is one of the commonest reasons men come to me unhappy after a previous procedure. When the gland is the problem, it needs to be excised directly through a small, well-hidden incision; I still assess the surrounding fat, because it usually needs attention too.
-
What is the deep fat layer, and why does it matter?
The deep fat is the layer that sits beneath the gland and on top of the pectoralis muscle, and it is the tissue most often overlooked. When it is excessive, it blurs the natural border of the pectoral muscle and softens the clean line that should separate the chest from the abdomen. You can have your gland removed and your superficial fat reduced and still be left with a chest that looks flat and shapeless, simply because this deep layer was never addressed. It is the difference between removing a problem and restoring a masculine contour, which is why I judge how much this layer is hiding the muscle in every assessment.
-
Does the gland shrink if I lose weight?
No. Weight loss shrinks the two fat layers, because fat cells empty as you lose weight, but the fibroglandular disc is not fat and does not respond. This is why a puffy nipple can look more obvious, not less, after you lose weight: the soft fullness around it has gone and the firm disc now stands alone. If your chest flattens completely with weight loss, the excess was fat. If a firm, puffy area remains however lean you get, that is gland, and no diet or training will remove it.
-
Is a puffy nipple always gynecomastia?
A persistent, firm puffiness directly under the nipple usually reflects true glandular tissue, which is what gynecomastia refers to. When it is firm and stays regardless of how lean you are, that points to gland rather than fat. Softness and fullness that changes with your weight is more likely fatty, and the two can coexist. This is why I am careful not to label a chest from appearance alone and instead assess the tissue by examination. The distinction is worth getting right because it changes what the correction needs to be: a truly glandular puffy nipple needs excision, whereas fatty fullness responds to a different approach.
-
What does the examination of the three tissues involve?
An examination by hand, focused on the tissues rather than on a quick promise of a single procedure. I feel for the firm glandular disc under the areola, I assess how much soft fat is present and how it is distributed, and I judge how far the deep fat is blurring the muscle border, with you relaxed and with the chest tensed. From that reading I can explain which of the three tissues are driving your particular chest, and therefore what a genuine correction would need to address. Where the reading is uncertain, I confirm it with a scan. I would rather you understand the diagnosis than simply be told a technique.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
