

Table of content
- What are the key takeaways about breast reduction for back and neck pain?
- Why do heavy breasts cause back, neck and shoulder pain?
- How can you tell if your pain will respond to breast reduction?
- Does the amount of tissue removed decide how much pain relief you get?
- How quickly does pain improve after breast reduction?
- What does the evidence say about pain relief after breast reduction?
- What principle guides breast reduction for pain relief?
- Which pages cover the rest of what a lighter breast changes?
- Which questions about pain relief come up most often?
- Will breast reduction cure my back pain completely?
- Does breast reduction help with tension headaches?
- Will numbness or tingling in my arms go away after breast reduction?
- Is a small breast reduction enough to relieve pain?
- Can a supportive bra or physiotherapy relieve the pain instead?
- Will breast reduction let me exercise without pain?
- Can the pain come back years after breast reduction?
- How do you find out whether breast reduction will relieve your pain?
- Get appointment
This article covers why heavy breasts cause pain, how to tell whether yours will respond, and what the evidence says about relief. For candidacy, technique, recovery, and risks, see my page on breast reduction in Dubai; for spinal alignment, see my article on how breast reduction changes posture; for the one-cup operation for athletic women, see the mini breast reduction; and for why a heavy breast that has dropped needs a reduction rather than a lift alone, see breast lift combined with reduction.
What are the key takeaways about breast reduction for back and neck pain?
Breast reduction relieves pain mainly by taking a constant load off the muscles of the neck, shoulders and upper back, and prospective studies show that relief lasting at least a year.
- The pain of heavy breasts is largely muscular: the trapezius, levator scapulae and neck extensors hold up a forward and downward load all day.
- In prospective studies, pain at the neck, shoulders, back and head falls after reduction and stays lower for at least twelve months.
- Relief has been reported after reductions under 1,000 grams as well as larger ones, so there is no fixed weight threshold for benefit.
- In my practice, the most useful sign is pain that eases when the breasts are supported; it is a clinical sign, not a validated test.
- Pain from another cause, such as a disc problem or widespread pain, is less likely to respond and is assessed separately.
- Muscle tension usually eases first, nerve symptoms settle over weeks, and pain reaches its new level by three to six months.
- A 2020 meta-analysis judged the evidence too inconsistent to offer reduction specifically as a back-pain treatment, which is why the decision is made for each woman individually.
Why do heavy breasts cause back, neck and shoulder pain?
Heavy breasts cause pain mainly through the muscles that hold them up: the upper trapezius, levator scapulae, rhomboids and neck extensors work all day against a forward and downward load. Bra straps add a second source of pain by concentrating that weight into a narrow band across the top of each shoulder.
The weight sits in front of the spine, so it pulls the upper body forward and down. The body answers by rounding the upper back and pulling the head back to keep the eyes level, and the muscles behind the neck and shoulder blades are left doing static work for hours at a time. Static muscle work is what fatigues: it reduces blood flow through the working muscle and is the classic setting for tender trigger points and myofascial pain.
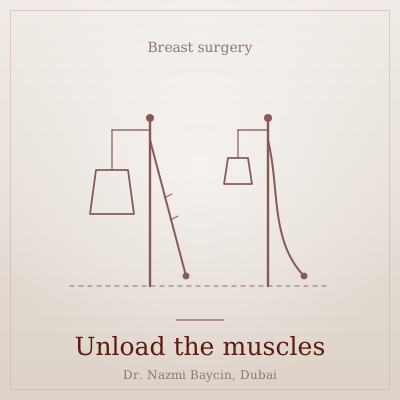
The spine’s role is often overstated. A radiographic study of 34 women X-rayed before and about twelve months after reduction found that thoracic kyphosis and lumbar lordosis angles barely changed, a mean kyphosis of about 40.5 degrees before surgery and 39.4 after. Yet relief is consistently reported. The most likely reading is that relief comes mainly from unloading the muscles rather than from reshaping the spine. How posture itself changes after surgery is the subject of my article on how reducing breast weight changes spinal alignment.

How the forward weight of very large breasts loads the neck, shoulder and upper back muscles, and what reduction removes, by Dr. Nazmi Baycin, Dubai.
Which muscles carry the load of heavy breasts?
The upper trapezius and levator scapulae carry most of the load, because they hold the shoulder girdle up against the downward pull of the breasts and the bra straps. The rhomboids and the extensors of the neck and upper back work alongside them to resist the forward pull.
These are also the muscles in which I find tenderness when I examine women with symptomatic macromastia: tight bands across the top of the shoulders, tender points along the inner border of the shoulder blade, and a stiff, overworked base of the neck. Pain in the upper trapezius commonly refers up the back of the head, which is why tension-type headaches so often travel with heavy breasts. When the pattern of tenderness matches the line of pull, it supports a mechanical explanation; when it does not, I look for another cause.
Can heavy breasts cause numbness or tingling in the arms?
They can contribute to it. Bra-strap pressure over the shoulder and a forward, dropped shoulder position can irritate the nerves that pass beneath the collarbone toward the arm, causing tingling or numbness, often on the little-finger side of the hand.
The same symptoms are also produced by a pinched nerve root in the neck and by carpal tunnel syndrome, which reduction will not treat. So I examine the neck and the hand before I attribute arm symptoms to breast weight, and I tell patients plainly when the pattern points elsewhere. Where the cause is the strap and the load, symptoms often settle over weeks to months after surgery; where it is not, they usually persist.
How does each part of the load show up as a symptom?
Each part of the load produces its own pattern: the forward pull causes neck and upper back pain, the strap pressure causes grooving and sometimes arm symptoms, and constant muscle bracing causes trigger points and headaches. The table links each one to what I look for at consultation.
| Part of the load | How the body compensates | Resulting symptom | What I look for at consultation |
|---|---|---|---|
| Forward pull of the breast mass | Rounded upper back, head pulled back | Neck and upper back pain, worse as the day goes on | Pain that eases when the breasts are supported |
| Downward pull through bra straps | Shoulders held up against the strap | Deep strap grooves, shoulder pain | Grooving depth, skin changes, tenderness over the groove |
| Strap pressure near the collarbone | Nerves compressed where they pass to the arm | Tingling or numbness in the arm or hand | Neck and hand examination to exclude other causes |
| Constant muscle bracing | Upper trapezius and levator scapulae overworked | Trigger points, stiffness, tension-type headaches | Tender bands that match the line of pull |
| Weight carried during movement | Activity avoided or cut short | Pain with running, sport or lifting | Which activities have been given up, and why |
How to read this table: read each row from left to right, from the mechanical cause to the symptom it produces. The last column is the clinical check that tells me whether a symptom really belongs to the breast load or to something else.
How can you tell if your pain will respond to breast reduction?
Pain is most likely to respond when it sits where the load is carried, at the base of the neck, across the tops of the shoulders and between the shoulder blades, worsens through the day, and eases when the breasts are supported. Pain with another clear cause, such as a disc problem, a pinched nerve root or a widespread pain condition, is less likely to resolve with reduction alone.
This is the question I spend most of a pain consultation on, because operating on the wrong pain is the commonest way to disappoint a patient. Low back pain deserves particular care: it is so common in the general population that its presence alone says little about breast weight. General suitability for surgery is a separate assessment, covered under who is a candidate for breast reduction.
| Feature | Suggests pain from breast weight | Suggests another cause |
|---|---|---|
| Where it hurts | Base of the neck, tops of the shoulders, between the shoulder blades | One side only, deep in the low back, or spreading down a leg |
| Timing | Builds through the day, eases lying down or without a bra | Worst on waking, at night, or unrelated to posture |
| Effect of support | Clear easing when the breasts are lifted and held | No change when the breasts are supported |
| Arm symptoms | Tingling that worsens with strap pressure and eases when it is lifted | Symptoms following a nerve-root pattern, weakness or reflex changes |
| Pain elsewhere | Limited to the regions that carry the load | Widespread pain, or pain in many unrelated joints |
| History | Grew with breast size, pregnancy or weight gain | Began with an injury, or has a known spinal diagnosis |
How to read this table: no single row decides the question. The more features fall in the middle column, the more likely the pain is mechanical and the more confidently relief can be expected; features in the right-hand column call for further assessment before surgery is discussed.
What is the manual support test, and how reliable is it?
In the manual support test, I lift and hold the weight of the breasts while the patient stands, and ask how her neck, shoulders and upper back feel. A clear easing of tension suggests the pain is load-related, but it is a clinical sign I use in my practice, not a validated diagnostic test, so I read it alongside the rest of the examination rather than on its own.
I hold the support for long enough for the muscles to respond, then release it, so the patient can feel the contrast in both directions. A useful result is specific: tension at the base of the neck or across the shoulders easing within moments, and returning when the weight is released. A vague sense of feeling lighter is less informative. The test has obvious limits. It lasts minutes, not hours; the patient knows what is being tested, which can color the answer; and it says nothing about arm symptoms caused by strap pressure. For those reasons I treat a positive test as supporting evidence and a negative one as a reason to look harder at other causes.
How do I assess your pain before breast reduction in Dubai?
Beyond the support test, the assessment includes posture from the front, side and back, examination of the neck, shoulder and upper back muscles, range of motion and strength, and a neurological check of the arms. Its purpose is to confirm the pain is mechanical and to exclude causes that reduction will not treat.
- Posture: head position relative to the shoulders, rounding of the upper back, and the position of the shoulder blades from the front, side and back.
- Muscle examination: palpation of the upper trapezius, levator scapulae, rhomboids and pectoralis minor for tight bands and tender points, and whether their location matches the line of pull.
- Movement and strength: neck rotation, upper back extension and shoulder elevation, looking for the overworked upper trapezius and weak shoulder-blade stabilizers that chronic bracing produces.
- Neurological check: sensation, strength and reflexes in the arms, to separate strap-related nerve irritation from a nerve root problem in the neck.
- History of treatment: what has already been tried, for how long, and with what effect.
Which treatments should be tried before breast reduction for pain?
A professionally fitted supportive bra with wide, padded straps, physiotherapy to strengthen the shoulder-blade stabilizers and stretch the overworked muscles, and weight loss where weight is part of the picture are reasonable first steps. They can ease symptoms, but they cannot remove the load itself, which is why many women find the relief partial or temporary.
I ask how long each has been tried and what changed. A woman whose pain improved substantially with physiotherapy and a well-fitted bra may not need surgery at all. A woman who has done both for months with little lasting effect, and whose pain eases clearly on the support test, has a much stronger case for reduction.
Does the amount of tissue removed decide how much pain relief you get?
Not in a simple way. Pain and quality of life improve after reductions under 1,000 grams as well as larger ones, and a large Australian cohort found the improvement was independent of resection weight and body mass index.
In a series of 59 women whose reductions removed less than 1,000 grams, every symptom measured fell significantly, including upper and lower back pain, neck, shoulder and arm pain, headaches and painful strap grooving. In a prospective cohort of 209 Australian women followed for twelve months, quality of life improved across all eight SF-36 scales after surgery while a comparison group of women with breast hypertrophy who did not have surgery stayed at baseline, and the improvement did not depend on how much tissue was removed.
That changes how I plan. I do not work toward a gram target. I plan the reduction to remove the weight the muscles have been bracing against while giving a breast that suits the patient’s frame, and I explain the proportions I am aiming for. Removing more weight is not automatically more relief; for some athletic women with symptoms, a modest reduction is the right operation, as I describe in my article on the mini breast reduction for athletic patients.
The mechanical effect of unloading has also been measured directly. A biomechanical study of eleven women, modeling low-back compressive forces during a lifting task before surgery and three months after it, found that the maximum compressive force at the low back fell by 35 percent, while self-reported functional disability improved by 76 percent. Those are modeled forces rather than measured ones, in eleven patients with no control group, but the direction and size of the change are what the load argument predicts. How the breast is shaped and supported so that the lighter result lasts belongs to the technique, which I cover in my articles on how pedicle selection shapes long-term outcomes and why some breast reduction results relapse.
How quickly does pain improve after breast reduction?
Muscle tension in the neck and shoulders often eases within the first weeks, strap grooving and nerve symptoms settle over weeks to months, and pain has usually reached its new level by three to six months. In prospective studies, the improvement measured at six months was still present at twelve.
| Phase | What is changing | What patients commonly notice |
|---|---|---|
| First weeks | The constant load is gone; the bracing muscles start to relax | A marked sense of lightness, easing tension at the neck and shoulders, alongside normal surgical soreness |
| Weeks 2 to 12 | Strap pressure has stopped; irritated nerves and grooved skin recover | Tingling fading where it was strap-related, grooves softening, activity returning gradually |
| Months 3 to 6 | Muscles adapt to working without the load; swelling resolves | Pain settling at its new level, easier sitting, standing and exercise |
| Months 6 to 12 | The new pattern becomes stable | In prospective studies, the improvement holds at twelve months |
How to read this table: the timings are typical, not guaranteed, and they describe pain rather than wound healing. The day-to-day course of recovery, dressings and return to work is covered under recovery after breast reduction on the procedure page.
What does the evidence say about pain relief after breast reduction?
Prospective studies consistently find that pain at the neck, shoulders and back falls after breast reduction and stays lower for at least a year, and a randomized trial found less disability than in women still waiting for surgery. What the evidence does not yet support is offering reduction specifically as a back-pain treatment, because the pooled studies vary too much to give a reliable size of effect.
A prospective Swedish series of 49 women, assessed before surgery and at six and twelve months, recorded significant reductions in pain at every site measured, neck, shoulders, back, breast, bra-strap indentation and head, after a mean resection of 1,052 grams, with the improvement still present at one year; by then the women’s SF-36 quality-of-life scores no longer differed from those of age-matched women. It is questionnaire-based and uncontrolled, and one year is the limit of what it can speak to.
The strongest single design comes from Brazil. In a randomized trial of 100 women with breast hypertrophy, half were operated on and half stayed on a waiting list; at six months, the operated women reported lower low back pain, on average from 5.7 to 1.3 on a ten-point scale, less disability on the Roland-Morris questionnaire and higher self-esteem than the waiting-list group. A Finnish study found that the quality-of-life gain after breast reduction was comparable to that after major joint replacement.
Smaller studies point the same way. A prospective study of eleven women measured posture and pain before surgery and at 60 and 90 days after it: pain fell significantly in the neck, back, shoulders and arms, but of the postural variables measured only one reached statistical significance, though several showed large effect sizes. In a sample of eleven, that is a signal rather than proof, and I cite it as corroboration.
When the literature is pooled, the direction is consistent and the certainty is not. A systematic review and meta-analysis in the European Spine Journal found thirteen eligible articles and pooled eight, reporting a large pooled odds ratio in favor of improvement in back pain, but with heterogeneity so extreme and a confidence interval so wide that the figure indicates direction rather than magnitude. Its authors concluded that the evidence does not yet justify offering reduction mammoplasty specifically as a treatment for back pain, and called for prospective studies using back pain as a defined outcome. That is a fair verdict on the literature. It is not an argument against the operation; it is an argument for indicating it as I do, on documented symptoms and a careful assessment in a particular woman, rather than on a population-level promise.
How strong is each study on breast reduction and pain?
The randomized trial and the Australian cohort with a non-surgical comparison group are the strongest designs; the remaining studies are uncontrolled before-and-after series or a pooled analysis of inconsistent studies. The table sets out what each one shows and what it cannot.
| Study | Design | Patients | What it reports | What it cannot show |
|---|---|---|---|---|
| Sabino Neto et al., Aesthetic Surgery Journal, 2008 | Randomized trial with waiting-list control | 100 | At six months, lower low back pain (5.7 to 1.3), less disability and better self-esteem than controls | Results beyond six months |
| Crittenden et al., BMJ Open, 2020 | Prospective cohort with a non-surgical comparison group | 209 operated | Quality of life improved on all SF-36 scales over twelve months, independent of resection weight; controls unchanged | Pain specifically; groups were not randomized |
| Blomqvist et al., Plastic and Reconstructive Surgery, 2000 | Prospective, uncontrolled | 49 | Pain fell at all six sites measured, sustained to twelve months; quality of life normalized | Results beyond one year; no control group |
| Spector and Karp, Plastic and Reconstructive Surgery, 2007 | Questionnaire series of reductions under 1,000 g | 59 | Every symptom measured fell significantly, including back, neck and arm pain and headaches | Comparison with larger reductions or with no surgery |
| Foreman et al., Plastic and Reconstructive Surgery, 2009 | Biomechanical before-and-after study | 11 | Modeled low-back compressive force fell 35 percent; disability improved 76 percent | Directly measured forces; effects beyond three months |
| Goulart et al., Canadian Journal of Plastic Surgery, 2013 | Prospective before-and-after study | 11 | Pain fell significantly; one postural variable reached significance | Radiographic spinal change; results beyond 90 days |
| Karaaslan et al., Scientific World Journal, 2013 | Radiographic before-and-after study | 34 | Thoracic kyphosis and lumbar lordosis angles barely changed at about twelve months | Pain outcomes, which it did not measure as its main question |
| Mian et al., European Spine Journal, 2020 | Systematic review and meta-analysis | 8 pooled studies | Large pooled odds of back-pain improvement, with extreme heterogeneity | A reliable size of effect; authors judged evidence insufficient for back pain as the indication |
How to read this table: the first two rows carry the most weight because they compare operated women with women who were not operated on. The others add mechanism and detail, but none of them can rule out improvement that would have happened anyway.
What principle guides breast reduction for pain relief?
The principle is that the indication must be as precise as the operation: I recommend reduction for pain when the pain is shown to come from the weight, not simply because the breasts are large. When the reasoning is shared, the plan becomes a collaboration rather than a promise. The wider case for treating reduction as a functional operation, with the quality-of-life evidence behind it, is in my article on why breast reduction is a functional operation first.
I would rather a patient understand why I remove what I remove than simply trust that I will. A woman who walks into surgery knowing that the weight leaving her chest is the weight her neck and shoulders have been carrying, and knowing honestly how much relief the evidence supports, is the patient most likely to be satisfied with the result. To restore form is to restore function, and in this operation the function is a neck and back that no longer hurt by evening.
Which pages cover the rest of what a lighter breast changes?
This article covers only why heavy breasts hurt and how to tell whether reduction will help; the pages below cover the operation, posture, the one-cup option and what keeps a result.
- The operation, candidacy, recovery, risks and cost: the breast reduction procedure page
- The functional case for the operation and the quality-of-life evidence: why breast reduction is a functional operation first
- How reducing breast weight changes spinal alignment: breast reduction and upper-body posture
- The one-cup reduction for athletic women: the mini breast reduction
- When a dropped, heavy breast needs a reduction rather than a lift alone: breast lift combined with reduction
- The pedicle and long-term shape: how pedicle selection shapes long-term outcomes
- Why a result can lose shape over time: why breast reduction results relapse
Which questions about pain relief come up most often?
Patients most often ask whether the pain will go completely, how quickly arm and head symptoms improve, and whether a smaller reduction or non-surgical treatment could be enough. The answers below address those questions specifically.
-
Will breast reduction cure my back pain completely?
For most women whose pain comes from breast weight, it improves substantially, and in prospective studies the improvement lasts at least a year. Complete relief cannot be promised, because back pain often has more than one cause, and the part that comes from a disc, the joints or general deconditioning will not be removed with the breast tissue.
-
Does breast reduction help with tension headaches?
It often does when the headaches come from overworked neck and shoulder muscles. In a prospective study of 49 women, head pain fell significantly after reduction along with neck, shoulder and back pain. Migraine and other headache types are not caused by breast weight and are not expected to change.
-
Will numbness or tingling in my arms go away after breast reduction?
When it comes from bra-strap pressure and the dropped shoulder position of heavy breasts, it often settles over weeks to months after surgery. When it comes from a pinched nerve root in the neck or from carpal tunnel syndrome, reduction will not treat it, which is why I examine the neck and hands before attributing arm symptoms to breast weight.
-
Is a small breast reduction enough to relieve pain?
Often, yes. In a series of 59 women whose reductions removed less than 1,000 grams, every symptom measured fell significantly, including back, neck and arm pain and headaches. The right amount depends on the load your muscles are carrying and the proportions that suit your frame, not on a fixed weight.
-
Can a supportive bra or physiotherapy relieve the pain instead?
They can ease it, and they are worth trying first: a professionally fitted bra with wide straps reduces strap pressure, and physiotherapy can strengthen the shoulder-blade stabilizers. What they cannot do is remove the weight itself, so when pain persists after months of good conservative care, reduction becomes the more reliable option.
-
Will breast reduction let me exercise without pain?
For many women it does. In a series of small reductions, difficulty taking part in sports and difficulty running both improved significantly after surgery. Returning to exercise is one of the changes patients mention most, because the activities they had given up because of pain or bounce become possible again.
-
Can the pain come back years after breast reduction?
It can if the breasts enlarge again, most often with significant weight gain or pregnancy, because the load returns. Most studies follow women for about a year, so long-term figures are limited; keeping a stable weight is the most practical way to protect the relief.
How do you find out whether breast reduction will relieve your pain?
You find out through a consultation that examines where your pain sits, how it behaves through the day, what happens when your breasts are supported, and what treatment you have already tried. Only then can we decide together whether reduction, conservative care or no surgery at all is the right answer.
Sometimes the honest advice is not to operate, as I explain in the honest decision of whether to operate at all. When the pain does come from the weight, breast reduction is one of the most rewarding operations I perform: not just a lighter silhouette, but a neck and back that no longer carry a load all day. If you would like to find out whether that is true for you, I invite you to schedule a consultation at my plastic surgery practice in Dubai.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
