

Table of content
- What are the key takeaways for planning post-bariatric body contouring for patients in Dubai?
- Why does massive weight loss need a different surgical plan?
- What is assessed before the first post-bariatric operation is planned in Dubai?
- Which area should be treated first after massive weight loss?
- When can post-bariatric procedures be combined in one operation in Dubai?
- How are complications managed across a staged plan?
- What does completing the sequence change for you?
- Where can you read about each part of post-bariatric body contouring in more depth?
- What do patients in Dubai ask about planning post-bariatric body contouring?
- How many operations will I need after massive weight loss?
- How long does the whole staged plan take?
- Can I have body contouring if I lost weight with GLP-1 medication?
- What happens if my weight changes between stages?
- Does my BMI have to be normal before body contouring?
- Is post-bariatric body contouring cosmetic or reconstructive?
- Get appointment
This article covers how I prepare, prioritize and stage a body contouring plan that spans several regions after massive weight loss. For each procedure’s technique, recovery, risks and cost, see my main page on body contouring in Dubai and the procedure pages linked throughout; which abdominal technique the excess calls for is on my page on which tummy tuck technique is right for you and in my article on when a 360-degree abdominoplasty is needed, and how I support healing after each stage is in my advanced recovery protocol.
What are the key takeaways for planning post-bariatric body contouring for patients in Dubai?
After massive weight loss, I plan the whole sequence before the first incision, because the order of operations shapes both safety and the final result.
- I begin with readiness, not surgery: a settled weight, a documented weight history, adequate nutrition and a BMI I am comfortable operating at.
- BMI at the time of surgery, and the amount of tissue removed relative to it, are the clearest published predictors of complications.
- Whether the weight was lost through bariatric surgery, medication or lifestyle matters less than once thought: the two largest recent studies disagree.
- The abdomen or lower body usually comes first, the thighs after it, and the face last.
- I combine regions only when the operation stays within safe time limits and the closures do not pull against each other; everything else is staged.
- Patients who complete contouring report substantially better body image and quality of life, though the studies behind that finding are not randomized.
Why does massive weight loss need a different surgical plan?
Massive weight loss needs a different plan because the problem is spread across several regions at once, in skin that will no longer retract, in a body whose healing capacity may still be recovering from the weight loss itself. No single operation can address it, so the real question is never which operation, but which sequence.
Massive weight loss is usually defined as the loss of at least half of excess body weight. At that scale the skin has been stretched for years. Once the collagen and elastin fibers that give it recoil are damaged, it cannot shrink back; why that happens is explained on my body contouring in Dubai page.
A routine cosmetic patient usually brings one concern. After massive weight loss you usually bring four or five: the abdomen, the breasts or chest, the arms, the thighs, and often the back and face. Each of those regions is a large wound in its own right. Treating them as one project, planned from the start, is what keeps each step safe and makes the final result coherent rather than a collection of separate repairs.
What makes the massive weight loss patient a higher-risk surgical patient?
Two factors stand out in the published evidence: your BMI at the time of surgery, and how much tissue is removed relative to it. Diabetes adds to that risk; the route by which you lost the weight, on current evidence, may not.
A prospective cohort of 606 body contouring patients at a single German center, analyzed with a focus on abdominal contouring, found that complications rose significantly above a BMI of 31 at the time of surgery. A resection weight disproportionate to BMI, an index above 105, was equally predictive. The same cohort found more complications after bariatric surgery than after weight lost through lifestyle change. That last finding has not held everywhere. A 2026 single-center study of 1,002 body contouring patients found no difference in complication rates whether the weight was lost through bariatric surgery, GLP-1 medication, lifestyle change or a combination, and identified BMI at surgery and diabetes as the independent predictors. It was retrospective, and two-thirds of its patients had had bariatric surgery, so the smaller groups carry less certainty.
I read the two studies together. Where they agree, on BMI, I act on it: I would rather you spend a few more months settling your weight than operate above the point where the risk climbs. Where they disagree, on the route of weight loss, I do not treat a bariatric history as a risk in itself, but I do treat it as a reason to check nutrition carefully.
| Risk factor | What the evidence shows | How I use it in planning |
|---|---|---|
| BMI at the time of surgery | Complications rose above a BMI of 31 in the 606-patient cohort; BMI was an independent predictor in the 1,002-patient study | I plan for a settled BMI and do not operate at the top of your weight range |
| Resection weight relative to BMI | An index above 105 predicted complications as strongly as BMI itself | Very large resections get an operation of their own rather than being combined |
| Diabetes | An independent predictor in the 1,002-patient study | Blood sugar control is confirmed with your physician before surgery |
| Route of weight loss | More complications after bariatric surgery in one cohort; no difference in the other | Not a barrier on its own, but a prompt to check nutrition before planning |
| Number of combined procedures | Combined operations were longer, with more minor complications and longer stays, but no rise in major complications | I combine regions only within safe operating limits |
| Weight fluctuation | Weight history is part of standard preoperative screening after massive weight loss | I document the full weight history and wait until the weight has settled |
How to read this table: the middle column is what has been measured, and the right column is the decision I make from it. No single factor rules you in or out; I weigh them together, and several of them, such as BMI and nutrition, can be improved before surgery.
What is assessed before the first post-bariatric operation is planned in Dubai?
Before I plan any operation, I assess readiness: how settled your weight is, how well nourished you are, what your abdominal wall and skin show, and what matters most to you. Only then do I decide the order.
I begin with the full weight history: starting weight, lowest weight, current weight and how long the weight has been stable. My general rule, set out on my body contouring page, is to consider contouring about twelve months after weight loss has plateaued, with the exact timing depending on how severe the original obesity was. What I am looking for is not a number on the scale but a weight you can hold, because the skin envelope I tailor in surgery is cut to fit that body.
The examination then tells me what the plan has to contain:
- I map where the excess skin lies and how it hangs.
- I check the abdominal wall for muscle separation or hernia.
- I ask which region troubles you most, because your priorities can legitimately change the order.
- I make sure you understand that this is a journey of several operations, each with its own recovery, and that you are ready for it.
| What I check | Why it matters | What happens if it is not yet met |
|---|---|---|
| Weight history and stability | The tailored skin envelope must fit the body you will keep | The plan is drawn up, but the first operation waits until the weight has settled |
| BMI | The clearest published predictor of complications | Further weight optimization with your bariatric team or physician first |
| Protein, iron and vitamin status | Deficits impair wound healing and are common after bariatric surgery | Repletion, coordinated with the bariatric team, before surgery is booked |
| Diabetes and other medical conditions | Diabetes independently raises the complication risk | Optimization with your physician |
| Smoking | Impairs blood supply to the wound edges | Stopping before surgery |
| Abdominal wall | Muscle separation or a hernia changes the abdominal operation | Hernia repair is planned with a general surgeon where needed |
| Pattern of excess skin | Determines which procedures are needed and in what order | Not a barrier; it shapes the sequence |
| Priorities and expectations | Your main concern can move a region earlier in the sequence | Discussed until we agree on a plan you understand |
How to read this table: read it as a checklist completed before the first date is set. A “not yet” in any row delays the start rather than cancelling the plan, and most rows can be corrected within weeks or months.
How does nutrition affect healing after massive weight loss?
Nutrition matters because wound healing needs protein, iron and vitamins, and bariatric surgery can leave you short of all three through restricted intake and malabsorption. The evidence on how much correcting it lowers the complication rate is still limited, so I treat optimization as a precaution, not a promise.
Wound healing problems are the most common complication after post-bariatric contouring; in the 606-patient cohort they affected 21.5% of patients. That cohort did not measure nutrition, so linking those problems to deficiency is an inference rather than a finding. I still check protein status, blood count and key vitamins before planning, and I coordinate any repletion with your bariatric team. The cost of checking is small; the cost of operating on a depleted patient is a wound that will not close. That caution is the standard I apply to all post-bariatric work as a DHA-licensed plastic surgeon in Dubai.
Which area should be treated first after massive weight loss?
For most patients I treat the abdomen or lower body first, the breasts and arms next, the thighs after the abdomen has healed, and the face last. Your own priorities can change that order, but the anatomy usually sets it.
I do not sequence by what is easiest. I sequence by what the later operations depend on. The abdomen and lower trunk sit at the center of the body, and how they are tightened changes the tension on the pubic area and thighs below and the flanks and back around them. Operating there first gives every later stage a stable base to build on.
Why is the abdomen or lower body usually treated first?
The abdomen or lower body usually comes first because it is often your greatest burden, and because every later operation below and around it depends on how it is tightened. Whichever technique it needs, it goes first.
That technique ranges from a front-only tummy tuck in Dubai, to a Fleur-de-Lis pattern where the excess runs both vertically and horizontally, to a circumferential lower body lift where it extends onto the flanks and back. How I choose among them is set out on my tummy tuck page under which tummy tuck technique is right for you and in my article on when a 360-degree abdominoplasty is needed. Whichever pattern is chosen, the quality of the skin that remains decides how long the incision must be and how the closure is layered, which I explain in my article on tissue elasticity and incision length in abdominoplasty. Where the pubic area stays heavy after the abdomen is tightened, it is addressed as described in correcting a heavy pubic area after weight loss.
Where do the breasts and arms fit in the sequence?
The breasts and arms usually form the second stage, because they share the upper body and can often be treated together without their closures pulling against each other. Where laxity runs from the arm onto the side of the chest, I plan the two as one continuous unit.
After massive weight loss the breast is usually both deflated and descended. Depending on what remains, it needs a breast lift in Dubai, a lift combined with an implant, which I describe in breast lift with implants after massive weight loss, or, where the breast is still disproportionately large, a breast reduction in Dubai. The arms are treated with an arm lift in Dubai, extended onto the chest wall when needed, as set out in the extended arm lift for lateral chest laxity, and refined with liposuction in Dubai where residual fat blurs the contour.
Why are the thighs usually treated after the abdomen?
I usually treat the thighs after the abdomen has healed, because a lower body lift and a thigh lift place tension on the same tissues in different directions, and two closures pulling against each other in one operation heal poorly. The lower body lift also lifts the outer thigh, so the thigh plan is best judged once that has settled.
Staging the thigh separately also keeps two of the largest healing fields in the body from competing at once. Which thigh lift in Dubai you then need depends on where the excess sits and how far down the leg it runs, which I cover in vertical or horizontal thigh lift after weight loss and in matching thigh lift technique to anatomy.
When does the face come into the plan?
The face usually comes last, because it is rarely your first concern and because its result is best judged once the body has settled. Weight loss often leaves the cheeks and neck sagging, and the face can look older than you feel.
Where that is the case, a facelift in Dubai completes the plan. I raise it in the first consultation so it is part of the map, but I leave the decision until the body stages are done, when you can see what you still want.
When can post-bariatric procedures be combined in one operation in Dubai?
I combine procedures when the operation stays within safe time limits, your health supports it, and the combined closures do not pull against each other; otherwise I stage them. Combining is not the danger in itself; length, blood loss and opposing tension are.
A large registry study from a center dedicated to massive weight loss surgery found that combining procedures lengthened the operation and the hospital stay and raised the rate of minor complications, but major complications did not rise with the number of procedures performed. The authors concluded that combined procedures can be safe in selected patients, and that staging is the alternative for patients who are poor candidates for a long operation. An expert review of massive weight loss surgery makes the same point from the other side: patient safety governs every decision to combine, and abdominoplasty with breast lift is a pairing its authors often recommend.
My own limits are practical:
- My body contouring operations typically run two to six hours, depending on how many areas are treated, and I do not extend an operation simply to save you a second anesthetic.
- I do not pair operations whose closures pull the same tissue in different directions.
- I keep very large resections, the kind the resection-to-BMI index flags, to an operation of their own.
Between stages, the previous operation must have fully healed: incisions closed, swelling settling, nutrition and blood count restored, and weight unchanged. On my recovery timeline that is from the second month onward, and I confirm it at review before the next date is set. There is no prize for speed.
| Stage | Typical focus | Why it sits here | What must be true before the next stage |
|---|---|---|---|
| Stage one | Abdomen or circumferential lower body | Usually the greatest burden, and the base every later stage builds on | Incisions healed, nutrition and blood count restored, weight unchanged |
| Stage two | Breasts or chest, with the arms and lateral chest | The upper body, with closures that work together rather than against each other | Incisions healed, nutrition and blood count restored, weight unchanged |
| Stage three | Thighs | Judged after the lower body has settled; avoids opposing tension in one operation | Healing complete before any facial surgery |
| Stage four | Face, if wanted | Rarely the first concern; best judged once the body is done | Plan complete |
How to read this table: this is the sequence I use most often, not a fixed rule. Your priorities can swap stages two and three, a patient with only two affected regions may need one or two operations in total, and a small procedure can sometimes join a larger stage when the time limits allow.
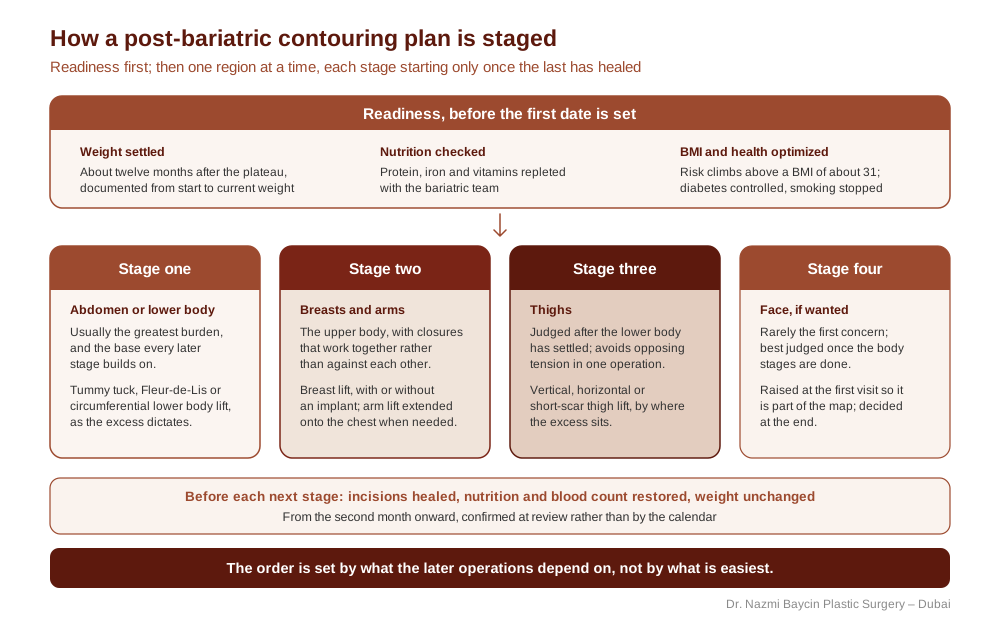
The usual order of a staged plan after massive weight loss: readiness first, then the abdomen or lower body, the breasts and arms, the thighs and, if wanted, the face, with each stage starting only once the last has healed. By Dr. Nazmi Baycin, Dubai.
The table below shows how I think about pairing procedures within one operation.
| Pairing | Why it can work | What I watch for |
|---|---|---|
| Abdominoplasty with breast lift | Separate regions whose closures do not compete; a pairing commonly recommended in the literature | Total operating time and blood loss |
| Breast surgery with arm lift | Both upper body; laxity often runs continuously from arm to chest | The chest closure where the two meet |
| Arm lift with liposuction | Liposuction refines residual fat as part of the same contour | Avoiding aggressive liposuction under a skin flap |
| Lower body lift with thigh lift | Rarely appropriate together | Opposing tension on the same tissues; usually staged |
| Any pairing with a very large resection | Not advisable | A high resection-to-BMI index; the large resection gets its own operation |
How to read this table: the first column lists pairings patients most often ask about. “Why it can work” is not a promise that it will be right for you; the final decision depends on the time limits and health factors above.
How are complications managed across a staged plan?
Complications after post-bariatric contouring are more common than after routine cosmetic surgery, and most are wound-healing problems, so I manage risk at the planning stage rather than only in the operating room. Staging is itself one of the most effective safety tools I have.
The 606-patient cohort recorded an overall complication rate of 37.5%, with wound healing disorders the most common at 21.5%. Those figures come from a series weighted toward abdominal contouring at one center, so they describe the demanding end of the spectrum rather than every procedure in a plan. Staging lowers the stakes of each step: every operation is shorter, every wound field smaller, and every stage starts only when you have recovered from the last.
The full list of risks, and how each one is prevented, is on my body contouring page, and how I support healing after each stage is set out in my advanced recovery protocol. What is specific to a staged plan is that a complication in one stage can delay the next. I would always rather move a date than start on a patient who has not fully healed.
What does completing the sequence change for you?
Completing the sequence is associated with substantially better body image and quality of life than stopping at weight loss, although the evidence cannot yet prove that contouring is the cause. That distinction matters, and I explain it to every patient.
A systematic review and meta-analysis pooling fifteen non-randomized studies and 7,339 patients compared those who had bariatric surgery alone with those who went on to body contouring. It found markedly higher BODY-Q scores in the contouring group across body image and physical, psychological, sexual and social function, with a mean difference of 16.07 points. Among patients who had bariatric surgery alone, those who wanted contouring reported lower body satisfaction and a poorer appraisal of their excess skin, which suggests that for many the transformation does feel incomplete until the skin is addressed.
None of the fifteen studies was randomized, and the contouring group had also lost more weight, by a mean of 4.4% of total body weight. Patients who reach contouring differ from those who do not in ways that plausibly affect how they rate their own lives, so the association is well established while the direction of cause is not. I would rather say that plainly than lean on a number that cannot carry the weight.
My philosophy rests on one word: completion. If you have achieved massive weight loss, you have done the hardest work, and a well-planned sequence removes the physical reminders of a former life so you can fully inhabit the body you have created. Because the plan spans several operations, its scope is individualized and set out candidly in consultation.
Where can you read about each part of post-bariatric body contouring in more depth?
This article covers the plan and its order; the pages below cover each region and each stage of care in depth.
- The procedures, timing, risks and cost: the body contouring procedure page
- Which abdominal technique the excess calls for: which tummy tuck technique is right for you
- When the excess runs around the back: when a 360-degree abdominoplasty is needed
- How skin quality sets the incision and the closure: tissue elasticity and incision length in abdominoplasty
- The pubic area after weight loss: correcting a heavy pubic area after weight loss
- The breast after weight loss: breast lift with implants after massive weight loss
- The arms and the side of the chest: the extended arm lift for lateral chest laxity
- The thighs: vertical or horizontal thigh lift after weight loss and matching thigh lift technique to anatomy
- Healing after each stage: the advanced recovery protocol
What do patients in Dubai ask about planning post-bariatric body contouring?
Patients ask me how many operations they will need, how long the whole plan takes, whether GLP-1 weight loss changes anything, what happens if their weight changes between stages, whether their BMI must be normal and whether this is cosmetic or reconstructive; the answers are below.
-
How many operations will I need after massive weight loss?
It depends on how many regions are affected and how much tissue each needs removed. If you have one or two concerns you may need a single operation; if you have excess skin across the abdomen, breasts, arms and thighs you usually need two to four stages, with the face, if wanted, last. I map the whole sequence at the first consultation, so you know the plan before the first step.
-
How long does the whole staged plan take?
Usually between one and two years from the first operation to the last, and longer if your weight needs to settle first. Each stage has to heal fully before the next is dated, which on my recovery timeline is from the second month onward, and I confirm it at review rather than by the calendar. A plan of two stages can be complete within a year; a plan of four, with the face last, rarely is. I would rather the journey take a season longer than start a stage on a body that has not recovered from the last.
-
Can I have body contouring if I lost weight with GLP-1 medication?
Yes. A 2026 study of 1,002 body contouring patients found that complication rates did not differ between weight lost through bariatric surgery, GLP-1 medication, lifestyle change or a combination. What matters more is that your weight is stable, because weight can return when medication is stopped, and a body tailored at one weight will not fit another.
-
What happens if my weight changes between stages?
A small change is expected and usually does not alter the plan. A significant gain or loss can change what the remaining stages need to remove, so I reassess before every stage and adjust the plan, or pause it, until your weight has settled again.
-
Does my BMI have to be normal before body contouring?
No. There is no single BMI above which surgery is ruled out, but risk rises as BMI rises: one large cohort found complications climbed above a BMI of 31. I look at your BMI together with your health, your weight history and the amount of tissue to be removed, and where lowering it first would make surgery meaningfully safer, I say so.
-
Is post-bariatric body contouring cosmetic or reconstructive?
For the massive weight loss patient, I regard it as reconstructive care. Hanging skin causes chafing, rashes and restricted movement as well as distress, and removing it restores function as much as appearance. The aim is not perfection, but a body that fits the life the weight loss made possible.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
