

Table of content
- What are the key takeaways about the three levels of vaginal support in Dubai?
- Why is vaginal support an architecture rather than a tube?
- What holds Level 1, the top of the vagina, in place?
- What holds Level 2, the vaginal walls, in place?
- What holds Level 3, the vaginal opening, in place?
- Why does the failed level matter more than the tightness?
- How does the framework become a personalized plan in Dubai?
- Why is lasting rejuvenation a restoration rather than a narrowing?
- Where can you read about each part of vaginal support and rejuvenation in Dubai in more depth?
- FAQs about the three levels of vaginal support in Dubai
- Why do you say vaginal rejuvenation is more than tightening?
- What are the levels of vaginal support?
- How can I tell which level of support has weakened?
- Which level does childbirth damage most often?
- Can more than one level be affected at the same time?
- Is this the same as prolapse surgery?
- How do you decide on the right approach for me?
- Get appointment
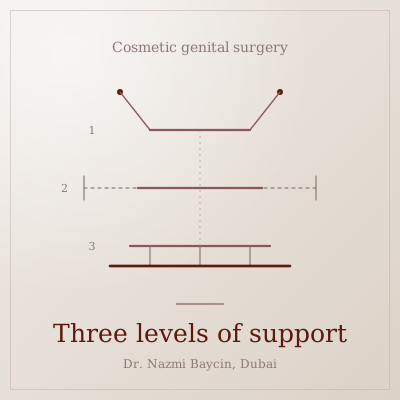
The three levels of vaginal support are the classical anatomical description of how the vagina is held in place: Level 1 suspends the top from the ligaments above, Level 2 holds the walls through fascial attachments at the sides, and Level 3 supports the opening through the perineal body and the pelvic floor.
This article covers the anatomy of support: the three levels, what holds each one and how each one fails. For candidacy, recovery, risks and cost, see my page on vaginal tightening in Dubai; for how the failed levels are found, see how vaginal laxity is evaluated; for the operation stage by stage, see the four stages of high-accuracy vaginoplasty.
What are the key takeaways about the three levels of vaginal support in Dubai?
The vagina is held by a three-level system, each level fails in its own way, and a result lasts only when the repair reaches the level that has given way.
- Vaginal support is a layered architecture, not a single tube.
- Level 1 suspends the top from the ligament complex above.
- Level 2 holds the walls through fascial attachments.
- Level 3 supports the opening via the perineal body and pelvic floor.
- Each level’s failure feels different and needs a different repair.
- More than one level is often affected, so I map the whole pattern before planning.
- Tightening the canal alone does not restore a failed level.
This support-first way of thinking is central to how I work as a genital plastic surgeon in Dubai. My aim here is not to describe the surgical steps, but to explain the anatomy of support. Once you see that the vagina is held by a three-level system, the reason a surface tightening so often disappoints becomes clear.
Why is vaginal support an architecture rather than a tube?
Because the vagina is not a passive tube but a dynamic organ suspended and supported by a three-dimensional framework. The classical anatomical description, which underpins modern reconstructive surgery, divides that framework into three levels of support.
- Level 1, apical: the top of the vagina, suspended from above by the cardinal and uterosacral ligaments.
- Level 2, mid-vaginal: the walls, held by lateral fascial attachments and the rectovaginal fascia.
- Level 3, distal: the opening, supported by the perineal body and the pelvic floor muscles.
The reason this framework matters so much is that the levels can be seen, not merely inferred. An MRI study of DeLancey’s vaginal support levels imaged twelve women with bladder-related prolapse and stress incontinence before and after surgical repair. It described a distinct appearance at each of the three levels, and those findings disappeared once the defects were repaired.
Two limits apply. The series was small, and it was drawn from women with prolapse and incontinence rather than aesthetic laxity, so it establishes the anatomy rather than the treatment. But it does establish it: the levels are identifiable structures, and a weakness in each produces a different clinical picture.
| Level | What it is made of | What it does | What most often weakens it |
|---|---|---|---|
| Level 1, apical | The cardinal and uterosacral ligament complex | Suspends the top of the vagina from the pelvic sidewall, like a hanger | Stretch of the ligaments with childbirth, age and hysterectomy |
| Level 2, mid-vaginal | Lateral attachments to the pelvic fascia; the rectovaginal fascia behind | Keeps the front and back walls firm and in position | Tearing or thinning of the fascia, usually in childbirth |
| Level 3, distal | The perineal body, the perineal muscles and the levator ani sling | Supports the lower third and the opening from below | Perineal tears, episiotomy, separation of the perineal muscles |
How to read this table: read down the first column from the deepest level to the opening. The last column is why the levels fail independently: different tissues, damaged by different events, so the same complaint can come from different places in different women.
What holds Level 1, the top of the vagina, in place?
Level 1 is held by the cardinal and uterosacral ligament complex, which anchors the top of the vagina to the pelvic sidewall and holds it up from above like a suspension. It is the deepest and highest of the three levels.
When this apical support weakens, what you feel is a sense of descent that seems to originate high inside, rather than at the opening. That is a different experience from a lax entrance, and recognizing it matters. A concern rooted at Level 1 will never be resolved by work directed only at the vaginal opening far below it.
What holds Level 2, the vaginal walls, in place?
Level 2 is held by lateral attachments of the front and back walls to the pelvic fascia and, crucially, by the rectovaginal fascia behind. This is the connective-tissue sheath that keeps the walls firm and in position.
When this fascia becomes thinned or torn, often through childbirth, the walls lose their firmness and contribute directly to a sensation of width and laxity. This is a structural failure of the wall’s support, not loose lining. Addressing it means reinforcing the fascia itself rather than trimming tissue at the surface.

The three anatomical levels of vaginal support and why lasting results depend on the failed level, by Dr. Nazmi Baycin, Dubai.
What holds Level 3, the vaginal opening, in place?
Level 3 is held from below by the perineal body and the superficial and deep perineal muscles, which integrate with the levator ani complex that forms the pelvic floor’s active sling. It supports the lower third of the vagina and the introitus, the opening itself.
When the perineal body thins or the muscles separate, the introitus gapes and support at the entrance is lost. This is the pattern most people associate with laxity. The perineal body decides this level, and it deserves its own account: what it is, how childbirth damages it, and why rebuilding it is the step most often skipped, I set out in my article on the perineal body as the keystone of the vaginal opening. How the surrounding vulvar anatomy interacts with that entrance I discuss in my article on how the surrounding anatomy affects vaginal results.
Why does the failed level matter more than the tightness?
Because the goal of durable rejuvenation is to restore the level that has actually failed, not simply to narrow the canal. These are not the same thing, and confusing them is the most common reason results do not last.
| Support level | What holds it | How its weakness feels | What restores it | Why surface tightening falls short |
|---|---|---|---|---|
| Level 1, apical | Cardinal-uterosacral ligaments | Descent felt high inside | Re-suspension of the top; often a pelvic-floor pathway rather than rejuvenation | Work at the opening cannot reach it |
| Level 2, mid-vaginal | Lateral and rectovaginal fascia | Loss of wall firmness and width | Reinforcement of the fascia beneath the lining | Trimming lining leaves fascia unreinforced |
| Level 3, distal | Perineal body and pelvic floor | A gaping, low-support opening | Rebuilding the perineal body and bringing the muscles to the midline | Narrowing skin ignores the weak keystone |
| Combined | More than one level at once | A mix of the above | Each affected level, in sequence | A single maneuver corrects only one part |
How to read this table: the third column is what you feel, and the fourth is the kind of repair that answers it; the last column is why a lining-only tightening answers none of them. The fourth column names the principle, not the steps, which belong to the operation itself.
The same principle governs reconstructive practice. A 2025 review of native-tissue pelvic floor repair proposes that a complex repair should address vaginal support at all three anatomical levels together with the structures below them. Its authors treat the visceral pelvic fascia, the perineal membrane and the external anal sphincter as one combined entity rather than separate targets.
Two things about that review deserve plain statement:
- It concerns prolapse and obstetric injury rather than rejuvenation, and it is a narrative review of the authors’ own practice, not a comparison of techniques. Its anatomical logic is the one I apply: support must be rebuilt where it was lost.
- It is candid about a limit: a significant tear of the levator ani muscle cannot be repaired, and where the muscular support beneath is deficient, the connective tissue above it remains prone to overload and gradual elongation. That is one reason I assess the muscular floor as well as the fascial levels before promising durability.
How does the framework become a personalized plan in Dubai?
It becomes a plan through an examination that identifies which level or levels are responsible in your case, because the levels fail differently in different women. That diagnostic step is what turns an anatomical map into a repair built around your anatomy rather than a template.
The pieces fit together in order:
- Evaluation: which level has weakened, and by how much, is a diagnostic discipline in its own right, set out in my article on how vaginal laxity is evaluated.
- The operation: once the failed levels are identified, the reconstruction is a deliberate, sequenced restoration of each compromised layer. The stages, their order and how the tension is calibrated are in my article on the four stages of high-accuracy vaginoplasty.
- The procedure page: candidacy, anesthesia, recovery, risks and cost are on my page for vaginal tightening surgery in Dubai.
My purpose here is simply to establish the framework that must come first: support is a three-level system, and lasting results depend on reading it correctly.
Why is lasting rejuvenation a restoration rather than a narrowing?
Because a narrowing changes how wide the canal feels for a while, and a restoration rebuilds the anatomy where the loss occurred. True vaginal rejuvenation, in my practice, is a commitment to restoring foundational anatomy rather than performing a cosmetic narrowing.
It requires a detailed knowledge of the three-level support system and the discipline to identify precisely where that system has weakened in each woman. By grounding the approach in this architecture, and by matching the restoration to the level that has given way, the result becomes far more enduring than a temporary reduction in caliber. It becomes a restoration of support, designed to last because it rebuilds the anatomy where the loss truly occurred.
Where can you read about each part of vaginal support and rejuvenation in Dubai in more depth?
Each part of the subject has its own page: the procedure page covers candidacy, recovery, risks and cost, and the articles below each go deeper into one question.
- The procedure, candidacy, recovery, risks and cost: vaginoplasty in Dubai
- How laxity is assessed before anything is decided: how vaginal laxity is evaluated and the rejuvenation options
- The keystone of the opening: the perineal body as the keystone of the vaginal opening
- Why the muscle, not the lining, must be repaired: muscle versus mucosa in vaginal tightening
- The operation, stage by stage: the four stages of high-accuracy vaginoplasty
- Protecting sensation: preserving the erogenous zones during vaginoplasty
- Severely stretched tissue: vaginoplasty after multiple deliveries
- The surrounding anatomy: how the surrounding anatomy affects vaginal results
FAQs about the three levels of vaginal support in Dubai
-
Why do you say vaginal rejuvenation is more than tightening?
Because the vagina is held in place by a layered support system, and simply narrowing the canal does not address a failure within that system. Tightening treats how wide the canal feels, but support is about the architecture that holds the walls and the opening in position. If the underlying weakness is in one of the deeper support levels, a procedure that only reduces caliber at the surface will feel different for a while but will not restore what actually gave way. That is the core reason surface tightening so often fades. I therefore think in terms of restoring support rather than narrowing width. Identifying which level of support has weakened, and rebuilding it, is what makes a result durable rather than temporary.
-
What are the levels of vaginal support?
They are the classical anatomical description of how the vagina is held in place, and I find them the clearest way to explain support to patients. Level 1 is apical support, where the cardinal and uterosacral ligaments suspend the top of the vagina from above. Level 2 is mid-vaginal support, where lateral attachments to the pelvic fascia and the rectovaginal fascia behind hold the walls firm. Level 3 is distal support, where the perineal body and the perineal muscles, together with the levator ani sling, support the opening. Each level does a different job, and each produces a different problem when it weakens. Understanding which of the three is responsible in your case is what allows a plan to be built around your actual anatomy rather than a one-size-fits-all narrowing.
-
How can I tell which level of support has weakened?
The pattern of what you feel gives important clues, though a proper assessment is needed to be sure. A weakness high inside, felt as a sense of descent from deep within, points more toward the apical Level 1. A loss of firmness in the walls and a sense of width points toward the mid-vaginal Level 2. A gaping opening and loss of support right at the entrance points toward the distal Level 3, which is the pattern most people recognize as laxity. Many women have a combination across more than one level. Distinguishing them is a diagnostic process that I carry out through a careful, structured examination, because the level that is responsible determines the entire approach. I would never assume it from symptoms alone, since the same sensation can arise from different levels in different women.
-
Which level does childbirth damage most often?
In the women I see for rejuvenation, the lower two levels most often. Delivery stretches and tears the perineal body and the perineal muscles at Level 3, which is why a gaping opening is the most recognized sign of laxity, and it thins or tears the rectovaginal fascia at Level 2, which is why the back wall loses its firmness. Level 1, the ligament suspension at the top, is affected too, but its failure tends to present later and as a sense of descent rather than width, and it more often belongs to a pelvic-floor pathway than to rejuvenation. The practical point is that one delivery can damage two levels at once, so I look at each level separately rather than assuming the opening is the whole story.
-
Can more than one level be affected at the same time?
Yes, and in my experience that is common rather than exceptional. Childbirth and the natural changes of time do not confine their effects neatly to one level, so many women have some degree of weakness across two or even all three. This is precisely why I resist a standardized approach. A woman with combined apical and distal weakness needs a different plan from one whose concern is confined to the mid-vaginal walls, even if the symptom they describe sounds similar. Recognizing the combination is part of the diagnostic work, because a single maneuver aimed at one level will under-correct if others are also involved. The whole point of thinking in levels is to map the full pattern first, and then to restore each affected level.
-
Is this the same as prolapse surgery?
The anatomy overlaps, because both are concerned with the same three-level support system, but the emphasis and the goals differ. The framework of apical, mid-vaginal and distal support comes from the same body of pelvic anatomy that informs reconstructive pelvic surgery. In rejuvenation, my focus is on restoring support and function for women with real laxity, integrating aesthetic refinement of the opening with the structural repair beneath. Where there are more significant medical problems of pelvic support, those may call for a different or collaborative pathway, and I say so. What I want you to take away is that thinking in support levels is not borrowed jargon; it reflects the real anatomy that determines results.
-
How do you decide on the right approach for me?
I begin with the anatomy rather than the technique. Through a structured, respectful assessment I work out which of the three support levels have weakened and to what degree, because that map is what determines everything that follows. From that reading I can explain which levels are responsible for your particular concern and what restoring each of them would involve. Only then does the question of the specific procedure arise, and it is chosen to match your anatomy rather than applied from a template. The reason I work this way is that, in my experience, the accuracy of that initial reading is what most determines whether a result lasts.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
