

Table of content
- What are the key takeaways about the transaxillary hidden-incision technique?
- Why is the incision placed in the armpit rather than on the breast?
- How is the implant pocket created at a distance from the incision?
- Why is the implant placed in a dual plane in this technique?
- How is symmetry confirmed before the incision is closed?
- How does the transaxillary approach compare with other incision routes?
- What are the limits and trade-offs of the transaxillary approach?
- How does the hidden-incision technique differ from the Mia Femtech procedure?
- What does the evidence show about transaxillary breast augmentation?
- How does the armpit scar heal after transaxillary augmentation?
- Why does a hidden incision demand more of the surgeon?
- Where can you read about each part of transaxillary augmentation in more depth?
- What do people ask most about transaxillary breast augmentation?
- Is transaxillary breast augmentation truly scarless?
- Does the armpit incision affect nipple sensation?
- Can I breastfeed after transaxillary breast augmentation?
- Can any implant be placed through the armpit?
- Can a later revision be done through the same armpit incision?
- Why is the pocket built by touch rather than with an endoscope?
- Get appointment
Transaxillary breast augmentation is a technique in which the implant is placed through a short incision hidden in a natural crease of the armpit, so that no incision is made on the breast itself.
Every request for breast augmentation carries a second, quieter request, one that you may voice only when you trust the surgeon enough to say it: let there be no evidence. Not of the volume, which they welcome, but of the surgery. For many years I have understood that the incision, not the implant, is what a woman fears will leave a permanent mark on her body, and that understanding is why the armpit approach has become a signature of my practice.
What are the key takeaways about the transaxillary hidden-incision technique?
The transaxillary technique moves the only scar off the breast and into the armpit, at the price of building the implant pocket from a distance, which demands precise anatomical control.
- The incision, 2.5 to 4 cm long, sits in the deepest crease of the armpit, so there is no scar on the breast; instruments I designed keep it shorter than the standard 4 to 5 cm.
- The implant pocket is built at a distance from the incision, by touch, to fixed landmarks: the edge of the pectoral muscle, the ribs and the muscle’s attachment to the breastbone.
- The implant sits in a dual plane: the muscle covers its upper part and the gland its lower part.
- The gland is never cut, so breastfeeding is preserved and nipple sensation is very rarely affected; in my series, 29 of the 40 women who later became pregnant breastfed without difficulty.
- The trade-offs are real: controlling the fold beneath the breast from a distance is harder, and a major revision may need a second incision.
- Symmetry is checked with you sitting up on the operating table before the incision is closed.
This article covers how the transaxillary technique is performed, why each step is done the way it is, and where its limits lie. For candidacy, implant choice, risks, and recovery, see my page on breast augmentation in Dubai; for how every boundary of the pocket is set and anchored, whichever incision is used, see my article on implant pocket control; for the full comparison of the three incision routes, see my article on where the scar goes in breast augmentation.
Why is the incision placed in the armpit rather than on the breast?
The incision is placed in the armpit because it is the one access route that leaves no scar on the breast and never passes through the breast gland. The alternatives, beneath the breast or around the areola, both leave a permanent line on the feature the operation is meant to enhance.
For many women this is not a cosmetic footnote. It removes the barrier that keeps them from surgery at all: the fear of a visible trace in swimwear, in lingerie, in moments of intimacy. The enhancement becomes a private fact rather than a public signature, and that respect for discretion is, to me, part of good surgery. Every incision option, and what each one costs, is compared in full in my article on where the scar goes in breast augmentation.
Where exactly in the armpit does the incision go?
The incision goes inside the deepest, best-defined natural crease of the armpit, and it is 2.5 to 4 centimeters long. I choose the crease that will hide it best when the arm is down and when it is raised.
The standard transaxillary incision is 4 to 5 cm, because the implant has to pass through it. With insertion instruments I designed for this route, including a protected sleeve, I hold it to 2.5 to 4 cm for any implant size the breast can carry. Because the short scar and the underarm fold overlap, its visibility fades within six months, and by a year it is very hard to find.
How is the implant pocket created at a distance from the incision?
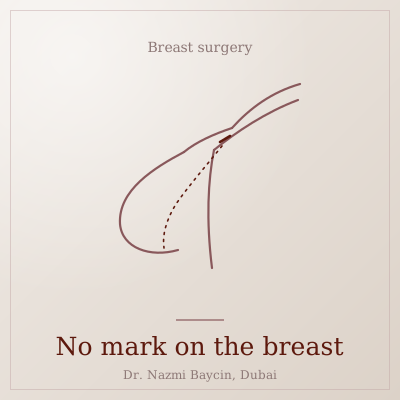
The pocket is created through a soft-tissue tunnel that runs from the armpit to the outer edge of the pectoral muscle, and then beneath the muscle and the gland, working by touch and to fixed anatomical landmarks rather than by direct sight. I perform it without an endoscope.
This is the heart of the technique and its clearest point of difference. The pocket is built far from where I entered, guided by a continuous mental map of the chest wall, and the breast gland itself is never opened.

The transaxillary hidden-incision pathway: from a concealed armpit entry to a submuscular pocket, created by tactile dissection — by Dr. Nazmi Baycin, Dubai.
Which anatomical landmarks guide the dissection?
Three landmarks guide the dissection: the firm outer border of the pectoralis major muscle, the regular pattern of the ribs and the muscles between them, and the attachment of the muscle to the breastbone.
- The outer border of the pectoralis major is where the tunnel meets the muscle and where the pocket beneath it begins.
- The ribs and intercostal muscles give a constant, rhythmic reference for depth and level as the pocket is extended downward.
- The attachment of the muscle to the breastbone marks the inner limit of the pocket; releasing too much there risks the two implants drawing toward each other, so this boundary is respected deliberately.
These structures do not move with swelling or position, which is why they can be trusted when the pocket cannot be seen. The boundaries they define, and what goes wrong when any one of them is set loosely, are the subject of my article on implant pocket control.
What are the steps of building the pocket from the armpit?
The pocket is built in a fixed sequence: a tunnel to the muscle edge, the dual-plane release of the muscle, extension of the pocket inward and downward to the marked fold, and complete preparation of the pocket before the implant goes in.
- The access tunnel. From the armpit incision I create a short tunnel through the soft tissue down to the outer edge of the pectoralis major.
- The dual-plane release. I lift the muscle from its outer border and divide its lower attachments to the degree the breast requires, so the muscle covers the upper part of the implant and the gland the lower part.
- Inner and lower refinement. I extend the pocket toward the breastbone and down to the fold beneath the breast, which is marked before surgery with you standing, comparing the reach and give of the tissue against the other side throughout.
- Preparation of the pocket. Before the implant is introduced, bleeding is fully controlled and the pocket is irrigated, because a dry, clean pocket is one of the foundations of a lasting result.
- Implant placement. The implant is passed through a protected sleeve and seated in the pocket without touching the skin.
How far the muscle is released, and how that judgment is made from the far side of the chest, is the subject of my article on the transaxillary dual-plane pocket.
Why is the implant placed in a dual plane in this technique?
I place the implant in a dual plane because the muscle over the upper part of the implant gives a soft, natural slope from chest to breast, while the gland over the lower part lets the implant fill the lower breast and move with it.
The armpit route lends itself to this plane: the tunnel arrives naturally at the outer border of the muscle, which is the doorway to the pocket beneath it. Covering the upper implant with muscle also matters for the long term: a 2025 systematic review and meta-analysis found about a third the odds of capsular contracture with placement beneath the muscle compared with placement above it.
How is symmetry confirmed before the incision is closed?
Symmetry is confirmed by bringing you briefly to a seated position on the operating table once both implants are in place. Sitting up shows the position, symmetry and drape as they will be in daily life, not as they appear lying flat.
I consider this check non-negotiable in the armpit technique in particular, because the pocket is built at a distance. If one implant sits higher or the folds are not level, it is corrected then, before closure, rather than discovered weeks later.
How does the transaxillary approach compare with other incision routes?
The transaxillary approach is the only route that leaves no scar on the breast and leaves the gland untouched, while the inframammary route gives the most direct control of the pocket and the periareolar route passes through the gland. Each trades something against something else.
| Feature | Transaxillary (armpit) | Inframammary (beneath the breast) | Periareolar (around the areola) |
|---|---|---|---|
| Scar location | Deep armpit crease, 2.5 to 4 cm | Fold beneath the breast, about 4 cm | Lower edge of the areola, about 4 cm |
| Scar on the breast | None | Yes, usually hidden by the fold | Yes, at the areolar border |
| Breast gland and ducts | Not entered; pocket reached beneath the gland | Not entered; pocket reached beneath the gland | Passed through; the only route that crosses the gland and ducts |
| Nipple sensation | Very rarely affected; the dissection stays deep to the nerves | Rarely affected | Most at risk |
| Direct view of the pocket | No; built by touch to landmarks | Yes | Yes |
| Control of the fold beneath the breast | Demanding; relies on marking and technique | Most direct | Good |
| Implant size | Any size the breast base can carry, through an insertion sleeve | Any | Limited by the diameter of the areola |
| Major revision through the same incision | Not always; capsule removal may need the fold | Usually | Usually |
How to read this table: Read across each row to see what each route gains and what it gives up. The armpit column wins on the scar, the gland and sensation, and asks more of the surgeon on direct view and fold control. A fuller comparison of all three routes is in my article on where the scar goes, and what it records.
What are the limits and trade-offs of the transaxillary approach?
The main limits are that the fold beneath the breast is harder to control from a distance, that a major revision may need a second incision, and that the approach does not suit breasts that also need lifting or reshaping. For well-shaped breasts that need volume, which is more than 90% of my cases, none of these stands in the way.
| Trade-off | Why it happens | How I manage it |
|---|---|---|
| Fold beneath the breast is harder to control | The fold is the part of the pocket farthest from the incision | The fold is marked standing before surgery, the lower pocket is released to that mark, and both sides are checked sitting up |
| Implants can sit high at first | The muscle and pocket take time to relax after surgery | This settling is expected and explained in advance; the pocket is built to the marked fold so the implant has room to descend |
| Capsule removal at a later revision | A capsule is difficult to remove fully through a distant incision | A major revision that needs direct vision is done through the fold, and I explain this possibility before the first operation |
| Breasts that also need a lift | A lift requires incisions on the breast regardless | The augmentation goes through the lift incisions instead of the armpit |
| Constricted (tuberous) lower breast | The lower breast must be scored and expanded under direct vision | The fold or areolar route is used, because the correction has to be made where the deformity is |
How to read this table: The first column names the trade-off, the second explains its cause, and the third is the step taken to manage it. Where the third column names another route, the honest answer for you is a different incision.
How does the hidden-incision technique differ from the Mia Femtech procedure?
Both use an incision in the armpit, but the Mia Femtech procedure is a proprietary system with single-use instruments and one specific implant, placed in front of the muscle, while my technique uses no proprietary system and places the implant in a dual plane.
The three-year study of 100 Mia Femtech patients describes the procedure as performed without general anesthesia, with proprietary single-use instruments and one implant, placed in front of the muscle in every case. Working outside that system, I can use any FDA-approved implant in any size your tissue can carry, placed in the plane your result calls for. The implant sizes the system allows, and what that means for the result, are set out in my comparison of the Mia Femtech system with the open transaxillary technique, and describe the procedure itself on my page about Mia Femtech breast augmentation in Dubai.
What does the evidence show about transaxillary breast augmentation?
The evidence shows that transaxillary augmentation is as safe as the other incisions, with complication rates that do not differ significantly from them, and that it carries the satisfaction of an unmarked breast. It comes from pooled observational studies and single-surgeon series rather than randomized trials.
A 2026 systematic review and meta-analysis of 11,686 breasts augmented through the armpit with silicone implants found no significant difference from the other incisions in capsular contracture, reintervention or infection, with hematoma, seroma and implant rupture each occurring in about 1 to 1.4% of breasts. A meta-analysis of seven comparative studies found capsular contracture significantly more common with the periareolar incision than with the other two (odds ratio 1.83), which the authors attribute to the ducts that route must cross.
A ten-year series of 2,430 transaxillary augmentations measured satisfaction with the validated BREAST-Q questionnaire in the 670 patients who returned it: the 543 with armpit incisions scored significantly higher for satisfaction with their breasts and with the outcome than the 127 whose incisions were on the breast. Patients chose their incision, so this is encouraging rather than conclusive.
In my own series of more than 950 augmentations, there have been no infections and no bleeding complications, and capsular contracture in 1.4%, all settled without further surgery. Those figures, and how they should be read, are set out on my page on breast augmentation in Dubai.
| Source | Design | What it found | What it does not show |
|---|---|---|---|
| Gonçalves and colleagues, 2026 | Systematic review and meta-analysis of 22 studies, 5,843 patients and 11,686 breasts augmented through the armpit | No significant difference from other incisions in capsular contracture, reintervention or infection; hematoma 1.4%, seroma 1.4%, rupture 1% | Superiority over other routes; the included studies were largely retrospective and heterogeneous |
| Periareolar incision meta-analysis, 2018 | Meta-analysis of 7 comparative studies | Higher capsular contracture with the periareolar incision than with the other two (odds ratio 1.83) | A difference between the armpit and areolar routes on their own; that subgroup comparison was not significant |
| Gryskiewicz and LeDuc, 2014 | Single-surgeon ten-year series of 2,430 transaxillary augmentations, with a BREAST-Q survey returned by 670 patients | Low complication and reoperation rates; patients with armpit incisions scored higher satisfaction than those with incisions on the breast | A randomized comparison: patients chose their incision and the comparison group was small |
How to read this table: The third column is what each source supports and the fourth is where its support stops. Together they show the armpit route is not less safe than the others; its gain is the unmarked breast.
How does the armpit scar heal after transaxillary augmentation?
The armpit scar is pink and firm for the first weeks, fades within six months and is very hard to find by a year, because it lies within the natural fold of the underarm.
In the first days I ask you to keep your arms below shoulder height, so the incision is not stretched while it seals. The overall recovery timeline, from the first days to returning to exercise, is set out on my page on breast augmentation in Dubai.
Why does a hidden incision demand more of the surgeon?
A hidden incision demands more because the pocket has to be built where it cannot be seen, so precision must come from anatomical knowledge, touch and verification rather than from direct view.
That difficulty is the reason the armpit route is less widely offered, and it is also the reason I hold to it: when it is done well, the only evidence of the operation is the result itself. To discuss whether it suits your anatomy and goals, the next step is a consultation at which the breast base, the tissue, and the armpit crease are all assessed together.
Where can you read about each part of transaxillary augmentation in more depth?
Each page below owns one part of the topic, so you can go straight to the question you have.
- Candidacy, implant choice, risks, recovery, and cost: breast augmentation in Dubai
- How far the muscle is released, judged from the far side of the chest: the transaxillary dual-plane pocket
- Every incision option compared, and what each scar records: where the scar goes in breast augmentation
- How every boundary of the pocket is built, matched, and anchored: implant pocket control in breast augmentation
- The open transaxillary technique against a branded system: transaxillary augmentation versus the Mia Femtech method
- The branded procedure itself: Mia Femtech breast augmentation in Dubai
What do people ask most about transaxillary breast augmentation?
The questions I hear most often are whether the technique is truly scarless, how it affects sensation and breastfeeding, and what happens if a revision is ever needed; the answers below are specific to the armpit route.
-
Is transaxillary breast augmentation truly scarless?
It leaves no scar on the breast, which is what scarless means here. There is a scar in the armpit, 2.5 to 4 centimeters long, placed in the deepest natural crease, where it fades within six months and is very hard to find by a year, even with the arm raised.
-
Does the armpit incision affect nipple sensation?
Very rarely. The incision is far from the areola, and the dissection runs beneath the gland, deep to the nerves that supply the nipple, so the armpit route is the one least likely to change sensation.
-
Can I breastfeed after transaxillary breast augmentation?
Yes. The gland and its ducts are never cut, so the ability to breastfeed is preserved. In my series, 29 of the 40 women who became pregnant after augmentation breastfed without any difficulty.
-
Can any implant be placed through the armpit?
Yes. Any FDA-approved implant, round or anatomical, in any size your breast base can carry, passes through the same 2.5 to 4 centimeter incision using a protected insertion sleeve. The size is decided by your anatomy at consultation, not by the route.
-
Can a later revision be done through the same armpit incision?
Minor adjustments, such as an implant exchange, can usually be done through the original armpit incision. A major revision that needs direct vision, such as removing a contracted capsule, is done through the fold beneath the breast, and I explain this possibility before the first operation.
-
Why is the pocket built by touch rather than with an endoscope?
I build the pocket by touch, guided by fixed landmarks of the chest wall, and confirm the result with you sitting up before closure. Some surgeons use an endoscope for the same purpose; what matters is a precise, symmetric pocket, and the seated check is how I verify it.


Book a private consultation with Dr. Baycin in Dubai
Get ready to look and feel best… You deserve…
